Related Experiment Video
Updated: Jun 4, 2026
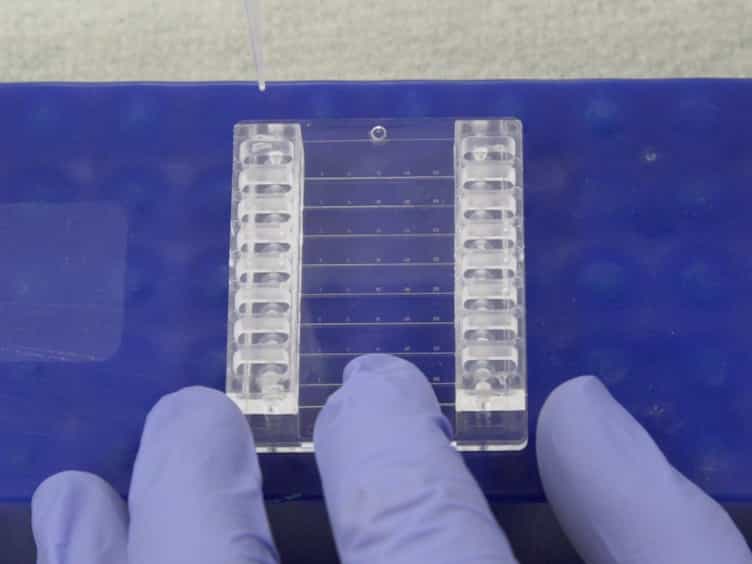

A Microfluidic Flow Chamber Model for Platelet Transfusion and Hemostasis Measures Platelet Deposition and Fibrin Formation in Real-time
Published on: February 14, 2017
Platelet depletion, platelet activation and coagulation during treatment with hemodialysis
Marianne Schoorl1, Margreet Schoorl, Menso J Nubé
1Department of Clinical Chemistry, Hematology & Immunology, Medical Center Alkmaar, The Netherlands. m.i.schoorl@mca.nl

Bioincompatibility is the total of side effects during hemodialysis (HD) including, amongst others, changes in platelet (PLT) level. Deviations in PLT count, immature PLT count, PLT morphology, CD62p expression, Platelet Factor 4 (PF4), β-Thromboglobulin (β-TG), serotonin, Thrombin-Antithrombin III (TAT) and Prothrombin Fragment 1+2 (F1+2) are monitored before and during treatment with HD in order to elucidate the interaction between modifications in PLT morphology, PLT activation and markers concerning activation of coagulation. Different patterns with time indicate that there is no correlation between an increased amount of depleted PLTs and increased amounts of PLT activation markers such as CD62p, PF4, β-TG and serotonin. A statistically significant correlation between increased PLT activation markers and markers for increased activation of coagulation such as TAT and F1+2 has not been established. Only a weak correlation is demonstrated between the increase of markers for activation of coagulation and the decrease in PLT counts, immature PLT counts and depleted PLTs during HD treatment. The change in the extracorporeal circuit during HD is probably a more critical factor in the mechanism leading to activation of the coagulation pathway than the modifications in PLT morphology.
Bioincompatibility is the total of side effects during hemodialysis (HD) including, amongst others, changes in platelet (PLT) level. Deviations in PLT count, immature PLT count, PLT morphology, CD62p expression, Platelet Factor 4 (PF4), β-Thromboglobulin (β-TG), serotonin, Thrombin-Antithrombin III (TAT) and Prothrombin Fragment 1+2 (F1+2) are monitored before and during treatment with HD in order to elucidate the interaction between modifications in PLT morphology, PLT activation and markers concerning activation of coagulation. Different patterns with time indicate that there is no correlation between an increased amount of depleted PLTs and increased amounts of PLT activation markers such as CD62p, PF4, β-TG and serotonin. A statistically significant correlation between increased PLT activation markers and markers for increased activation of coagulation such as TAT and F1+2 has not been established. Only a weak correlation is demonstrated between the increase of markers for activation of coagulation and the decrease in PLT counts, immature PLT counts and depleted PLTs during HD treatment. The change in the extracorporeal circuit during HD is probably a more critical factor in the mechanism leading to activation of the coagulation pathway than the modifications in PLT morphology.
Related Concept Videos
 01:24
Hemodialysis II: Procedure and Complications
 01:25
Hemodialysis III: Nursing Management
 01:22
Formation of the Platelet Plug
As the injured blood vessel contracts, endothelial cells undergo contraction, revealing collagen fibers in the basement membrane and underlying connective tissue. Furthermore, the plasma membrane of endothelial cells becomes adhesive, preparing the site for platelet adhesion. Platelets...
 01:25
Hemodialysis I: Introduction
 01:27
Dialysis
Acute kidney injury develops suddenly and can be caused by pre-renal causes (e.g., hypovolemia, shock), intrinsic renal causes (e.g., acute tubular necrosis), or post-renal causes (e.g., urinary obstruction). In contrast, chronic renal failure progresses gradually over time and is often...
 01:05
Introduction to Hemostasis
The three phases of hemostasis involve many clotting factors present in plasma and several substances released by platelets and injured tissue cells. It is a fast, localized, and...