Related Experiment Video
Updated: Jun 4, 2026
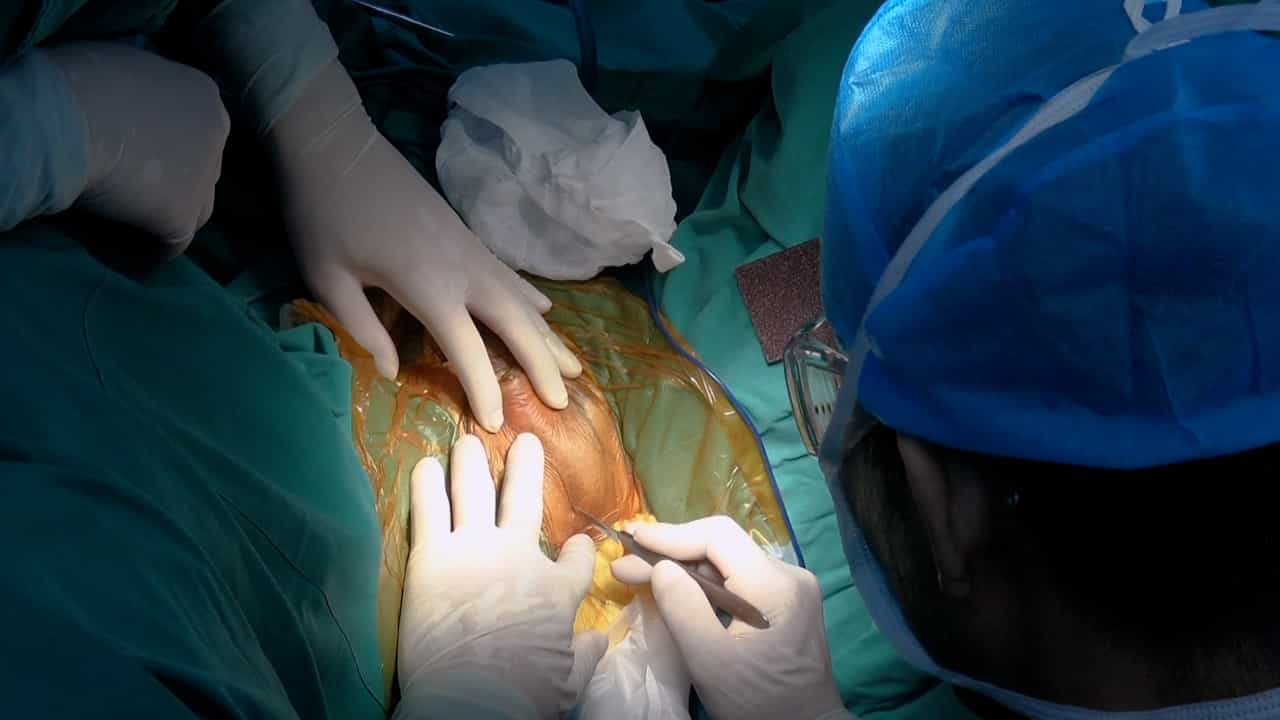

Transcorporal Artificial Urinary Sphincter Cuff Placement in a Case Requiring Revision for Urethral Atrophy
Published on: June 16, 2022
'Have you had a wee yet?' Postpartum urinary retention

Physiological changes in the bladder that occur during pregnancy predispose women to develop symptomatic retention of urine during the first hours to days after birth (Saultz et al 1991, Lose et al 1992). A basic definition of postpartum urinary retention (PUR) is the lack of spontaneous micturition six hours after vaginal birth or after removing an indwelling catheter (Humburg 2008). PUR after vaginal birth is a relatively common event, with the reported incidence ranging from 1.7 per cent to 17.9 per cent (Carley et al 2002, Ching-Chung et al 2002, Glavind and Bjørk 2003, Yip et al 2004). When examining why PUR occurs following vaginal birth research often states that instrument-assisted birth and regional analgesia are both independently associated (MacLennan 2002, Groutz 2001,Teo et al 2007). Other common risk factors include primiparity, prolonged first and second stage, perineal damage and oxytocin use (MacLennan 2002, Glavind and Bjørk 2003, Humburg 2008, Groutz et al 2001, Teo et al 2007). Unrecognised urinary retention and mismanagement may lead to recurrent urinary tract infections, upper urinary tract damage and permanent voiding difficulties (Groutz et al 2001). Humburg (2008) suggests that, overall, the lack of guidelines is one of the major problems in treating women with PUR. Careful questioning and examination from the midwife should always be performed to avoid any complication.
Physiological changes in the bladder that occur during pregnancy predispose women to develop symptomatic retention of urine during the first hours to days after birth (Saultz et al 1991, Lose et al 1992). A basic definition of postpartum urinary retention (PUR) is the lack of spontaneous micturition six hours after vaginal birth or after removing an indwelling catheter (Humburg 2008). PUR after vaginal birth is a relatively common event, with the reported incidence ranging from 1.7 per cent to 17.9 per cent (Carley et al 2002, Ching-Chung et al 2002, Glavind and Bjørk 2003, Yip et al 2004). When examining why PUR occurs following vaginal birth research often states that instrument-assisted birth and regional analgesia are both independently associated (MacLennan 2002, Groutz 2001,Teo et al 2007). Other common risk factors include primiparity, prolonged first and second stage, perineal damage and oxytocin use (MacLennan 2002, Glavind and Bjørk 2003, Humburg 2008, Groutz et al 2001, Teo et al 2007). Unrecognised urinary retention and mismanagement may lead to recurrent urinary tract infections, upper urinary tract damage and permanent voiding difficulties (Groutz et al 2001). Humburg (2008) suggests that, overall, the lack of guidelines is one of the major problems in treating women with PUR. Careful questioning and examination from the midwife should always be performed to avoid any complication.
Related Concept Videos
 01:26
Nursing Assessment of the Genitourinary System II: Inspection and Palpation
 01:26
The Micturition Reflex
The process begins with bladder filling, where the bladder wall stretches as urine accumulates. This stretching activates the urine storage reflex, mediated by the sacral spinal segments and the pontine storage center. Efferent sympathetic impulses stimulate the detrusor muscle to relax and the internal urethral sphincter to contract, facilitating urine...
 01:19
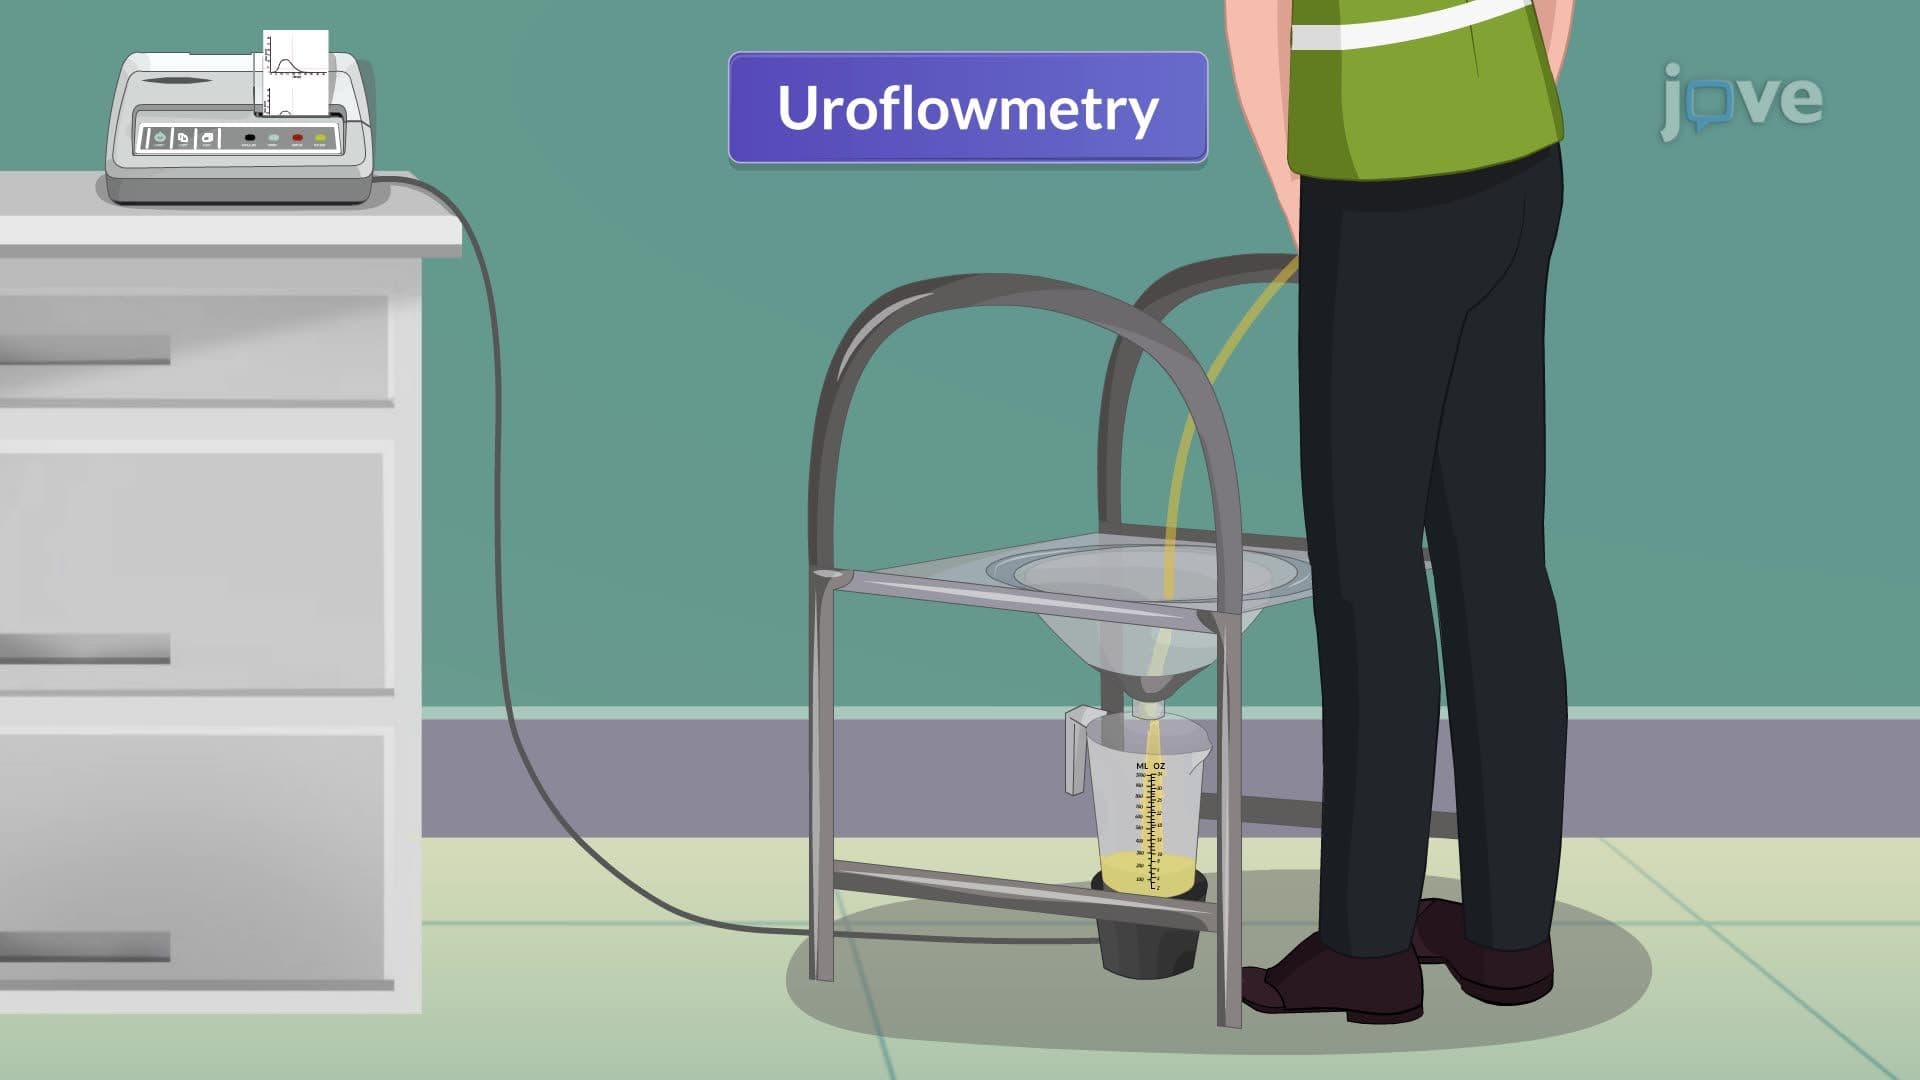
Urodynamic Studies: Uroflowmetry
 01:21
Nursing Assessment of the Genitourinary System I: Health History
 01:17
Urinary Tract Infection IV: Nursing Management
 01:23
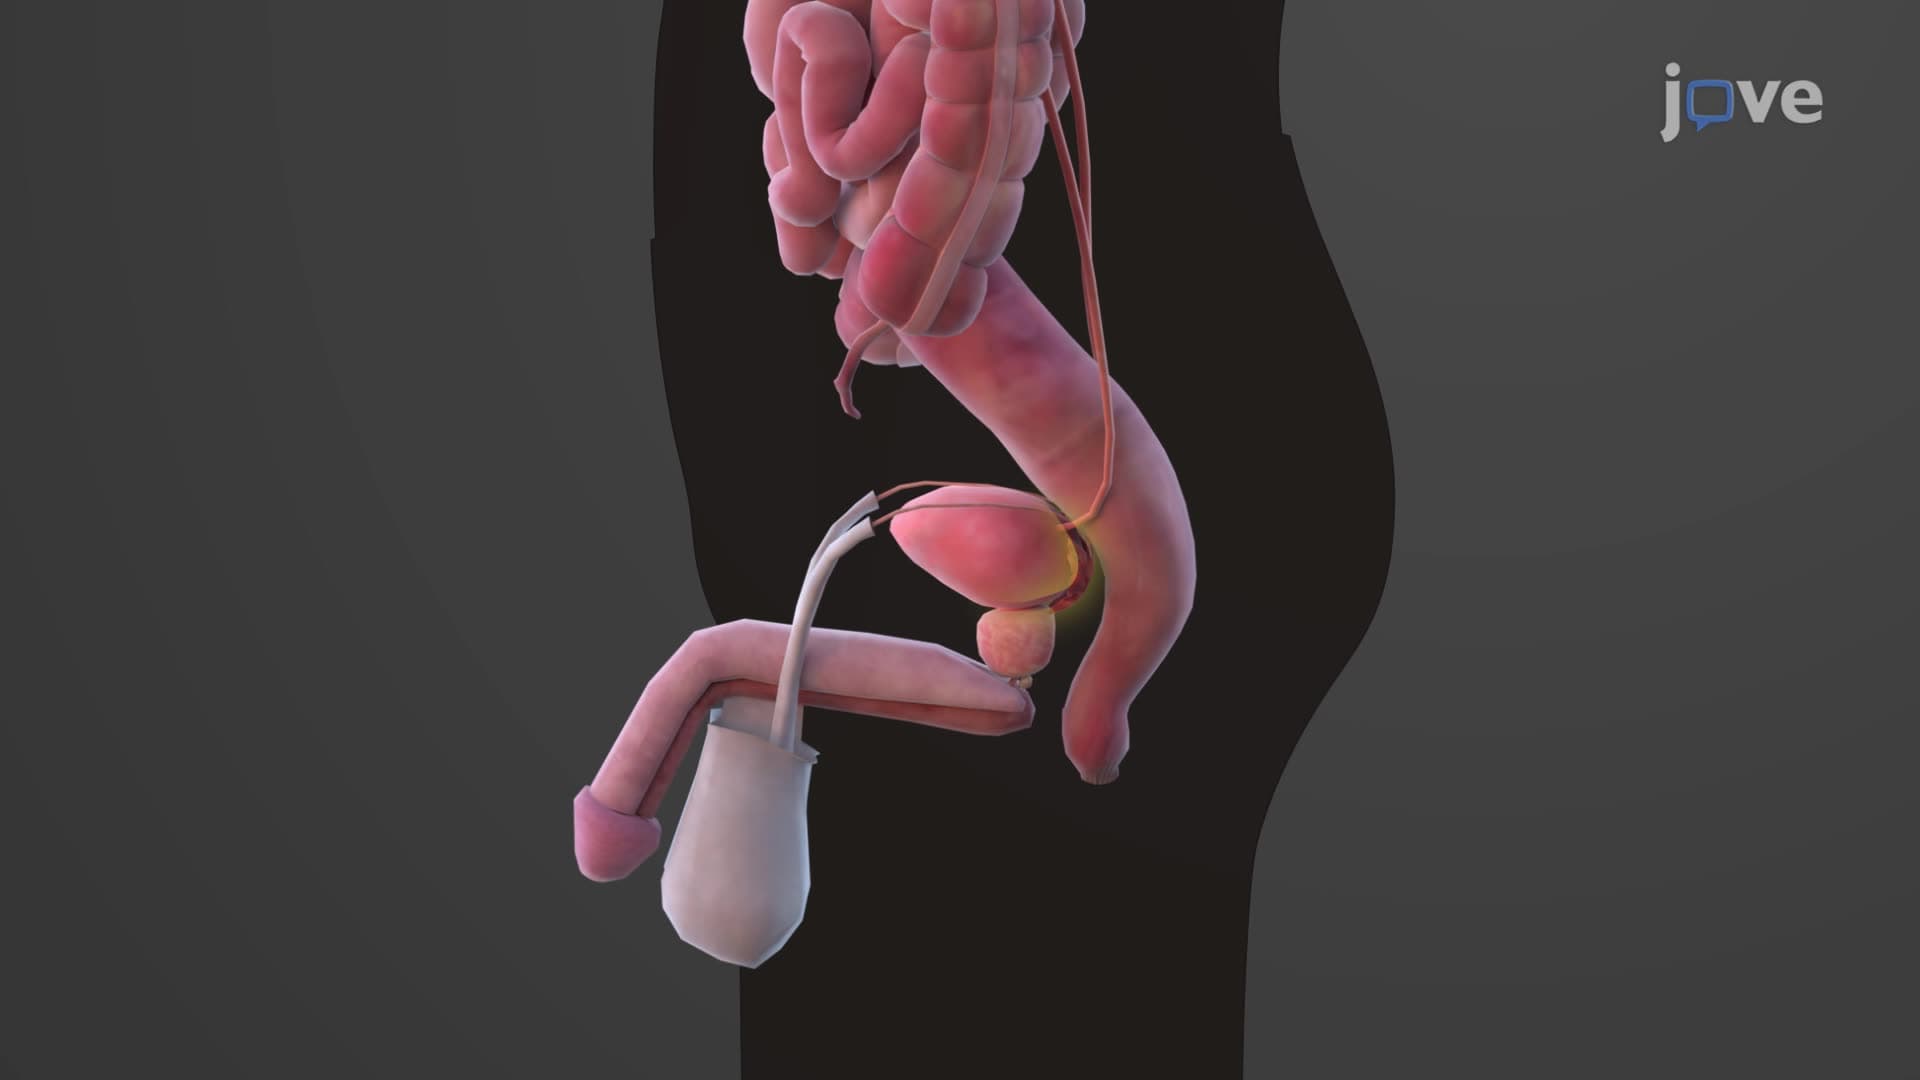
Urinary Bladder
In males, the bladder is situated in front of the rectum, while in females, it is positioned anterior to the vagina and uterus. The bladder floor contains an inverted triangular area called the trigone, defined by the two ureteric...