Related Experiment Video
Updated: Jun 3, 2026


An In Vivo Estrogen Deficiency Mouse Model for Screening Exogenous Estrogen Treatments of Cardiovascular Dysfunction After Menopause
Published on: August 13, 2019
Practice patterns with hormone therapy after surgical menopause
Adriana Chubaty1, M Tami L Shandro, Nan Schuurmans
1University of Alberta Hospital, Edmonton, AB, Canada.

Objectives:
To describe practice patterns with hormone therapy (HT) in women after a surgical menopause and to describe their experience of hot flashes and other menopausal symptoms.
Methods:
This was a cross-sectional chart-review with telephone follow up interview of women between the ages of 20 and 50 years who had a hysterectomy and bilateral salpingo-oophorectomy (BSO) before menopause at an academic teaching facility in Edmonton, Canada between December 1, 2006 and November 30, 2007.
Results:
Seventy women were interviewed. Mean respondents age at surgery was 44.3 (±5.2) years and mean time since surgery was 10.2 (±3.8) months. Twenty-eight women (40%) were started on HT after surgical menopause; 23 (33%) were still taking HT at the time of the interview. Estrogen therapy (ET) was the only HT prescribed in all instances, with over half the women on transdermal estrogen at time of the interview and 70% on ET doses equivalent to 0.625mg conjugated estrogens. Women not taking HT were more likely to experience daily hot flashes (74% vs 30%, p=0.006) and to classify them as moderate or severe intensity (57% vs 47%, p=0.033). Night sweats and difficulty sleeping were reported equally in both groups.
Conclusions:
Over 2/3rd of women were not on HT after a surgical menopause and many of these women were still having daily hot flashes. Targeted patient education prior to surgery or at discharge may help improve the management of menopausal symptoms and long term health consequences in women after a surgical menopause.

Related Concept Videos
 01:28
Menopause
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH release.
 01:30
Hormonal Control of the Ovarian Cycle
Before puberty, the hypothalamus releases GnRH in a low frequency, low amplitude pulsatile manner. This along with the immature hypothalamic-pituitary-gonadal axis activity, results in low estrogen levels and the absence of a fully functional ovarian cycle. At puberty, GnRH secretion increases in both frequency and...
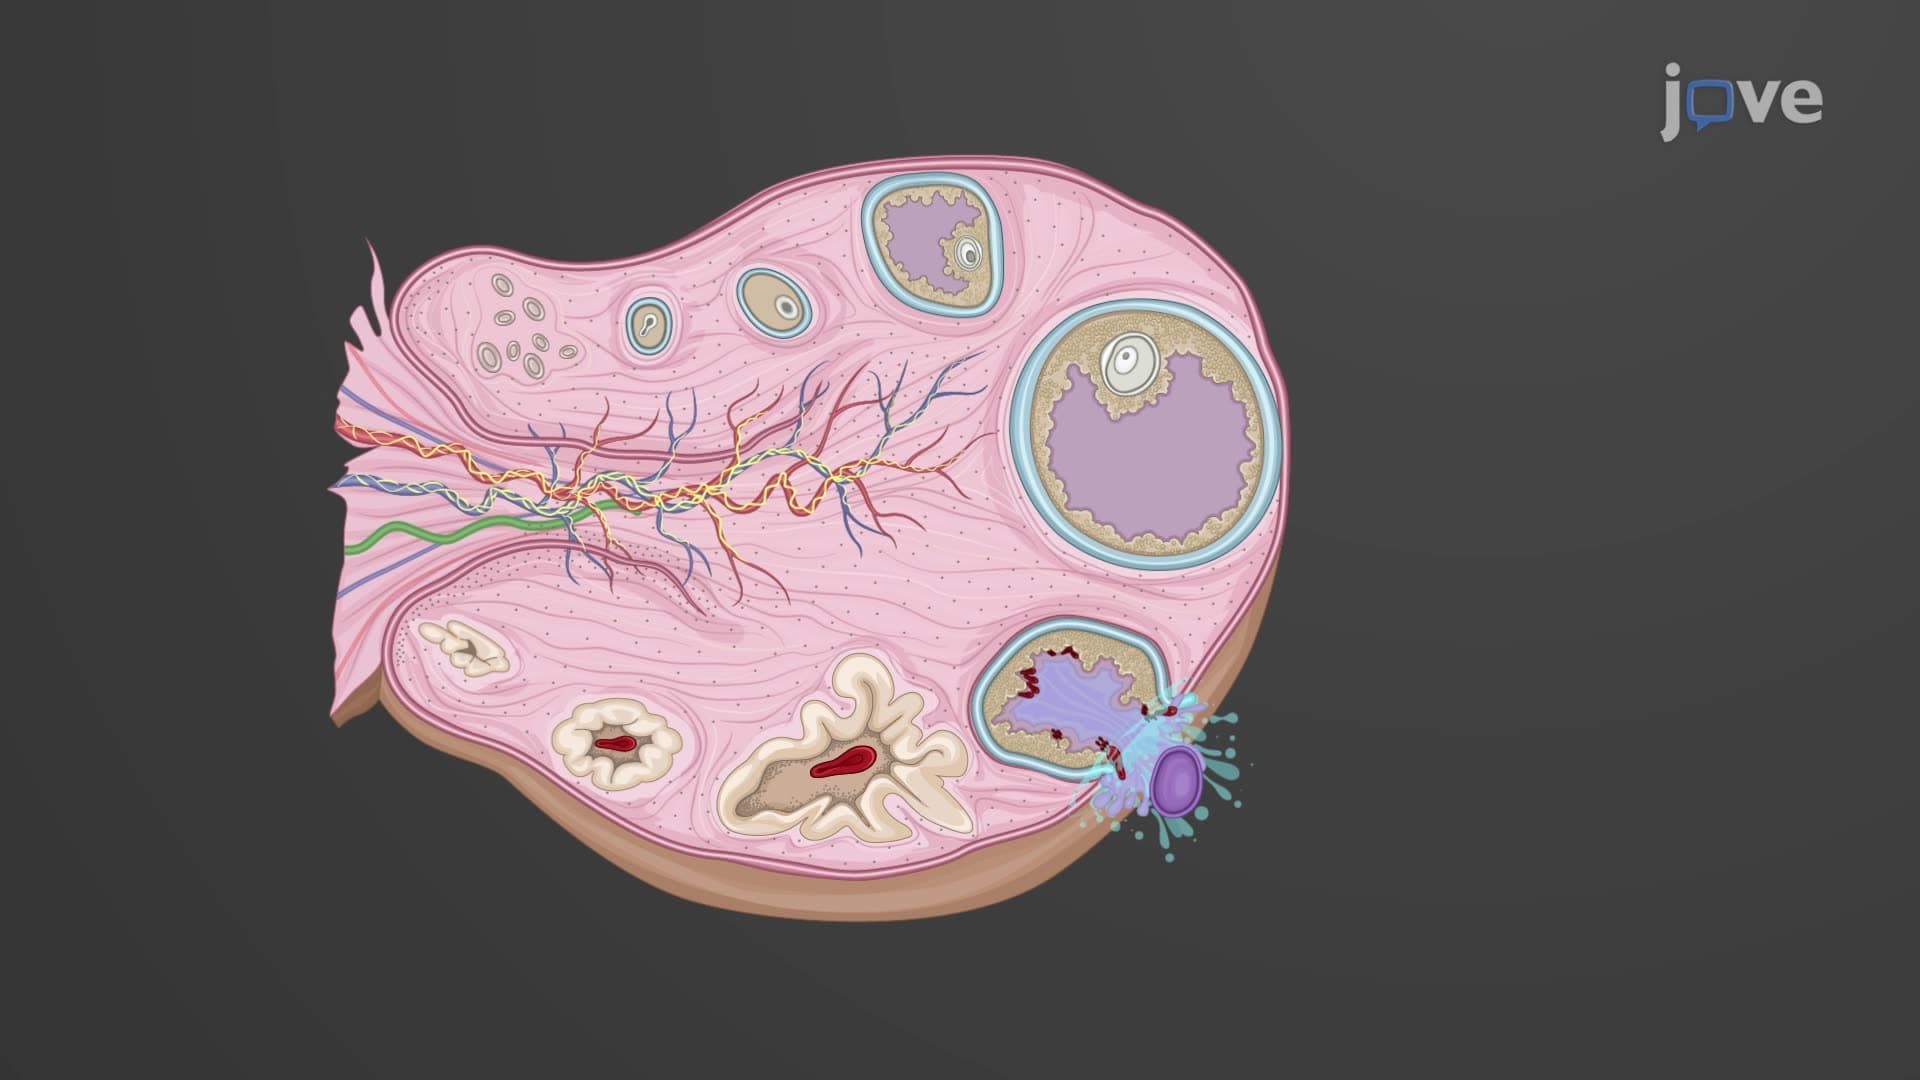 01:20
Proliferative Phase
Notably, the stratum basale, the basal layer of the endometrium, including the basal parts of the uterine glands, remains unaffected by menstruation. Stem cells in this layer undergo mitosis, regenerating the stratum functionalis and thickening the...
 01:24
Disorders of the Female Reproductive System