Related Experiment Video
Updated: Jun 3, 2026
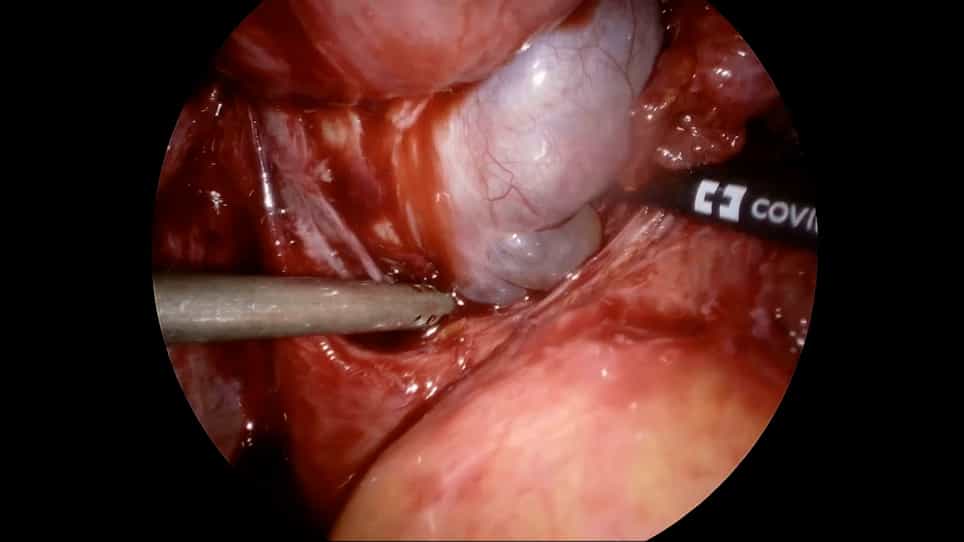

Surgical Techniques to Optimize Ovarian Reserve during Laparoscopic Cystectomy for Ovarian Endometrioma
Published on: January 22, 2022
Complete laparoscopic excision of endometriosis in teenagers: is postoperative hormonal suppression necessary?
Patrick Yeung1, Ken Sinervo, Wendy Winer
1Department of Obstetrics & Gynecology, Duke University, Durham, North Carolina 27704, USA. yeungpjr.md@gmail.com

Objective:
To determine long-term outcomes after complete laparoscopic excision done at a tertiary referral center in a teenager population, who were not specifically advised to take postoperative hormonal suppression.
Design:
Prospective observational case series (Canadian Task Force II-3).
Setting:
A tertiary referral center that specializes in the laparoscopic treatment of endometriosis.
Patient(S):
Teenagers with symptoms suspicious for endometriosis who consented and were prospectively recruited to participate in the study.
Intervention(S):
All patients underwent diagnostic laparoscopy and complete excision of all areas of abnormal peritoneum with typical and atypical endometriosis. Patients were not specifically advised to take postoperative hormonal suppression.
Main Outcome Measure(S):
Rate of recurrent (or persistent) endometriosis.
Result(S):
Twenty teenagers underwent complete laparoscopic excision of all areas of abnormal peritoneum with typical and atypical endometriosis. Seventeen patients had endometriosis confirmed by histology at initial surgery. Follow-up was up to 66 months (average 23.1 months). There was a statistically significant improvement in most pain symptoms, including bowel-related symptoms, during this time period. The rate of repeat surgery was 8 of 17 patients (47.1%), but the rate of endometriosis (diagnosed visually or histologically) found at surgery was zero. Only one-third of patients took postoperative hormonal suppression for any length of time.
Conclusion(S):
Complete laparoscopic excision of endometriosis in teenagers--including areas of typical and atypical endometriosis--has the potential to eradicate disease. These results do not depend on postoperative hormonal suppression. These data have important implications in the overall care of teenagers, regarding pain management, but also potentially for fertility. Further large comparative trials are needed to verify these results.
Related Concept Videos
 01:30
Hormonal Control of the Ovarian Cycle
Before puberty, the hypothalamus releases GnRH in a low frequency, low amplitude pulsatile manner. This along with the immature hypothalamic-pituitary-gonadal axis activity, results in low estrogen levels and the absence of a fully functional ovarian cycle. At puberty, GnRH secretion increases in both frequency and...
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH release.
 01:27
Ovarian Cycle
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...