Related Experiment Video
Updated: Jun 3, 2026
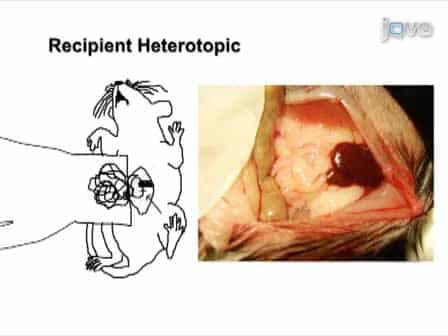

Heterotopic and Orthotopic Tracheal Transplantation in Mice used as Models to Study the Development of Obliterative Airway Disease
Published on: January 20, 2010
Cervical tracheal resection: new lessons learned
Christopher J Mutrie1, Shady M Eldaif, Caleb W Rutledge
1Department of Surgery, Section of General Thoracic Surgery, Emory University School of Medicine, Atlanta, Georgia 30322, USA.

Background:
Cervical tracheal stenosis can be a difficult condition to manage. Depending on the etiology, location, and extent of the stenosis, tracheal or cricotracheal resection may be required. Intraoperative decisions may predict outcome.
Methods:
We performed a retrospective chart review of all patients undergoing cervical tracheal or cricotracheal resection from April 2000 through March 2008.
Results:
One hundred and five patients underwent 108 tracheal or cricotracheal resections. Median age was 65 years (range, 15 to 78); 68% were women. Indication for operation included postintubation tracheal stenosis (38), idiopathic (31), tracheostomy stenosis (19), invasive thyroid cancer (9), and other (8). Median length of trachea resected was 2.7 cm (range, 1.5 to 6.0 cm); 48 patients (46%) underwent extended cricotracheal resections. Twenty-six patients (25%) had an intraoperative chin stitch placed. Hospital stay was a median of 4 days (range, 2 to 33). Operative mortality was (1%); 1 patient died of myocardial infarction on postoperative day 3. Four patients (4%) had hoarseness or vocal cord immobility. Median follow-up was 36 months (range, 1 to 79). Eighteen patients (17%) required dilation postoperatively. Seven patients (7%) required tracheostomy; 2 (2%) are tracheostomy dependent. Three patients (3%) underwent a re-resection for recurrent stenosis. Multivariate analysis of indication for resection, type of resection, length of resection, anastomotic technique, and use of chin stitch did not predict the need for postoperative dilation, tracheostomy, or reoperation.
Conclusions:
Cervical tracheal resection can be performed safely with low morbidity and mortality. Only 5% of patients required a long-term tracheostomy or re-resection for recurrent tracheal stenosis. Specific intraoperative decisions did not predict long-term success.


Related Concept Videos
 01:22
Trachea
Anatomical Features:
Location: About half of the trachea is situated in the neck, anterior to the esophagus, and extends from the larynx (at the level of the...
 01:28
Tracheostomy: Procedure and Tubes
Tracheostomy tubes can be made of semiflexible plastic (polyurethane or silicone), rigid plastic, or metal, and they come in...
 01:25
Tracheostomy Care II: Procedure
Step 1: Perform hand hygiene, and put on personal protective equipment: gown, gloves, mask and...
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:16
Tracheostomy Care I: Pre-procedural Steps
Required Equipment
The equipment necessary for tracheostomy care includes:
 01:21
Tracheostomy Decannulation
Description of the Procedure
Decannulation refers to the permanent removal of the tracheostomy tube, signaling the resolution of the condition that initially necessitated the tracheostomy. The process requires a well-coordinated interplay between...