Related Experiment Video
Updated: Jun 2, 2026


Vessel-sparing Excision and Primary Anastomosis
Published on: January 7, 2019
Traumatic strictures of the posterior urethra in boys with special reference to recurrent strictures
Satish Kumar Aggarwal1, Shandip K Sinha, Arun Kumar
1Maulana Azad Medical College & Lok Nayak Hospital, New Delhi, India. satish.childurology@gmail.com

Insights
This study evaluated 18 years of traumatic urethral stricture repairs in boys. Anastomotic urethroplasty is highly successful for primary cases, while substitution urethroplasty offers acceptable outcomes for complex or recurrent strictures.
Area of Science:
- Pediatric Urology
- Trauma Surgery
- Reconstructive Urology
Background:
- Traumatic urethral strictures in boys, often resulting from pelvic fractures, present significant reconstructive challenges.
- Recurrent strictures after initial repair necessitate specialized surgical approaches.
Purpose of the Study:
- To analyze 18 years of surgical experience with traumatic urethral strictures in pediatric patients.
- To evaluate the outcomes of primary and re-do urethroplasty, with a focus on recurrent strictures.
Main Methods:
- A cohort of 34 boys with pelvic fracture urethral strictures underwent 35 repairs over 18 years.
- Surgical techniques included anastomotic urethroplasty and substitution urethroplasty.
- Patients were divided into primary (no prior urethral repair) and re-do (previous failed attempts) groups, with median follow-up of 9 and 8 years, respectively.
Main Results:
- Primary urethroplasty achieved a success rate of 22/23 (over 95%), with minimal impact on erectile function and upper tracts.
- In the re-do group, anastomotic urethroplasty succeeded in 5/12 (41%), while substitution urethroplasty was required for 7 patients with complex strictures, yielding acceptable results.
- Two patients in each group developed stress incontinence; upper tracts were maintained in all patients.
Conclusions:
- Anastomotic urethroplasty is the preferred and highly successful method for primary traumatic urethral strictures in boys.
- Substitution urethroplasty provides a viable and acceptable alternative for complex or recurrent urethral strictures, preserving urinary and sexual function.
- Long-term follow-up confirms the durability of reconstructive techniques for pediatric urethral strictures.
Purpose:
We report 18 years' experience of traumatic urethral strictures in boys with emphasis on recurrent strictures.
Materials And Methods:
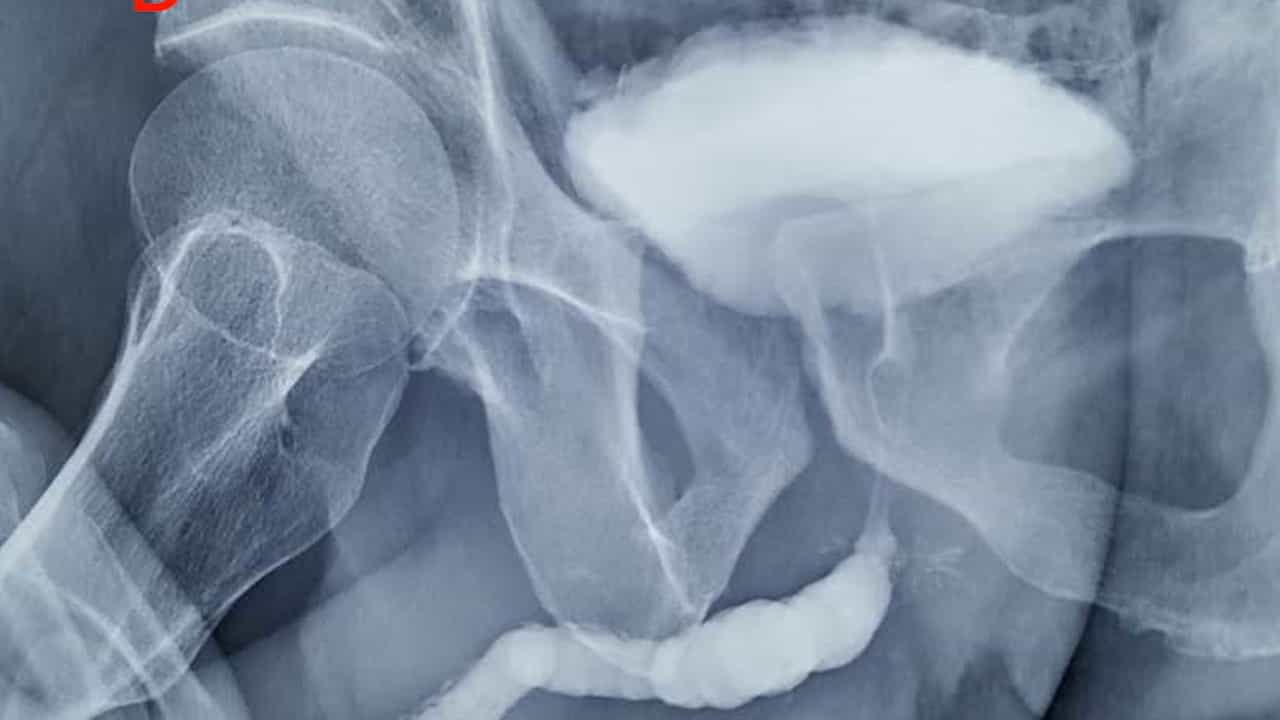
Thirty-four boys with pelvic fracture urethral strictures underwent 35 repairs: 23 in the primary group (initial suprapubic cystostomy, but no urethral repair) and 12 in the re-do group (previously failed attempt(s) at urethroplasty elsewhere). The median age at operation and stricture length was 8.4 years and 3 cm in the primary and 9 years and 5.4 cm in the re-do group, respectively. Anastomotic urethroplasty was performed wherever possible, or failing this a substitution urethroplasty. Median follow up was 9 years for primary group and 8 years for re-do group.
Results:
Primary group: urethroplasty was successful in 22/23, with 10 by perineal and 13 by additional transpubic approach. Two have stress incontinence. Erectile function is unchanged in all and upper tracts are maintained. One had recurrent stricture. Re-do group (12 including 1 recurrence from primary group): anastomotic urethroplasty was done in 5 and substitution urethroplasty in 7. Patients needing substitution had long stricture (>5 cm), stricture extending to distal bulb, or high riding bladder neck. All patients are voiding urethrally. Two patients with substitution required dilatation for early re-stenosis. One appendix substitution required delayed revision. Two have stress incontinence. Erectile function was unaffected. Upper tracts are maintained.
Conclusions:
Anastomotic urethroplasty was successful in over 95% of primary cases. In re-do cases it was viable in only 41% of cases; the rest required substitution urethroplasty. Urethral substitution also gave acceptable results.
Related Concept Videos
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:16
Urethra
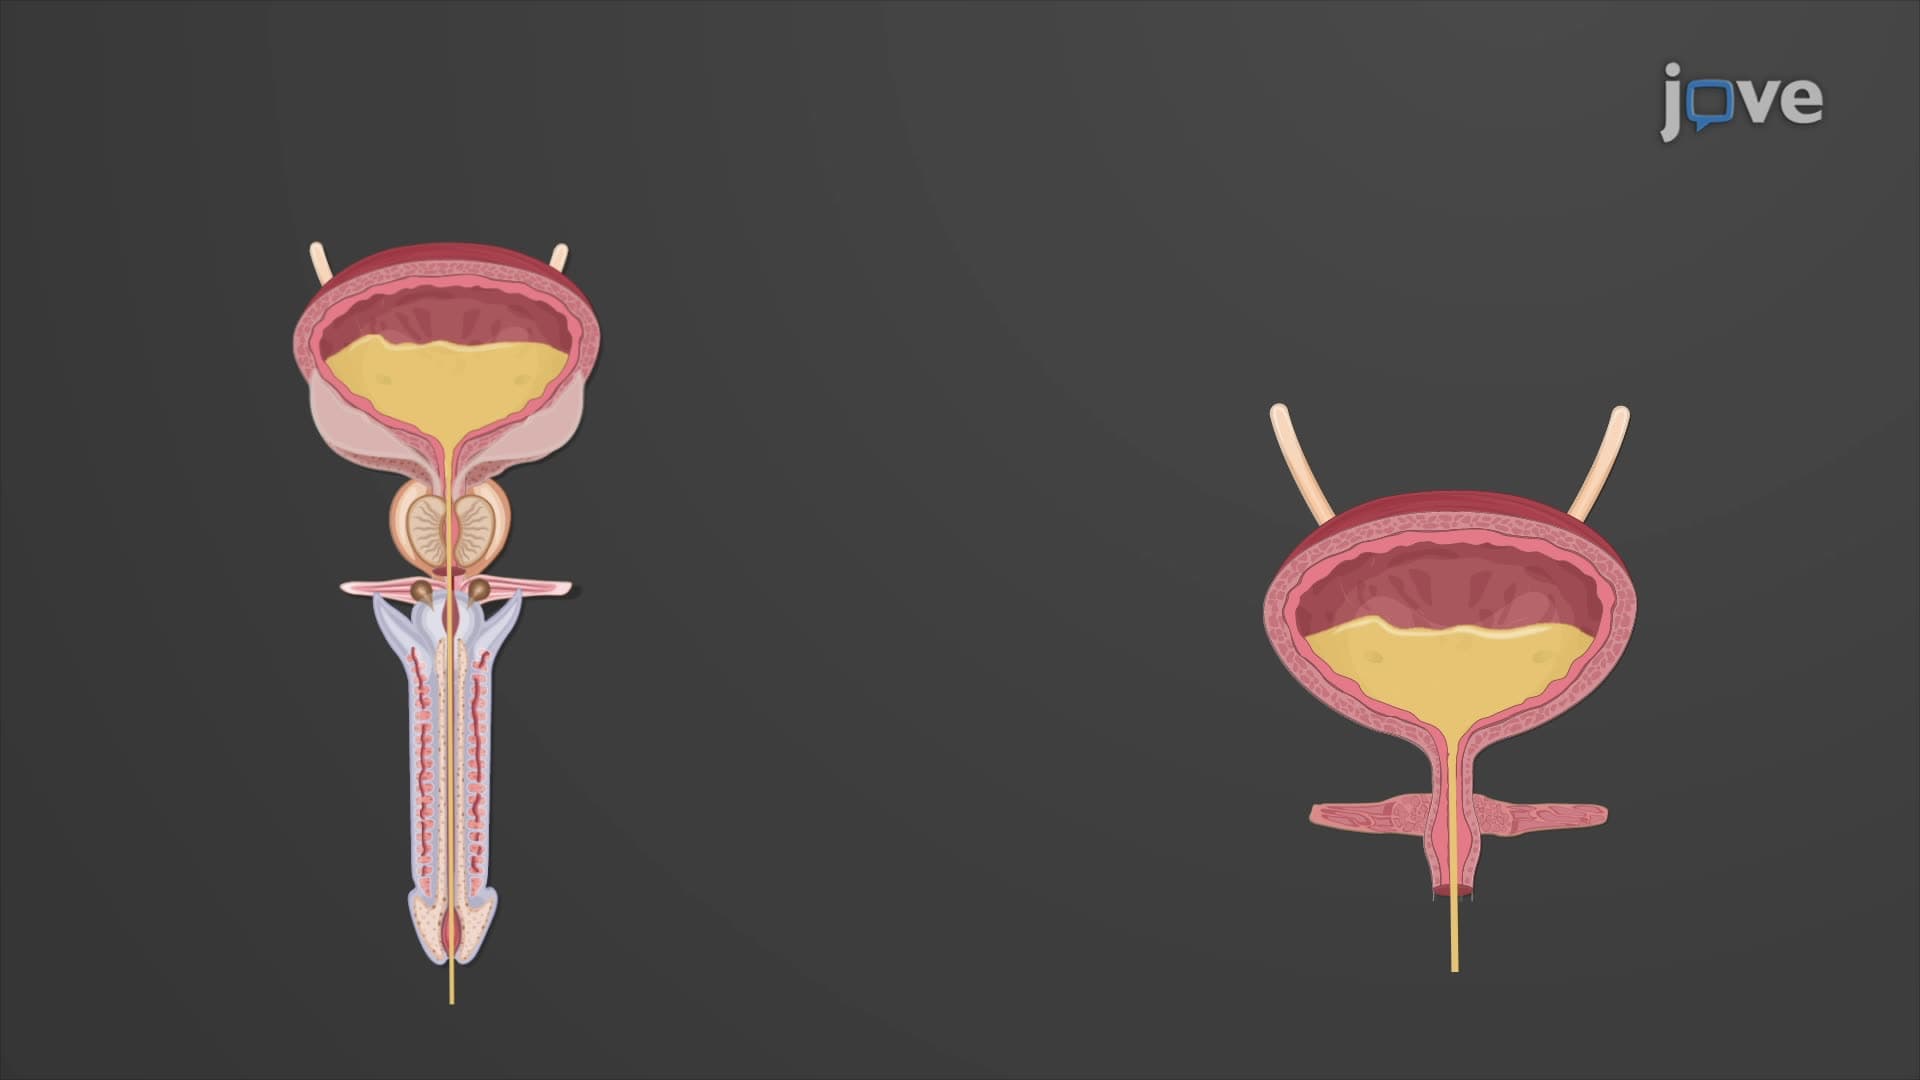
The anatomy of the urethra differs between males and females. In females, the urethra is short, measuring about 3–4 cm in length, and opens anterior to the vaginal opening. In males, the urethra is longer and passes through the penis, serving dual purposes: expelling urine and ejaculating semen. The male urethra is...
 01:25
Urinary Tract Calculi VI: Surgical Management
 01:26
Urinary Tract Calculi II: Pathophysiology and Clinical Manifestations
 01:22
Ureters
 01:19
Anatomy of the Genitourinary System II: Bladder and Urethra