Related Experiment Video
Updated: Jun 2, 2026


Laparoscopic Choledochal Cyst Excision and Roux-en-Y Choledochojejunostomy in Adults
Published on: February 28, 2025
Laparoscopic management of juvenile cystic adenomyoma: four cases
Alka Kriplani1, Reeta Mahey, Nutan Agarwal
1Department of Obstetrics and Gynecology, All India Institute of Medical Sciences, New Delhi, India. kriplanialka@gmail.com

Study Objective:
To highlight a recently identified rare cause of severe dysmenorrhea in young patients with poor response to medical management.
Design:
Evidence obtained from several timed series with or without intervention (Canadian Task Force classification II-3).
Setting:
Tertiary care referral hospital.
Patients:
Four young (age, 16-24 years) nulliparous patients with juvenile cystic adenoma with severe secondary dysmenorrhea with poor response to medical management.
Intervention:
Laparoscopic resection of the cystic adenomyoma.
Measurements And Main Results:
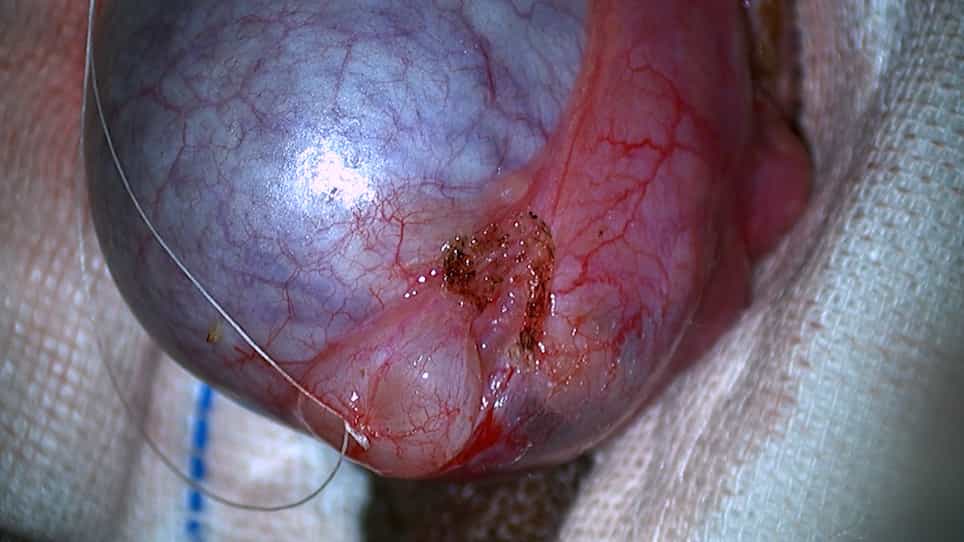
Complete resection of the cystic adenomyoma was performed laparoscopically in all patients. The lesion was uncapsulated (unlike myoma) and locally defined to the uterine myometrium (unlike diffuse adenomyosis), and there was chocolate-colored blood in the cavity. No other müllerian anomaly was observed in any patient. Histopathologic analysis revealed features suggestive of adenomyosis in all cases. After surgery, dysmenorrhea resolved completely in all patients. Compared with preoperative visual analog scores, significant improvement was observed at the first menstrual cycle after surgery. Patients are being followed up every 3 months for a minimum of 12 months to detect development of dysmenorrhea or any other menstrual disorder.
Conclusion:
Juvenile cystic adenomyosis is a rare cause of severe dysmenorrhea. However, it should be included in the differential diagnosis in patients with dysmenorrhea with poor response to medical treatment. All patients reported in the literature and in our series were younger than 30 years, which can be considered as an arbitrary cutoff point to differentiate juvenile from adult cystic adenomyosis. It can be considered a new type of müllerian anomaly that manifests as a noncommunicating accessory uterine cavity lined with endometrium and with an otherwise normal uterus. Surgery is the only therapeutic option for these patients. Minimally invasive surgery in expert hands is advisable to preserve fertility.
Related Concept Videos
 01:28
Urologic Endoscopic Procedure: Cystoscopic Examination
 01:25
Urinary Tract Calculi VI: Surgical Management