Related Experiment Video
Updated: Oct 2, 2026
Physiology Lab Demonstration: Glomerular Filtration Rate in a Rat
Published on: July 26, 2015
[Glomerular function and urine acidification in chronic renal diseases]
1Department of Medicine, Kidney Center, Tokyo Women's Medical College, Japan.

Abstract:
Intravenous sodium bicarbonate (NaHCO3) infusion test was performed in 26 patients with chronic glomerulonephritis (CGN) and 16 with distal renal tubular acidosis (dRTA) in order to evaluate urinary acidifying capacity in chronic renal diseases. Comparative studies with glomerular filtration were planned, so that the patients with CGN were divided by creatinine clearance (Ccr) into 3 groups (G-I greater than or equal to 70, 30 less than or equal to G-II less than 70, G-III less than 30 ml/min). Proximal tubular bicarbonate (HCO3) reabsorption rate increased in CGN as Ccr decreased. Urine to blood carbon dioxide tension gradient (U-B PCO2) was above 30 mmHg in controls and below 20 mmHg in dRTA. In patients with CGN, urine HCO3 concentration (UHCO3) did not increase during NaHCO3 loading as Ccr decreased. However, U-B PCO2 rose above 20 mmHg, when UHCO3 was above 50 ml/min. Fishberg concentrating test was also performed in 15 patients with CGN and 6 with dRTA so that the relationship between urinary concentrating ability and urine acidification might be evaluated. While both functions were decreased in dRTA, U-B PCO2 in alkaline urine remained above 20 mmHg in CGN associated with moderate renal dysfunction (Ccr greater than or equal to 30 ml/min) despite decreased maximal urine osmolality. Intravenous furosemide (FM) injection test was carried out in 8 patients with chronic renal failure (CRF) and 3 with dRTA. Minimal urine pH fell below 5.5 and net acid excretion (NAE) increased in controls, whereas these responses were not seen in dRTA. In CRF, urine pH generally decreased below 5.5 and those who had a similar response to FM as dRTA, seemed to have more severe disturbance of the distal acidification. In conclusion, U-B PCO2 in alkaline urine and lowered urine pH in FM loading appeared to be a useful index of distal tubular acid excretion in patients with renal dysfunction. In CGN with moderate renal dysfunction (Ccr greater than or equal to 30 ml/min), urinary acidifying capacity remained normal in comparison with decreased urine concentrating ability.


Related Concept Videos
 01:29
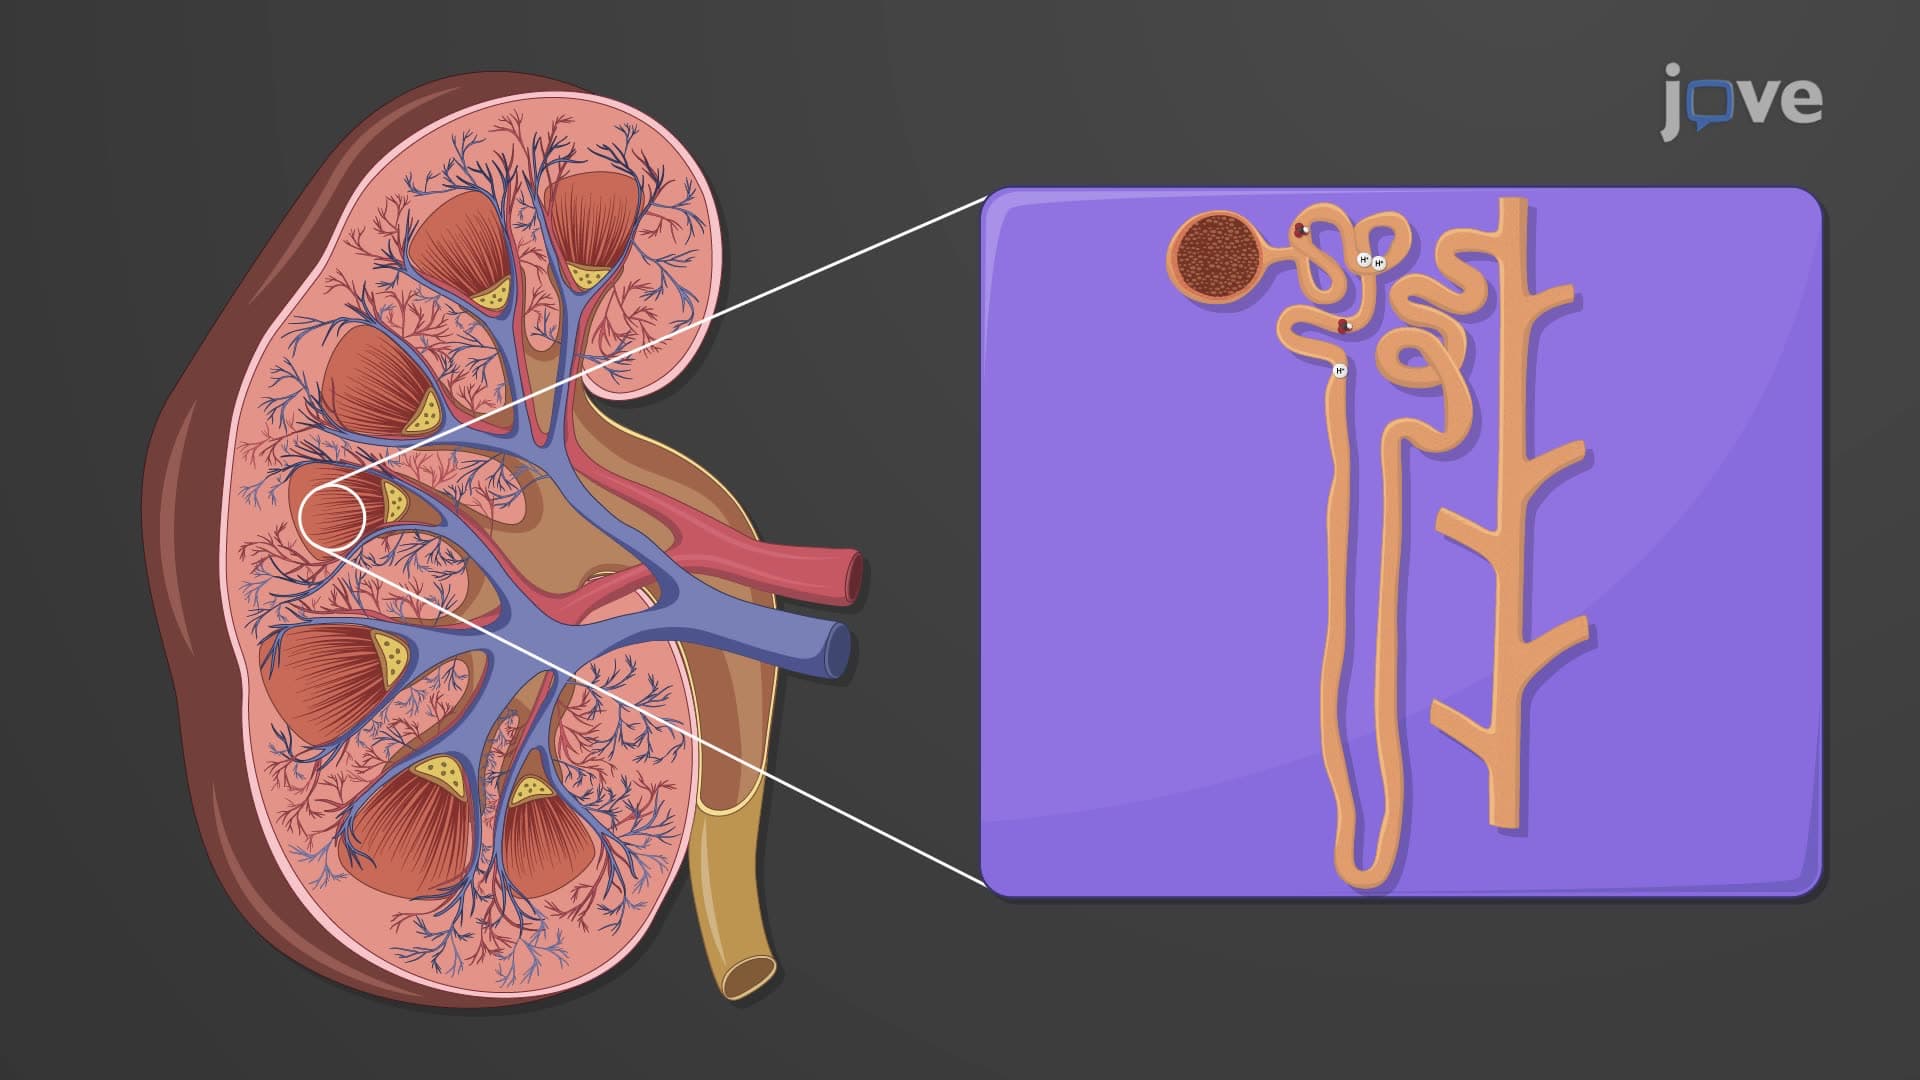
Renal Regulation of Acid-Base Balance
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...
 01:22
Renal Drug Excretion: Effect of Urine pH, Flow Rate, and Drug pKa
The pKa of a drug,...
 01:17
Factors Affecting Renal Clearance: Renal Impairment
One condition associated with renal failure is uremia. Uremia is characterized by impaired glomerular filtration and fluid accumulation in the body. This condition hinders the renal clearance of drugs, resulting in drug accumulation and potential...
 01:25
Drug Dosing in Renal Diseases: Measurement of Glomerular Filtration Rate
 01:28
Drug Dosing in Renal Diseases: Estimation of Glomerular Filtration Rate Based on Serum Creatinine Concentration
 01:28
Chronic Kidney Disease III: Interprofessional Care