Related Experiment Video
Updated: Jun 1, 2026
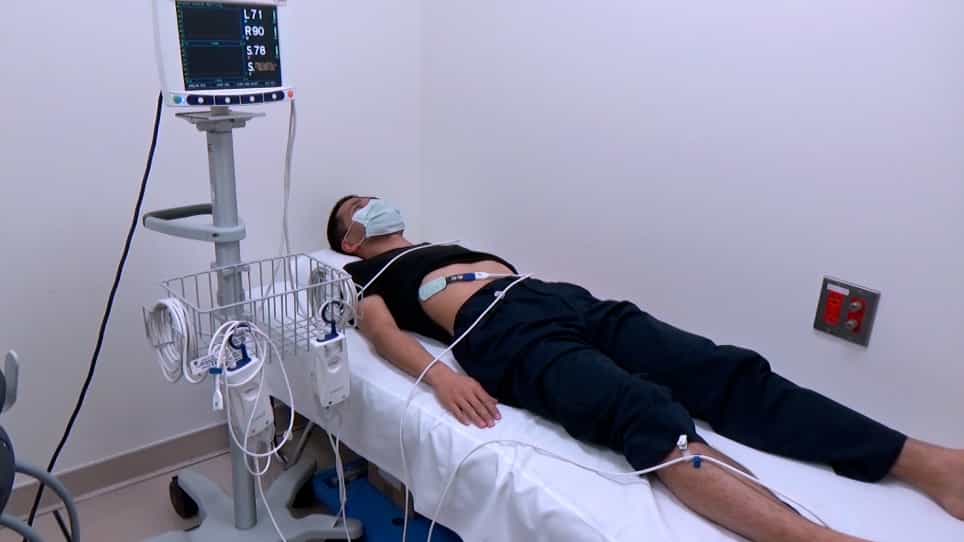
Measurement of Tissue Oxygenation Using Near-Infrared Spectroscopy in Patients Undergoing Hemodialysis
Published on: October 2, 2020
Fluctuations of haemoglobinaemia in chronic haemodialysis patients
J De Meester1, B Maes, A De Vriese
1Department of Nephrology AZ Nikolaas, Sint-Niklaas, Bonheiden. Johan.DeMeester@aznikolaas.be

In March 2008 and June 2009, an ad hoc working group of nephrologists discussed the status of anaemia therapy with erythropoiesis-stimulating agents [ESA] in patients on chronic haemodialysis, the phenomenon of fluctuations of haemoglobinaemia, and the need for individualisation of ESA treatment. The working group put together the following statements: (1) ESAs increase the haemoglobin concentration and adaptations of the ESA dose adjust the response according to a negative-feedback loop. The long lag time between an ESA dose change and its effect on erythropoiesis is cumbersome. The optimal haemoglobin target concentration is different for every haemodialysis patient; the lowest haemoglobin concentration upon which one could consistently demonstrate a positive subjective and objective clinical benefit in chronic dialysis is 11 g/dL, in contrast to the lowest haemoglobin concentration of 10 g/dL recommended in the current EMEA label for ESAs. (2) Intra-individual fluctuation of haemoglobinaemia over time is unavoidable, not only due to the ESA dose/haemoglobin response interaction, but also, and more importantly, due to the occurrence of acute illnesses and exacerbations of co-morbid conditions. Many different methodologies to characterise haemoglobin variability have been described but there is currently no universally applied definition of the phenomenon. (3) An impact of the haemoglobin level and the amplitude of the haemoglobin fluctuations on patient outcome has been observed. Without disclosing any causal relationship, worse outcomes were associated with haemoglobin fluctuations around the lower target level, but later on, more simply linked to the relative time spent below the haemoglobin concentration of 11 g/dL and to the administration of inappropriately high ESA doses in order to achieve the recommended haemoglobin target range. A plausible mechanism might be that acute illnesses blunt the patients' basal ESA sensitivity; this leads to subnormal and/or varying haemoglobin levels, currently initiating an ESA dose increase. The longer it takes the patient to recover from the acute illness, the more the prolongation of the clinically poor condition is to some extent maintained by the persistence of low haemoglobinaemia and/or by the administration of high ESA doses, and, as such, on their turn possibly contributing to an ultimate poor outcome. In the absence of clinical trials, recommendations should be offered how to proceed with the administration of ESAs as optimal as possible in periods of clinical instability.
In March 2008 and June 2009, an ad hoc working group of nephrologists discussed the status of anaemia therapy with erythropoiesis-stimulating agents [ESA] in patients on chronic haemodialysis, the phenomenon of fluctuations of haemoglobinaemia, and the need for individualisation of ESA treatment. The working group put together the following statements: (1) ESAs increase the haemoglobin concentration and adaptations of the ESA dose adjust the response according to a negative-feedback loop. The long lag time between an ESA dose change and its effect on erythropoiesis is cumbersome. The optimal haemoglobin target concentration is different for every haemodialysis patient; the lowest haemoglobin concentration upon which one could consistently demonstrate a positive subjective and objective clinical benefit in chronic dialysis is 11 g/dL, in contrast to the lowest haemoglobin concentration of 10 g/dL recommended in the current EMEA label for ESAs. (2) Intra-individual fluctuation of haemoglobinaemia over time is unavoidable, not only due to the ESA dose/haemoglobin response interaction, but also, and more importantly, due to the occurrence of acute illnesses and exacerbations of co-morbid conditions. Many different methodologies to characterise haemoglobin variability have been described but there is currently no universally applied definition of the phenomenon. (3) An impact of the haemoglobin level and the amplitude of the haemoglobin fluctuations on patient outcome has been observed. Without disclosing any causal relationship, worse outcomes were associated with haemoglobin fluctuations around the lower target level, but later on, more simply linked to the relative time spent below the haemoglobin concentration of 11 g/dL and to the administration of inappropriately high ESA doses in order to achieve the recommended haemoglobin target range. A plausible mechanism might be that acute illnesses blunt the patients' basal ESA sensitivity; this leads to subnormal and/or varying haemoglobin levels, currently initiating an ESA dose increase. The longer it takes the patient to recover from the acute illness, the more the prolongation of the clinically poor condition is to some extent maintained by the persistence of low haemoglobinaemia and/or by the administration of high ESA doses, and, as such, on their turn possibly contributing to an ultimate poor outcome. In the absence of clinical trials, recommendations should be offered how to proceed with the administration of ESAs as optimal as possible in periods of clinical instability.

Related Concept Videos
 01:24
Hemodialysis II: Procedure and Complications
 01:25
Hemodialysis III: Nursing Management
 01:24
Chronic Kidney Disease II: Clinical Manifestations
 01:27
Dialysis
Acute kidney injury develops suddenly and can be caused by pre-renal causes (e.g., hypovolemia, shock), intrinsic renal causes (e.g., acute tubular necrosis), or post-renal causes (e.g., urinary obstruction). In contrast, chronic renal failure progresses gradually over time and is often...
 01:15
Dialysis
 01:26
Effect of Hepatic Disease on Pharmacokinetics: Drug Dosing and Hepatic Blood Flow