Related Experiment Video
Updated: Jun 1, 2026
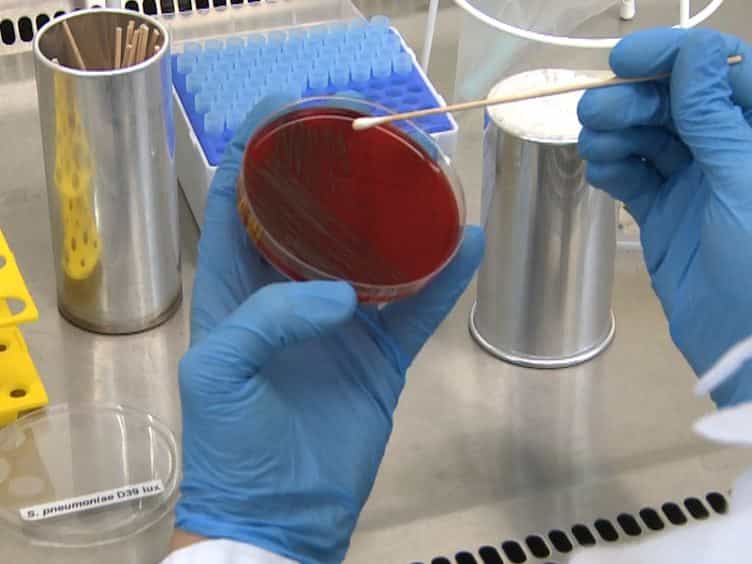
Following in Real Time the Impact of Pneumococcal Virulence Factors in an Acute Mouse Pneumonia Model Using Bioluminescent Bacteria
Published on: February 23, 2014
Diagnosis and management of community-acquired pneumonia in adults
Richard R Watkins1, Tracy L Lemonovich
1Akron General Medical Center, OH 44302, USA. rwatkins@agmc.org

Abstract:
Community-acquired pneumonia is diagnosed by clinical features (e.g., cough, fever, pleuritic chest pain) and by lung imaging, usually an infiltrate seen on chest radiography. Initial evaluation should determine the need for hospitalization versus outpatient management using validated mortality or severity prediction scores. Selected diagnostic laboratory testing, such as sputum and blood cultures, is indicated for inpatients with severe illness but is rarely useful for outpatients. Initial outpatient therapy should include a macrolide or doxycycline. For outpatients with comorbidities or who have used antibiotics within the previous three months, a respiratory fluoroquinolone (levofloxacin, gemifloxacin, or moxifloxacin), or an oral beta-lactam antibiotic plus a macrolide should be used. Inpatients not admitted to an intensive care unit should receive a respiratory fluoroquinolone, or a beta-lactam antibiotic plus a macrolide. Patients with severe community-acquired pneumonia or who are admitted to the intensive care unit should be treated with a beta-lactam antibiotic, plus azithromycin or a respiratory fluoroquinolone. Those with risk factors for Pseudomonas should be treated with a beta-lactam antibiotic (piperacillin/tazobactam, imipenem/cilastatin, meropenem, doripenem, or cefepime), plus an aminoglycoside and azithromycin or an antipseudomonal fluoroquinolone (levofloxacin or ciprofloxacin). Those with risk factors for methicillin-resistant Staphylococcus aureus should be given vancomycin or linezolid. Hospitalized patients may be switched from intravenous to oral antibiotics after they have clinical improvement and are able to tolerate oral medications, typically in the first three days. Adherence to the Infectious Diseases Society of America/American Thoracic Society guidelines for the management of community-acquired pneumonia has been shown to improve patient outcomes. Physicians should promote pneumococcal and influenza vaccination as a means to prevent community-acquired pneumonia and pneumococcal bacteremia.
Related Concept Videos
 01:28
Pneumonia IV: Management
Bacterial Pneumonia Treatment
For bacterial pneumonia, antibiotics serve as the cornerstone of therapy. Initial treatment often begins with empirical antibiotics, tailored to the anticipated causative organism and adjusted based on culture results. Key antibiotic choices include:
 01:30
Pneumonia V: Nursing management and Prevention
The nurse must practice strict medical asepsis and adhere to infection control guidelines to minimize healthcare-associated infections.
Enhance airway patency
Position the patient correctly to facilitate drainage of the affected lung segments. Manual or mechanical percussion and vibration can also be employed.
 01:29
Pneumonia I: Introduction
 01:30
Pneumonia I: Introduction
Risk Factors
Various factors influence the likelihood of developing pneumonia. Age plays a crucial role, with infants, children under two, and individuals over 65 at increased risk due to their...
 01:30
Pneumonia III: Complications and Assessment
 01:14
Atypical Pneumonia