Related Experiment Video
Updated: May 31, 2026
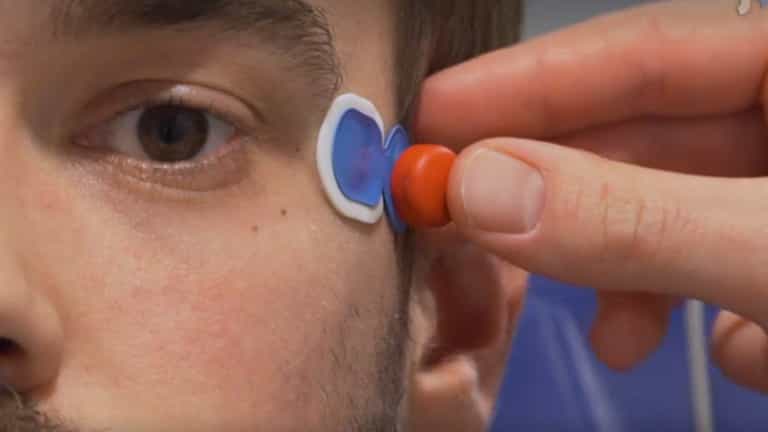

A Computerized Test Battery to Study Pharmacodynamic Effects on the Central Nervous System of Cholinergic Drugs in Early Phase Drug Development
Published on: February 11, 2019
Effect of oxybutynin and imidafenacin on central muscarinic receptor occupancy and cognitive function: a monkey PET
Shigeyuki Yamamoto1, Shuji Maruyama, Yoshihiko Ito
1Karolinska Institutet, Department of Clinical Neuroscience, Psychiatry Section, Stockholm, Sweden.

Abstract:
Although antimuscarinic agents are widely used to treat overactive bladder (OAB), they have been shown to induce side effects including dry mouth and cognitive impairment. The present study was aimed to investigate the effects of antimuscarinic agents, oxybutynin and imidafenacin, on temporal changes in cognitive function and central mAChR occupancy in conscious monkeys (Macaca mulatta). Three conscious monkeys underwent positron emission tomography (PET) scans with a mAChR radioligand N-[(11)C]methyl-3-piperidyl benzilate ([(11)C](+)3-MPB). The scan sequence was pre, and 1, 4, and 24h post oral administration of oxybutynin (0.1-1.0mg/kg) or imidafenacin (0.01-0.1mg/kg). Maximum cognitive impairment was observed 1h post-oxybutynin at oral doses of 0.3 and 1.0mg/kg, in a dose-dependent manner, and oxybutynin produced significant positive correlations between mAChR occupancy and cognitive impairment in the cortices, thalamus, brainstem, and striatum. The most significant correlation was observed in the brainstem, and then cortices. In contrast, imidafenacin did not induce discernible cognitive impairment, despite having obtained some lesser occupancy in cortices and brainstem. We propose that the thresholds of mAChR occupancy to produce cognitive impairment by antimuscarinic agents are ca. 30-40% in cortices and ca. 20-30% in brainstem, and a desirable drug for OAB treatment should not occupy central mAChR above these thresholds.
Insights
Antimuscarinic drugs for overactive bladder can cause cognitive impairment by blocking central muscarinic acetylcholine receptors (mAChR). Imidafenacin showed less cognitive impact than oxybutynin, suggesting lower central mAChR occupancy is key for safer OAB treatments.
Area of Science:
- Neuroscience
- Pharmacology
- Radiochemistry
Background:
- Antimuscarinic agents are common treatments for overactive bladder (OAB).
- These drugs can cause side effects like dry mouth and cognitive impairment.
- Central muscarinic acetylcholine receptor (mAChR) occupancy is implicated in these side effects.
Purpose of the Study:
- To investigate the effects of oxybutynin and imidafenacin on cognitive function and central mAChR occupancy in conscious monkeys.
- To determine the relationship between mAChR occupancy and cognitive impairment.
- To identify potential thresholds for central mAChR occupancy to avoid cognitive side effects.
Main Methods:
- Positron emission tomography (PET) scans were performed on three conscious monkeys (Macaca mulatta).
- A mAChR radioligand, N-[(11)C]methyl-3-piperidyl benzilate ([(11)C](+)3-MPB), was used.
- Scans were conducted before and at 1, 4, and 24 hours after oral administration of oxybutynin or imidafenacin.
Main Results:
- Oxybutynin induced dose-dependent cognitive impairment, peaking at 1 hour post-administration.
- Significant positive correlations were found between mAChR occupancy and cognitive impairment in various brain regions, particularly the brainstem and cortices.
- Imidafenacin did not cause significant cognitive impairment, despite some central mAChR occupancy.
Conclusions:
- Central mAChR occupancy thresholds for cognitive impairment are approximately 30-40% in cortices and 20-30% in the brainstem.
- Drugs for OAB treatment should ideally maintain central mAChR occupancy below these thresholds to minimize cognitive side effects.
- This study provides insights into the neuropharmacology of antimuscarinic agents and OAB treatment.


Related Concept Videos
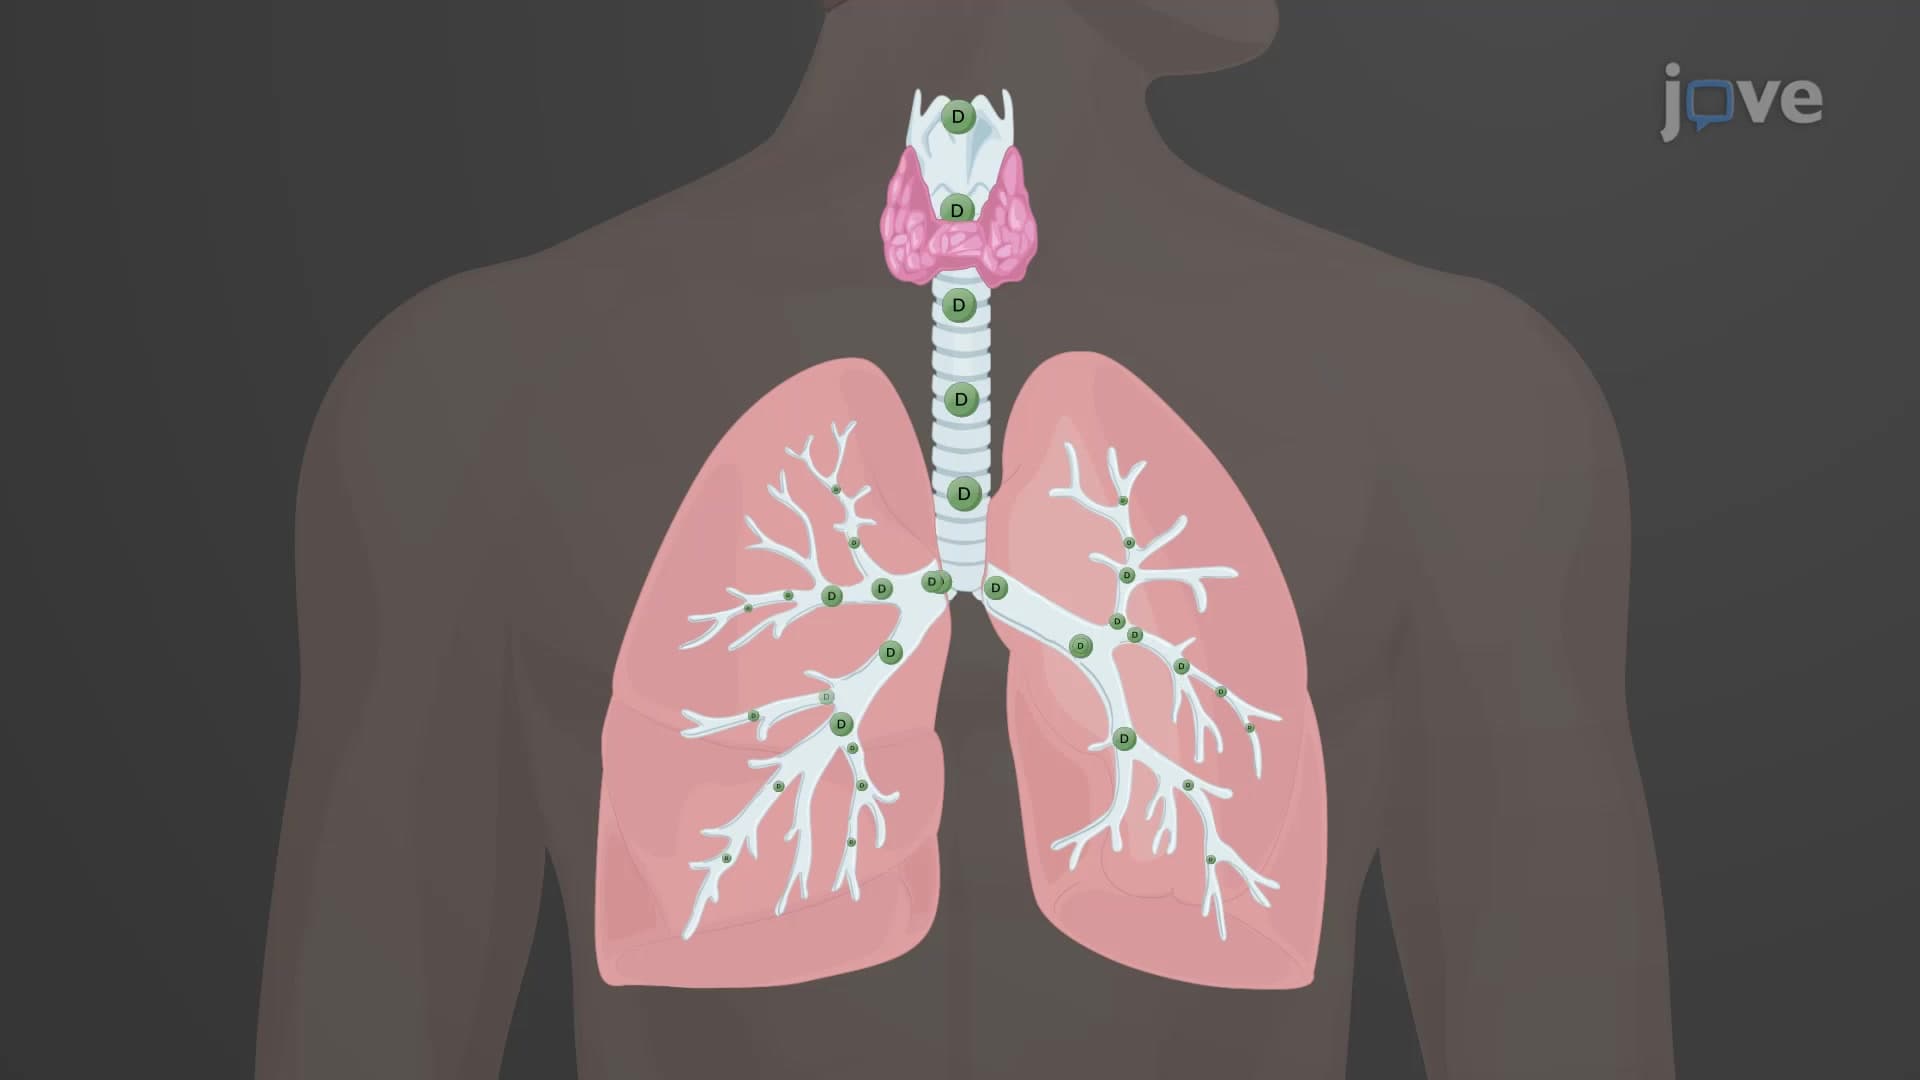 01:28
Cholinergic Antagonists: Pharmacological Actions
Gastrointestinal Effects: Antimuscarinics reduce gut contractions, increase gastric emptying, and slow intestinal transit. They partly inhibit gastric acid secretion...
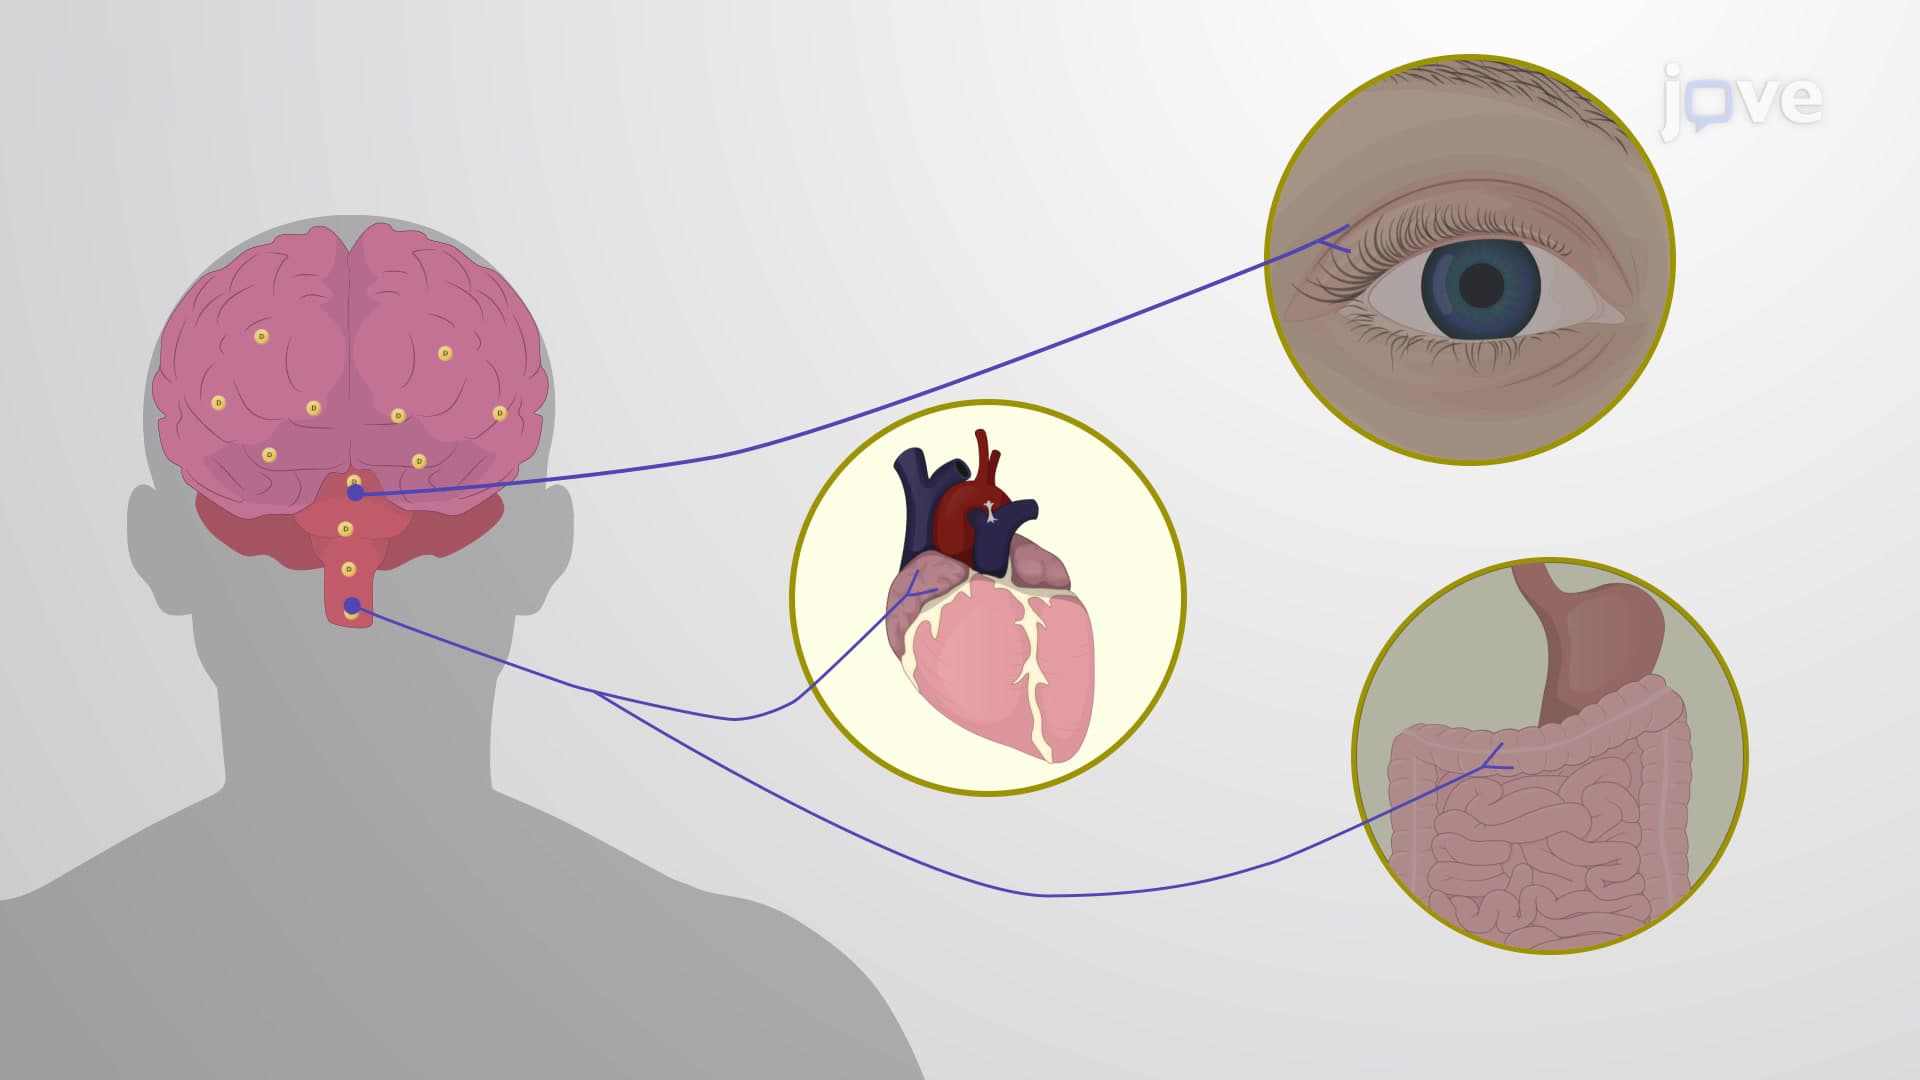 00:59
Direct-Acting Cholinergic Agonists: Pharmacological Actions
 01:26
Cholinergic Antagonists: Therapeutic Uses
Respiratory Tract: Ipratropium, aclidinium, and tiotropium treat asthma, chronic bronchitis, and chronic obstructive pulmonary disease (COPD). They protect against bronchoconstriction caused by irritants like cigarette smoke, sulfur dioxide, and ozone. They also help reduce nasopharyngeal secretions in common...
 01:24
Cholinergic Antagonists: Pharmacokinetics
 01:11
Direct-Acting Cholinergic Agonists: Therapeutic Uses
 01:31
Direct-Acting Cholinergic Agonists: Pharmacokinetics