Related Experiment Video
Updated: May 31, 2026
Dissection of Single Skeletal Muscle Fibers for Immunofluorescent and Morphometric Analyses of Whole-Mount Neuromuscular Junctions
Published on: August 14, 2021
[Histochemical findings of and fine structural changes in motor endplates in diseases with neuromuscular transmission
Toshiro Yoshimura1, Masakatsu Motomura, Mitsuhiro Tsujihata
1Unit of Rehabilitation Sciences, Department of Medical and Dental Sciences, Nagasaki University Graduate School of Biomedical Sciences, Nagasaki, Japan.

Abstract:
We herein review the histochemical findings and fine structural changes of motor endplates associated with diseases causing neuromuscular transmission abnormalities. In anti-acetylcholine receptor (AChR) antibody-positive myasthenia gravis (MG), type 2 fiber atrophy is observed, and the motor endplates show a reduction in the nerve terminal area, simplification of the postsynaptic membrane, decreased number of acetylcholine receptors, and deposition of immune complexes. In anti-MuSK antibody-positive MG, the fine structure shows a decrease in the postsynaptic membrane length, but the secondary synaptic cleft is preserved. There is no decrease in the number of AChRs, and there are no deposits of immune complexes at the motor endplates. Patients with Lambert-Eaton myasthenic syndrome show type 2 fiber atrophy, their motor endplates show a decrease in both the mean postsynaptic area and postsynaptic membrane length in the brachial biceps muscle. Congenital myasthenic syndrome with episodic apnea is characterized only by small-sized synaptic vesicles; the postsynaptic area is preserved. In subjects with congenital myasthenic syndrome with acetylcholinesterase deficiency, quantitative electron microscopy reveals a significant decrease in the nerve terminal size and presynaptic membrane length; further, the Schwann cell processes extend into the primary synaptic cleft, and partially or completely occlude the presynaptic membrane. The postsynaptic folds are degenerated, and associated with pinocytotic vesicles and labyrinthine membranous networks. Patients with slow-channel congenital myasthenia syndrome show type 1 fiber predominance, and their junctional folds are typically degenerated with widened synaptic space and loss of AChRs. Patients with AChR deficiency syndrome caused by recessive mutations in AChR subunits also show type 1 fiber predominance, and while most junctional folds are normal, some are simplified and have smaller than normal endplates. Rapsin and MuSK mutations cause type 1 fiber predominance, and the small postsynaptic area is associated with AChR decrease.
More Related Videos
 12:18
The Neuromuscular Junction: Measuring Synapse Size, Fragmentation and Changes in Synaptic Protein Density Using Confocal Fluorescence Microscopy
Published on: December 26, 2014
 11:03
Characterization of Neuromuscular Junctions in Mice by Combined Confocal and Super-Resolution Microscopy
Published on: December 8, 2021
Related Concept Videos
 01:11
Alterations in Muscle Tone lll
 01:12
Alterations in Muscle Tone ll
 01:15
Myasthenia Gravis: Diagnostic Tests
The edrophonium test is a diagnostic tool for myasthenia gravis. It involves...
 01:19
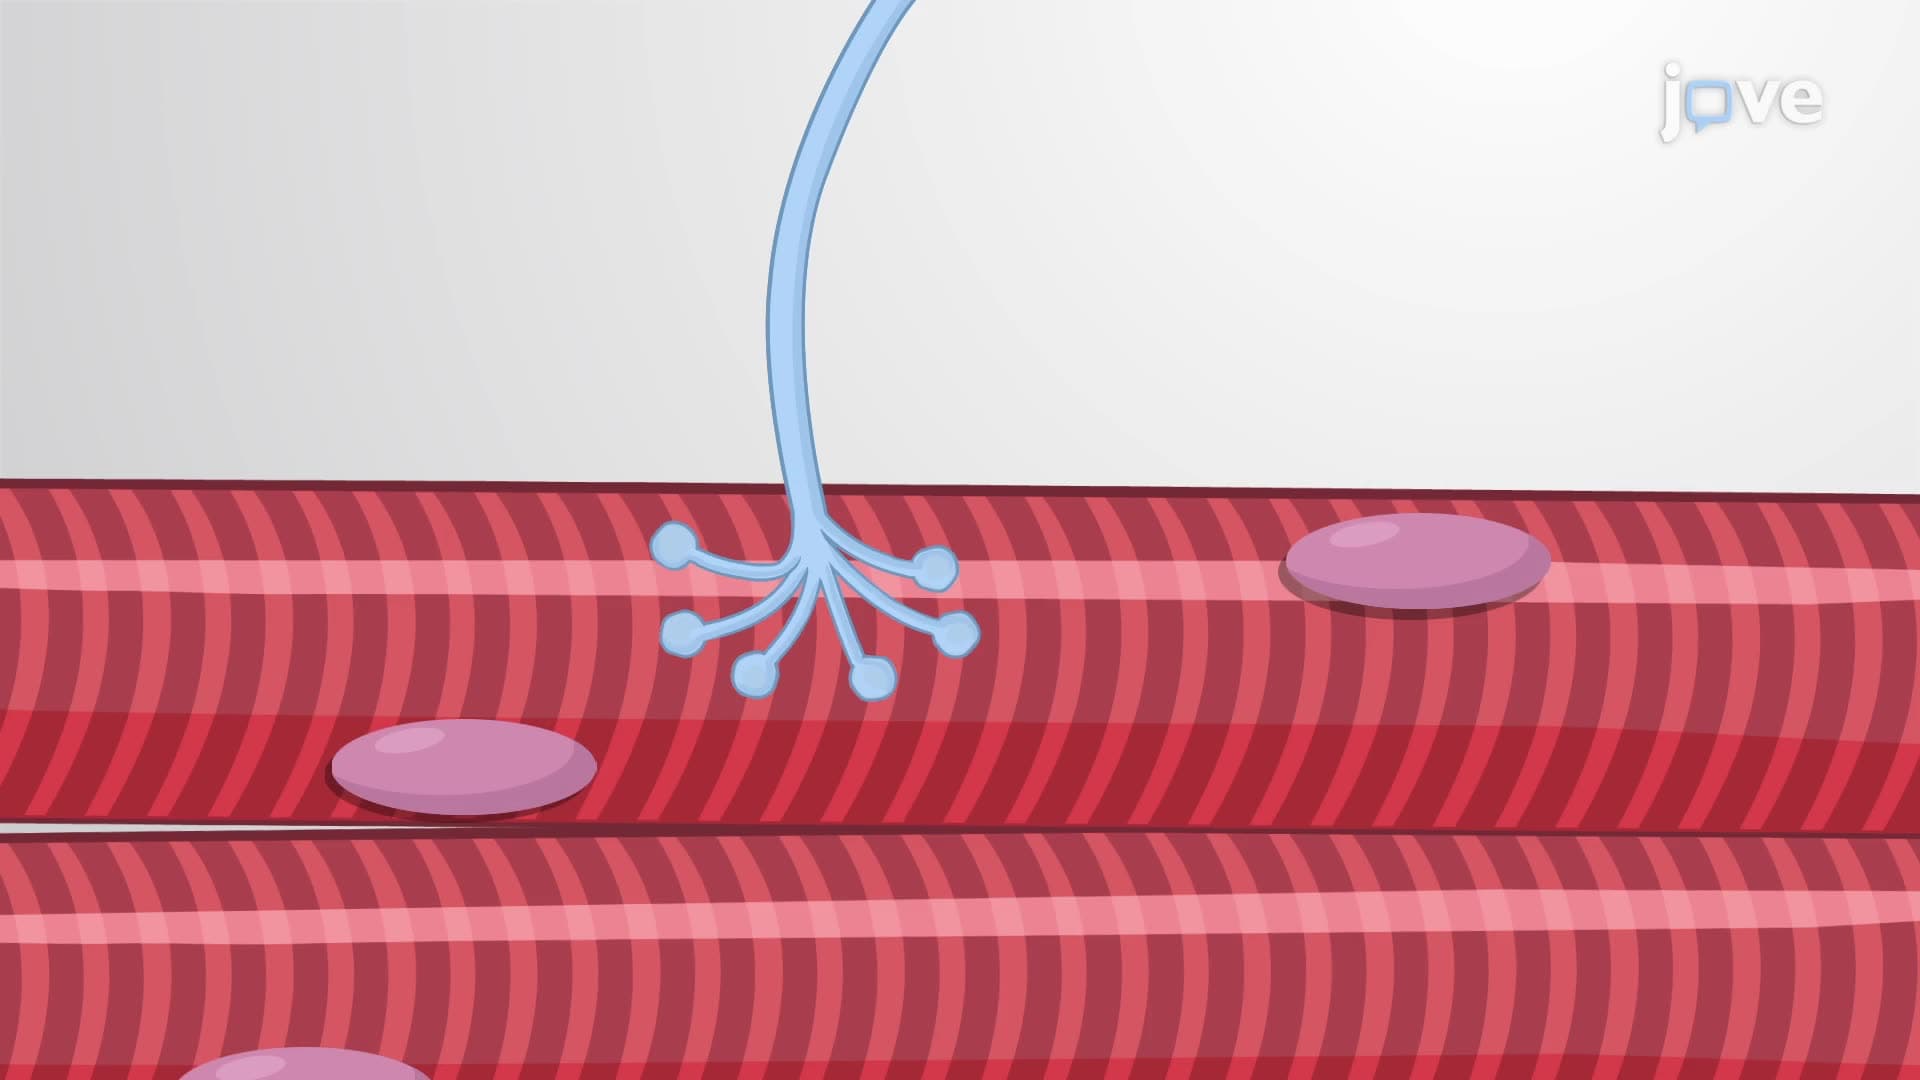
The Neuromuscular Junction
 01:22
Myasthenia Gravis ll: Pathophysiology
 01:29
Neuromuscular Junction And Blockade