Related Experiment Video
Updated: May 30, 2026

Cell-based Assay Protocol for the Prognostic Prediction of Idiopathic Scoliosis Using Cellular Dielectric Spectroscopy
Published on: October 16, 2013
Risk of progression of degenerative lumbar scoliosis
Jun-Yeong Seo1, Kee-Yong Ha, Tae-Hyok Hwang
1Department of Orthopaedic Surgery, College of Medicine, The Catholic University of Korea, Seoul, Korea.

Object:
In this paper the authors' goal was to determine the factors associated with the progression of degenerative lumbar scoliosis (DLS).
Methods:
Twenty-seven patients (3 men and 24 women; mean age 64.9 years) with more than 10° of lumbar scoliosis at baseline were monitored for a mean period of 10 years. The radiological evaluation included measurement of the scoliosis angle using the Cobb method, the direction of the scoliosis, the relationship between the intercrest line and the L-5 vertebra, lateral listhesis, segmental angle, distance from the center of the sacral line to the apical vertebra, degenerative listhesis anteriorly or posteriorly or both, and lordosis angle. In addition, the lateral osteophyte difference, disc index, and severity of osteoporosis were measured. The pain and disability outcomes were assessed using the visual analog scale and the Oswestry Disability Index (ODI) relative to severity of the angle of scoliosis.
Results:
The mean initial and final scoliosis angles were 14° ± 5.4° and 25° ± 8.5°, respectively. The initial disc index at the L-3 vertebra (Spearman ρ = 0.7, p < 0.001), the sum of the segmental wedging angles above and below the L-3 vertebra (ρ = 0.6, p < 0.001), and the initial disc index at the apical vertebra (ρ = 0.6, p < 0.001) were correlated with the last follow-up angle of the scoliosis. By contrast, there was no statistically significant correlation between the initial segmental angles at L2-3 and L3-4 and the final follow-up scoliosis angle (ρ = 0.2, p = 0.67; and ρ = 0.1, p = 0.22; respectively). When the authors separated the patients into 3 groups according to the sum of the segmental angles above and below L-3 (< 5°, 5° to 10°, and > 10°), they found that 3 (42.9%) of 7, 8 (66.7%) of 12, and 6 (75.0%) of 8 patients in the 3 groups showed increases of greater than 10° in scoliosis angle. The mean distance from the center of the sacral line to the apical vertebra was 36.0 ± 9.7 mm, and the distance correlated with the measurement of the last follow-up angle of the scoliosis (ρ = 0.6, p < 0.001). The mean angle of the scoliosis was significantly greater when the intercrest line passed through the L-5 or L4-5 disc space than when the line passed through the L-4 vertebral body (31.4° ± 7.9° vs 21.8° ± 6.7°, p = 0.01). The ODI correlated with the measurement of the angle of the scoliosis (ρ = 0.6, p < 0.001). Age, sex, osteoporosis, the direction of the scoliosis, listhesis of coronal and sagittal planes, the lateral osteophyte difference, and the vertebral body index did not correlate with curve progression.
Conclusions:
The findings of this study demonstrated that the progression of DLS was affected by the relationship between the intercrest line and the L-5 vertebra. When L-5 was deep seated, progression of DLS was found. Asymmetrical change in the disc space above and below the L-3 or apical vertebra may also be an important predictor of curve progression.
More Related Videos
 04:19
Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
 07:12
Clinical Efficacy of an Innovative Multidimensional Traction Therapy in Moderate Adolescent Idiopathic Scoliosis
Published on: February 10, 2026
Related Concept Videos
 01:27
Degenerative Disc Disease I: Introduction
 01:23
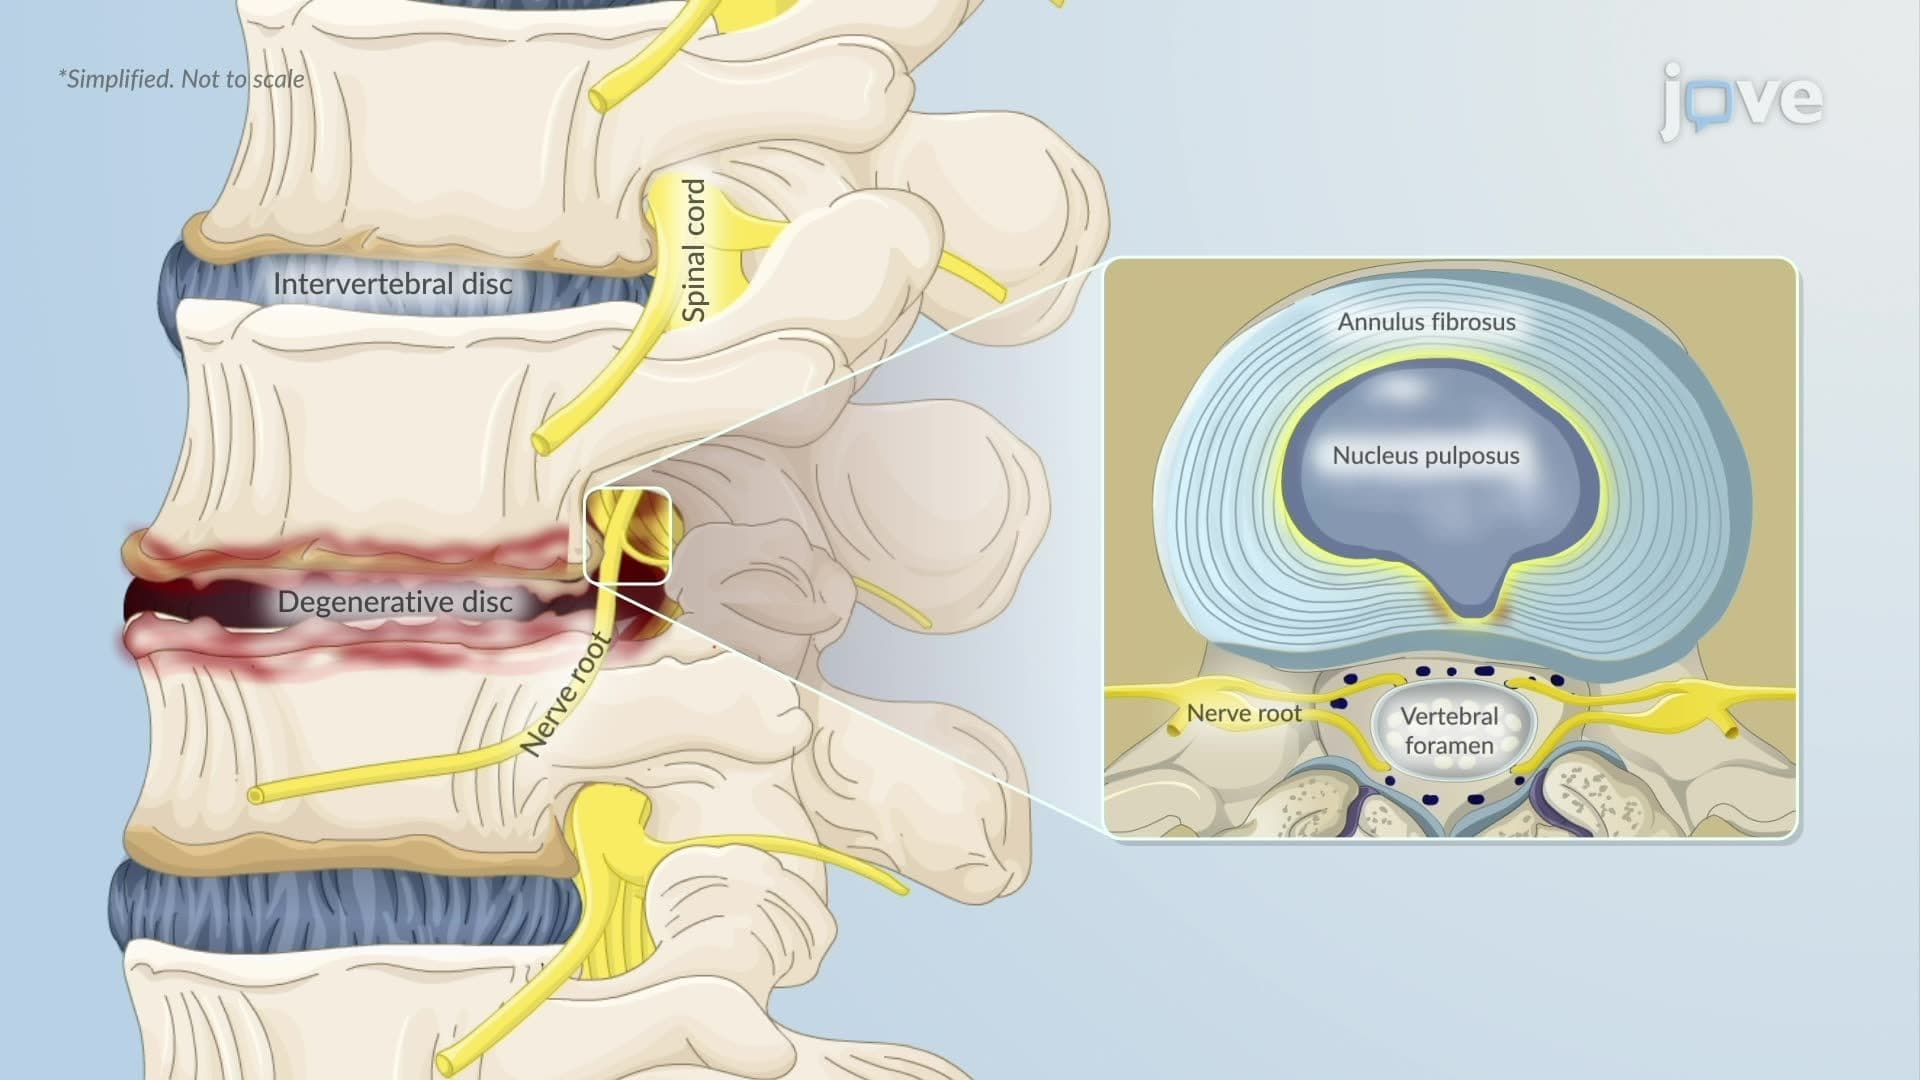
Degenerative Disc Disease ll: Pathophysiology