Related Experiment Video
Updated: May 30, 2026

Trabecular Bone Microarchitecture Evaluation in an Osteoporosis Mouse Model
Published on: September 8, 2023
Bone microarchitecture is impaired in adolescent amenorrheic athletes compared with eumenorrheic athletes and
Kathryn E Ackerman1, Taraneh Nazem, Dorota Chapko
1Neuroendocrine Unit, Massachusetts General Hospital and Harvard Medical School, Boston, Massachusetts 02114, USA.

Context:
Bone mineral density (BMD) is lower in young amenorrheic athletes (AA) compared to eumenorrheic athletes (EA) and nonathletic controls and may contribute to fracture risk during a critical time of bone accrual. Abnormal bone microarchitecture is an independent determinant of fracture risk and has not been assessed in young athletes and nonathletes.
Objective:
We hypothesized that bone microarchitecture is impaired in AA compared to EA and nonathletes despite weight-bearing exercise.
Design And Setting:
We conducted this cross-sectional study at the Clinical Research Center of Massachusetts General Hospital.
Subjects And Outcome Measures:
We assessed BMD and bone microarchitecture in 50 subjects [16 AA, 18 EA, and 16 nonathletes (15-21 yr old)] using dual-energy x-ray absorptiometry and high-resolution peripheral quantitative computed tomography.
Results:
Groups did not differ for chronological age, bone age, body mass index, or vitamin D levels. Lumbar BMD Z-scores were lower in AA vs. EA and nonathletes; hip and femoral neck BMD Z-scores were highest in EA. At the weight-bearing tibia, athletes had greater total area, trabecular area, and cortical perimeter than nonathletes, whereas cortical area and thickness trended lower in AA. Trabecular number was lower and trabecular separation higher in AA vs. EA and nonathletes. At the non-weight-bearing radius, trabecular density was lower in AA vs. EA and nonathletes. Later menarchal age was an important determinant of impaired microarchitecture. After controlling for covariates, subject grouping accounted for 18-24% of the variability in tibial trabecular number and separation.
Conclusion:
In addition to low BMD, AA have impaired bone microarchitecture compared with EA and nonathletes. These are the first data to show abnormal bone microarchitecture in AA.


Related Concept Videos
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:40
Bone Remodeling
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...
 01:09
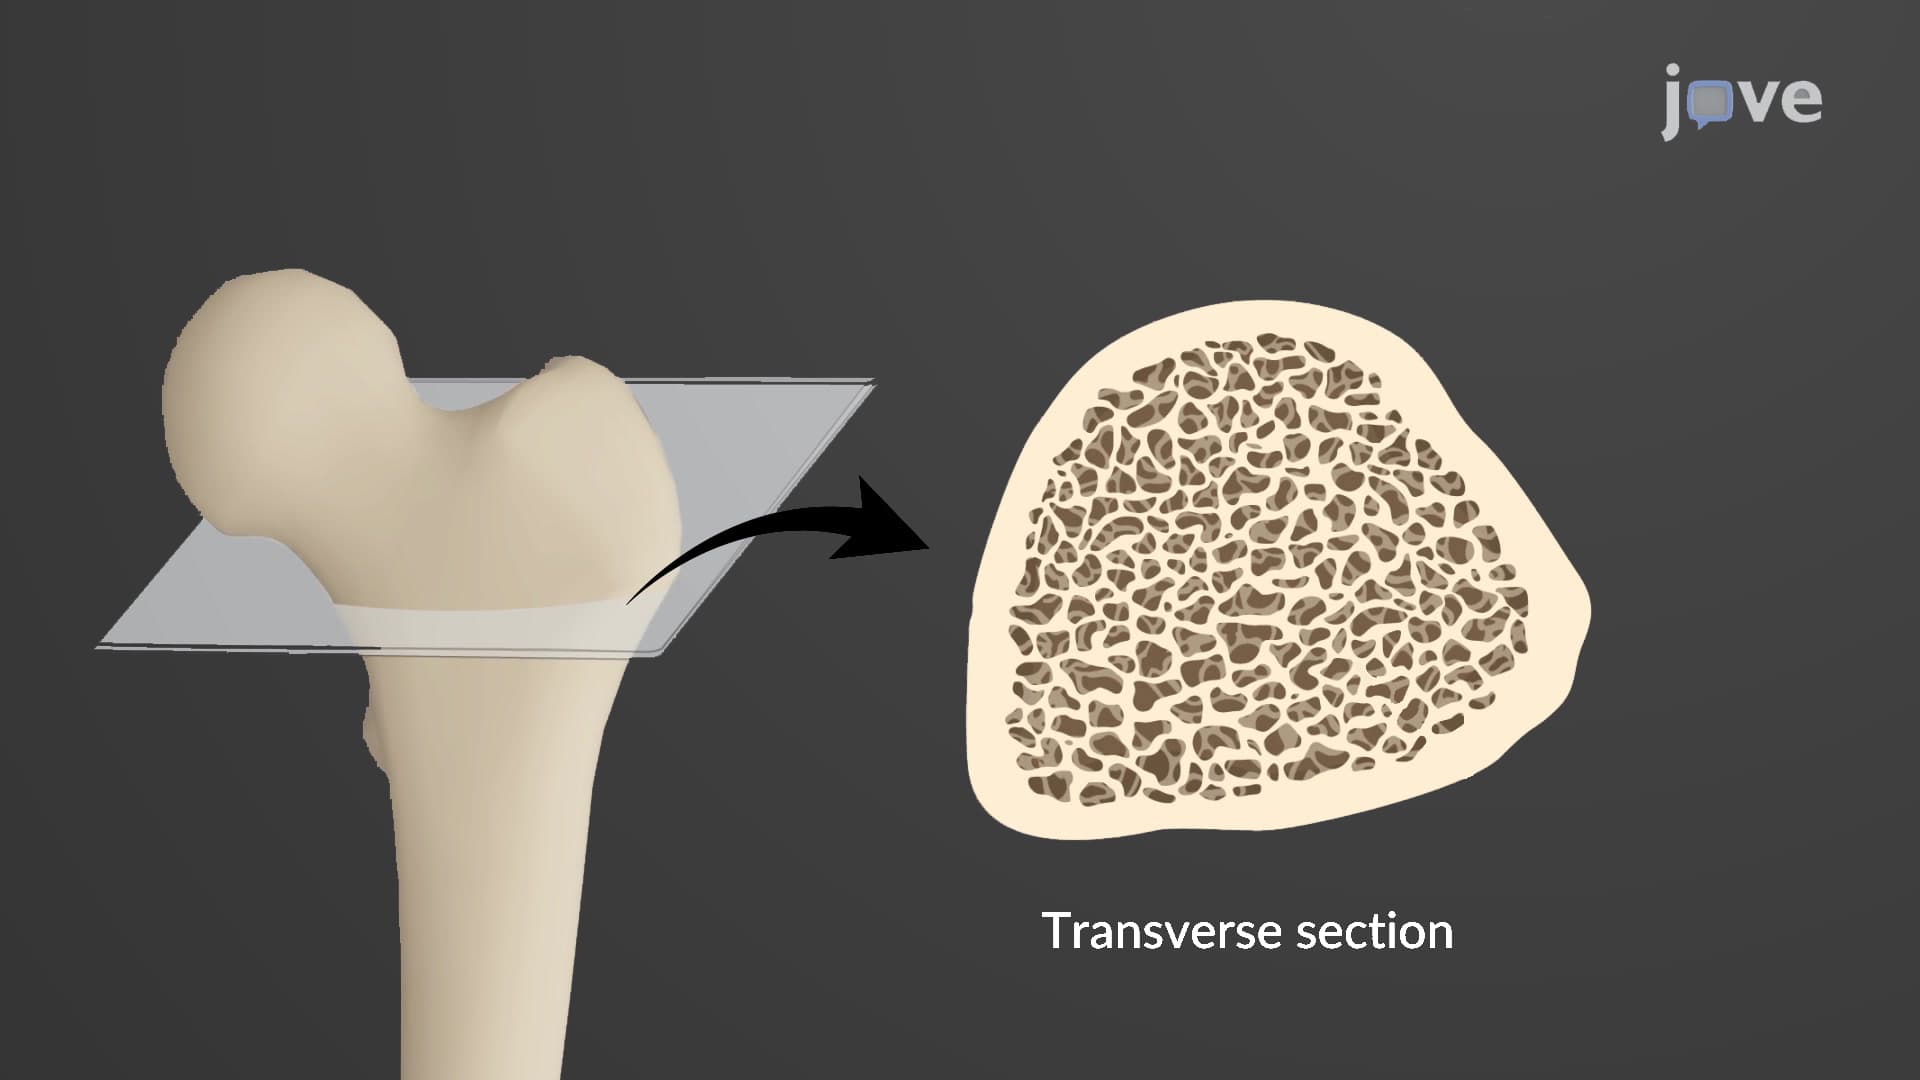
Spongy Bone
Spongy bone is more porous, and less dense compared to compact bone. It is composed of concentric lamellae that are arranged irregularly to form the trabecular network. In some bones, the spaces between trabeculae contain red marrow, where...
 01:27
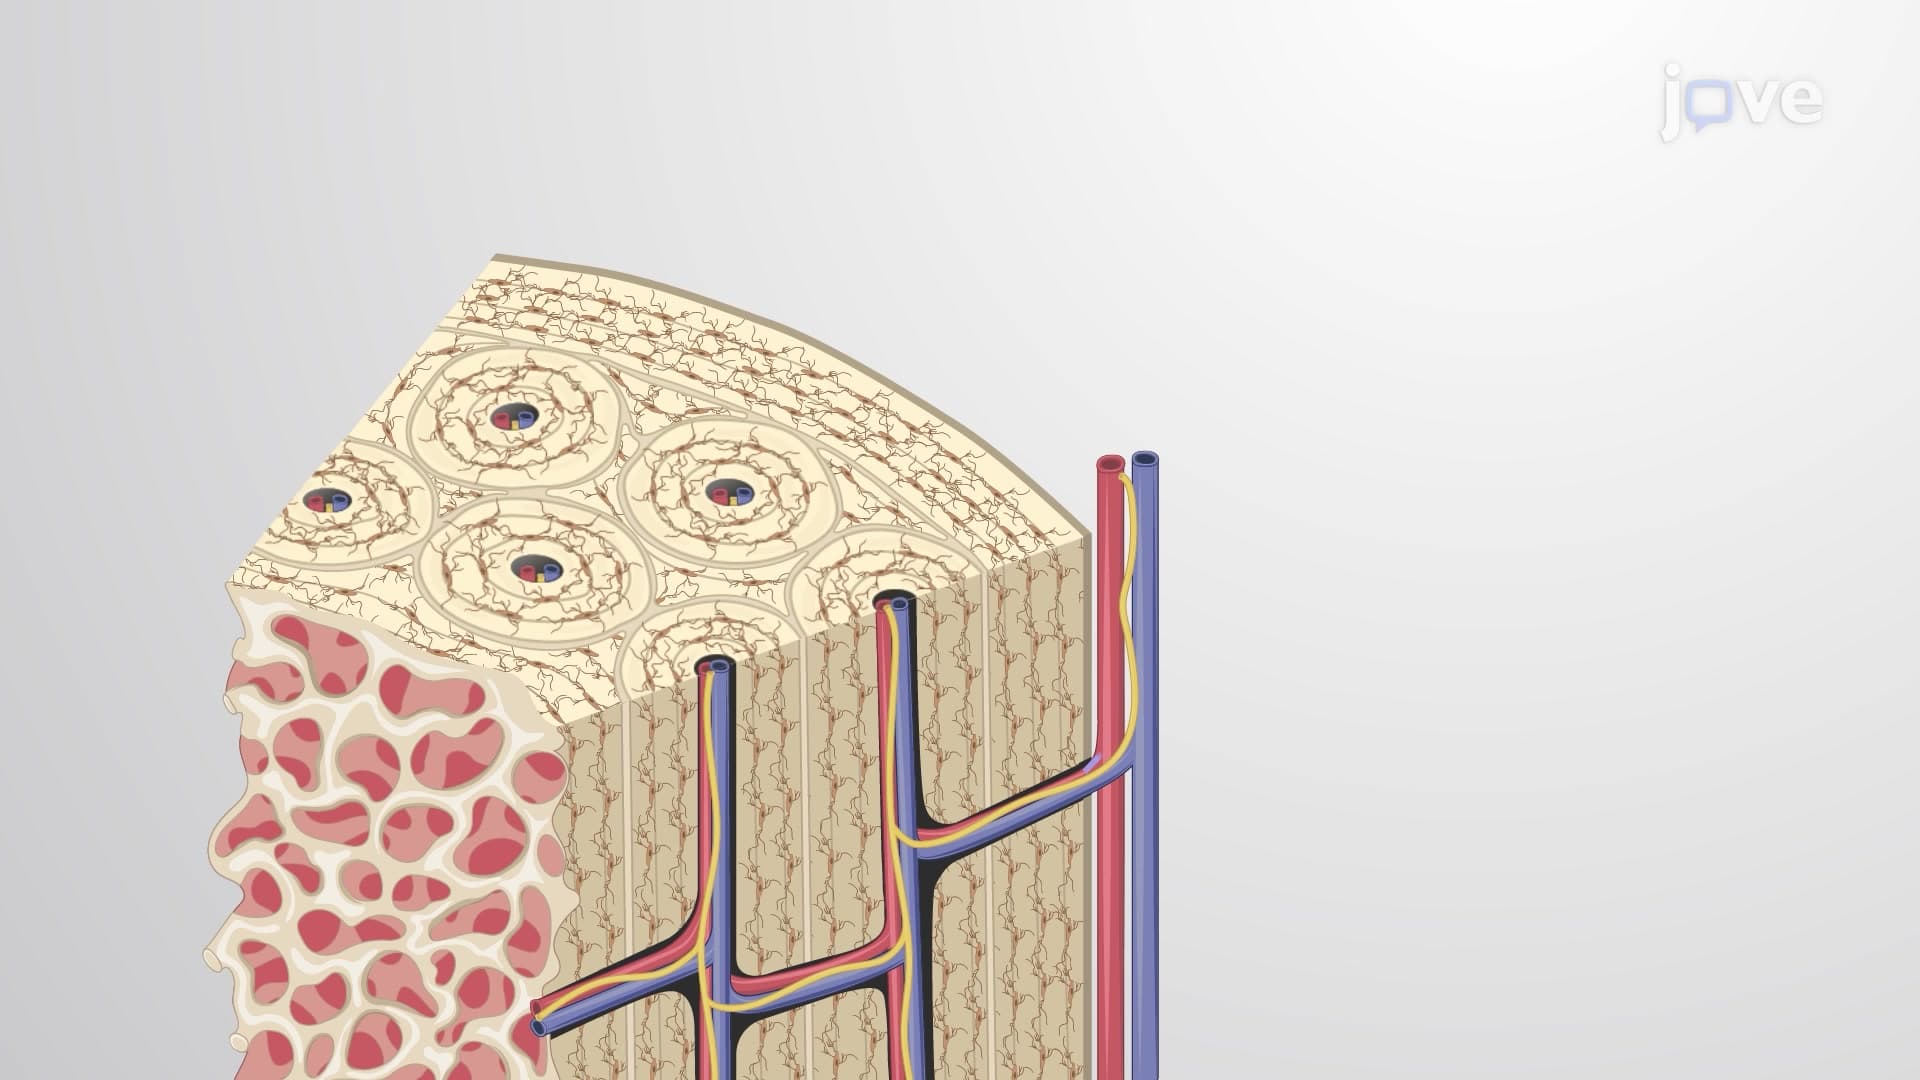
Compact Bone
Compact bone, also called cortical bone, is the denser, stronger of the two types of bone tissue. It is found under the periosteum and in the diaphyses of long bones, where it provides support and protection. The microscopic structural unit of compact bone is called an osteon, or haversian system. Each osteon is composed of concentric rings of calcified...
 01:17
Hormones and Bone Tissue
Hormones That Influence Osteoblasts and/or Maintain the Matrix
Several hormones are necessary for controlling bone growth and maintaining the bone matrix. The pituitary gland secretes growth hormone (GH), which, as its name implies, controls bone growth. This happens in several ways: first, it triggers chondrocyte...