Related Experiment Video
Updated: May 30, 2026
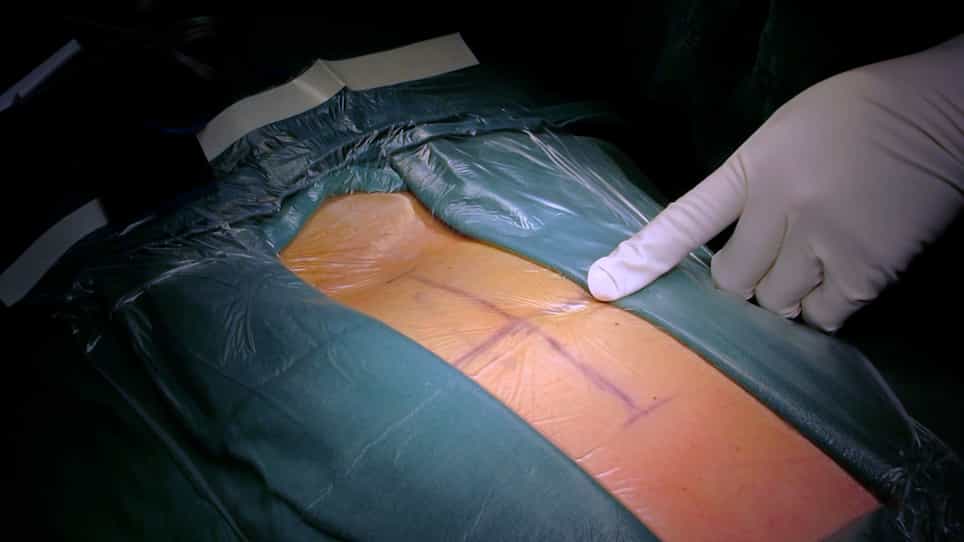

Modified Posterior Vertebral Column Resection for Patients with Thoracolumbar Kyphotic Deformity
Published on: September 16, 2022
Modified posterior closing wedge osteotomy for the treatment of posttraumatic thoracolumbar kyphosis
Xuesong Zhang1, Xuelian Zhang, Yonggang Zhang
1Department of Orthopaedics, Chinese PLA General Hospital, Beijing, People's Republic of China.

Background:
Posttraumatic thoracolumbar deformities can occur in patients after conservative or inadequate surgical treatment. Anterior, posterior, or combined anterior and posterior procedures of Smith-Peterson osteotomy technique have been developed to correct thoracolumbar kyphosis to various degrees. Recently, many reports have addressed the specific problem of local posttraumatic thoracolumbar deformity; however, there is significant controversy over the ideal management. The objectives are to illustrate the technique of modified closing wedge osteotomy for the treatment of posttraumatic kyphosis and to report the radiographic results and clinical outcome of patients treated with the technique.
Methods:
Thirty-six patients with symptomatic posttraumatic thoracolumbar kyphosis treated with a posterior modified closing wedge osteotomy. All patients completed follow-up of at least 2 years.
Results:
The mean surgical time was 224 minutes with a mean intraoperative blood loss of 611.5 mL. The average preoperative regional angle was 40.5 degrees, 4.8 degrees postoperatively, and 5.8 degrees at final follow-up. The average Cobb angle changed from 43.4 degrees preoperatively to 2.4 degrees after surgery. The mean visual analog scale back pain score decreased from 55.2 preoperatively to 19.6 at final follow up, and the mean Oswestry disability index score changed from 58.7 preoperatively to 21.8 at the last follow-up. All patients achieved bony anterior fusion based on radiographic evidence of the presence of trabecular bone bridging at the osteotomy site.
Conclusions:
The modified wedge closing osteotomy achieves satisfactory kyphosis correction and good fusion with less blood loss and complications than other approaches, implying an alternative method in patients with posttraumatic kyphosis.
