Related Experiment Video
Updated: May 30, 2026


Evaluation of a Point-of-Care Testing Analyzer for Measuring Peripheral Blood Leukocytes
Published on: March 22, 2022
Diagnostic accuracy of white cell count and C-reactive protein for assessing the severity of paediatric appendicitis
Khurram Siddique1, Paramita Baruah, Santosh Bhandari
1Department of General Surgery , William Harvey Hospital, Ashford, Kent , UK.

Insights
White cell count (WCC) and C-reactive protein (CRP) aid in diagnosing paediatric appendicitis severity. Combined, WCC and CRP offer high accuracy for simple and perforated appendicitis in children.
Area of Science:
- Pediatric Surgery
- Diagnostic Imaging
- Clinical Pathology
Background:
- Acute appendicitis is a common surgical emergency in children.
- Accurate diagnosis is crucial to prevent complications.
- Biomarkers like white cell count (WCC) and C-reactive protein (CRP) are used to aid diagnosis.
Purpose of the Study:
- To evaluate the diagnostic accuracy of WCC and CRP for assessing the severity of acute appendicitis in children.
- To compare the diagnostic performance of WCC and CRP individually and in combination.
Main Methods:
- A cross-sectional study was conducted on children undergoing open appendectomy.
- Data on demographics, WCC, CRP, histology, and complications were analyzed.
- Diagnostic accuracy of WCC and CRP for simple appendicitis and perforated appendix was assessed.
Main Results:
- Out of 204 patients, 32 had perforated appendix; this group had significantly worse clinical parameters (P<0.05).
- White cell count (WCC) demonstrated higher diagnostic accuracy and sensitivity than C-reactive protein (CRP) for simple appendicitis.
- Combined WCC and CRP sensitivity reached 95% for simple appendicitis and 100% for perforated appendicitis.
Conclusions:
- WCC is more accurate than CRP in diagnosing simple acute appendicitis.
- The combination of WCC and CRP significantly enhances diagnostic accuracy for both simple and perforated appendicitis in pediatric patients.
Objectives:
Simple investigations like white cell count (WCC) and C-reactive protein (CRP) may help to improve the accuracy of diagnosis in paediatric appendicitis. We evaluated the diagnostic accuracy of WCC and CRP for the severity of acute appendicitis in children.
Design:
Cross-sectional study.
Setting:
This study was conducted on all children who underwent open appendectomy from January 2007 to December 2008 at a District General Hospital. Data regarding demographics, WCC, CRP, histology and postoperative complications were analysed.
Participants:
All children who underwent open appendectomy during the study period.
Main Outcome Measures:
Diagnostic accuracy of WCC and CRP for simple acute appendicitis and a perforated appendix.
Results:
Out of 204 patients, 112 (54.9%) were girls. At surgery, appendix was grossly inflamed in 175 of which 32 had perforation. Histology revealed simple acute appendicitis in 135 (66.2%) and gangrenous appendicitis in 32 (15.7%). The rest were normal. The duration of symptoms, temperature, length of stay, WCC and CRP were significantly worse in the perforated group (P value <0.05). Postoperative complications included wound infection (n = 18), pelvic collection (n = 5) and intestinal obstruction (n = 6); and were more common among patients with a perforated appendix (P value <0.05). WCC had a higher diagnostic accuracy and higher sensitivity than CRP in diagnosing simple acute appendicitis. The combined sensitivity of WCC and CRP increased to 95% and 100% for the diagnosis of simple acute appendicitis and a perforated appendix, respectively.
Conclusion:
Accuracy of WCC is higher than CRP for diagnosing simple acute appendicitis. The combined sensitivity of WCC and CRP increases for simple acute appendicitis as well as a perforated appendix.
Related Concept Videos
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:22
Appendicitis-I: Introduction
Etiology: Appendicitis can arise from various causes, primarily rooted in the obstruction of the appendix lumen. Factors contributing to this obstruction include fecal accumulation, lymphoid hyperplasia and, in...
 01:30
Pneumonia III: Complications and Assessment
 01:19
Pericarditis II: Clinical Features and Diagnostic Tests
 01:19
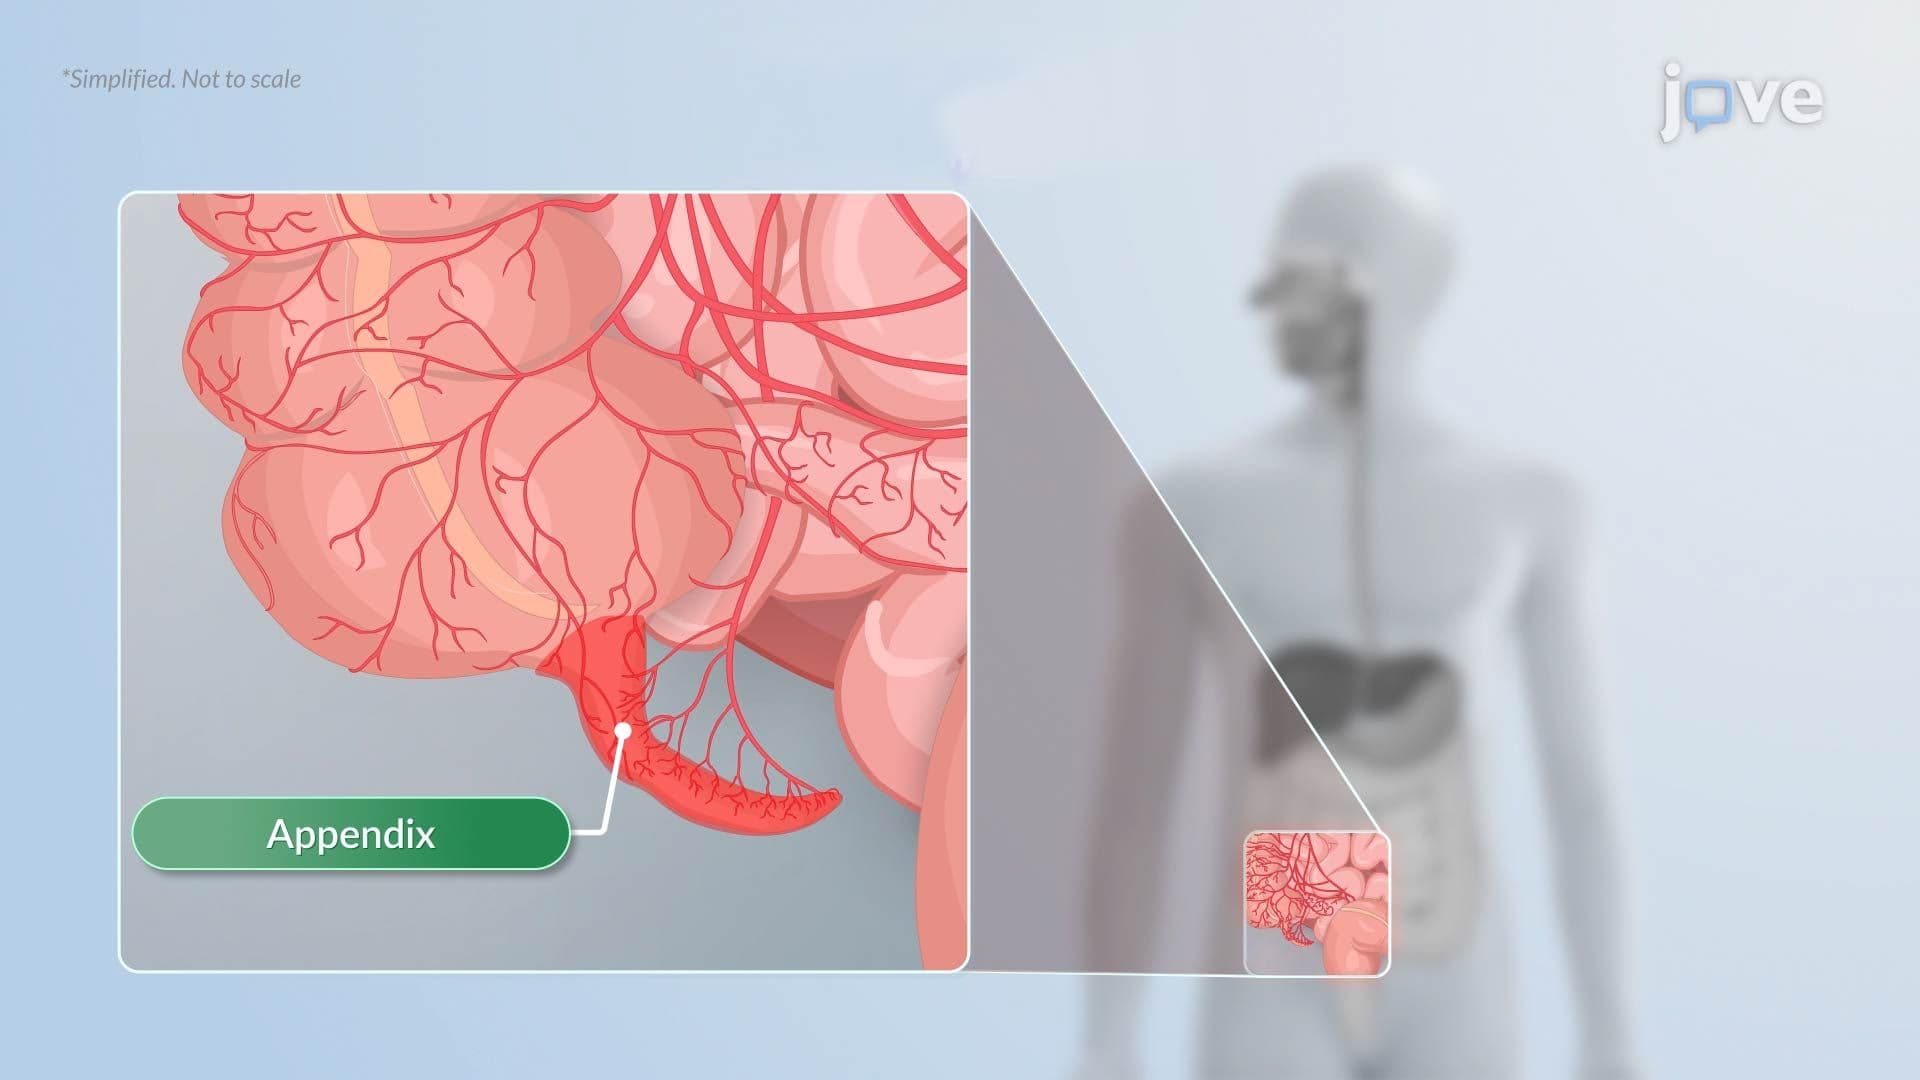
Appendicitis