Related Experiment Video
Updated: May 29, 2026
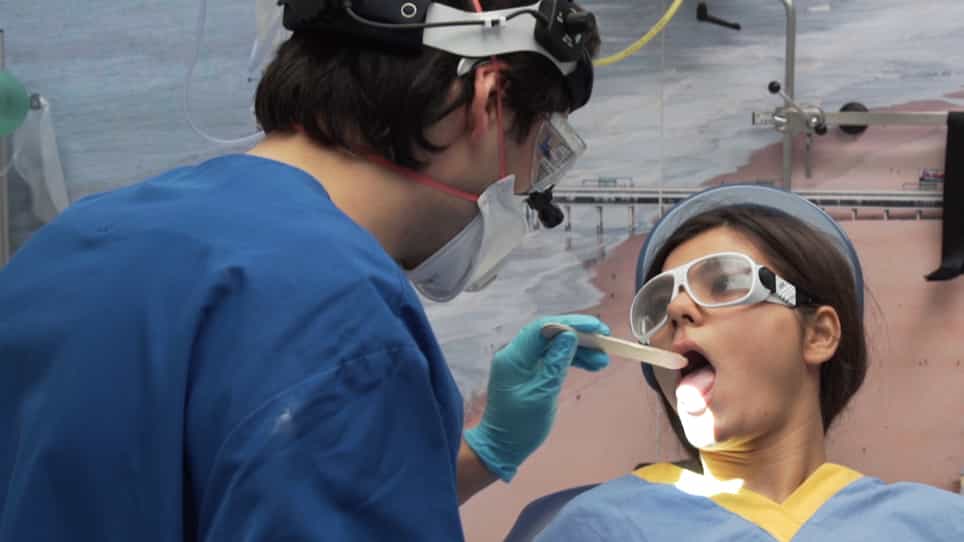

CO2-Lasertonsillotomy Under Local Anesthesia in Adults
Published on: November 6, 2019
A randomised controlled trial of two analgesic techniques for paediatric tonsillectomy*
E Rawlinson1, A Walker, R Skone
1Great Ormond Street Hospital for Children NHS Trust, London, UK.

Abstract:
Investigators from Bristol described a fentanyl- and diclofenac-based analgesic technique for tonsillectomy with low postoperative nausea and vomiting rates and low pain scores. This study compared the effectiveness of a modified Bristol technique with a codeine-based regimen with respect to PONV and analgesia. Sixty-five children, ASA 1-2, were randomly assigned to either the Bristol group (fentanyl 1-2 μg.kg(-1) and diclofenac 1-2 mg.kg(-1)) or codeine group (codeine 1.5 mg.kg(-1)). All children received paracetamol 15 mg.kg(-1) and dexamethasone 0.1 mg.kg(-1) . Postoperative nausea and vomiting and pain scores were recorded hourly, and fitness for discharge was assessed at 4 h. The overall incidence of postoperative nausea and vomiting was 21% with no difference between groups (Bristol group 8/30, codeine group 5/32, p = 0.29). Children in the Bristol group required analgesia earlier than those in the codeine group (p < 0.005), but maximum pain scores were not different (Bristol group median (IQR [range) 4.5 (3-5 [0-5]), codeine group 4.0 (2-5 [1-5]), p = 0.15). Twenty-three per cent of children were assessed as not fit for discharge at 4 h. The codeine-based regimen may have a small advantage over the Bristol regimen, but neither technique seems ideally suited for a day-case service without a longer period of observation. You can respond to this article at http://www.anaesthesiacorrespondence.com.
Related Concept Videos
 01:26
Tonsillitis II: Management
 01:23
Chronic Pharyngitis
Etiology
It often arises from persistent viral or bacterial infections affecting sinuses and tonsils.
Additional contributing factors include inadequate dental hygiene, mouth breathing, recurring tonsillitis, allergic rhinitis, laryngopharyngeal reflux, and exposure to smoke, chemicals, and other environmental pollutants. Allergic reactions to pollen, mold, and pet dander, chronic cough, excessive voice usage,...