Related Experiment Video
Updated: Oct 3, 2026
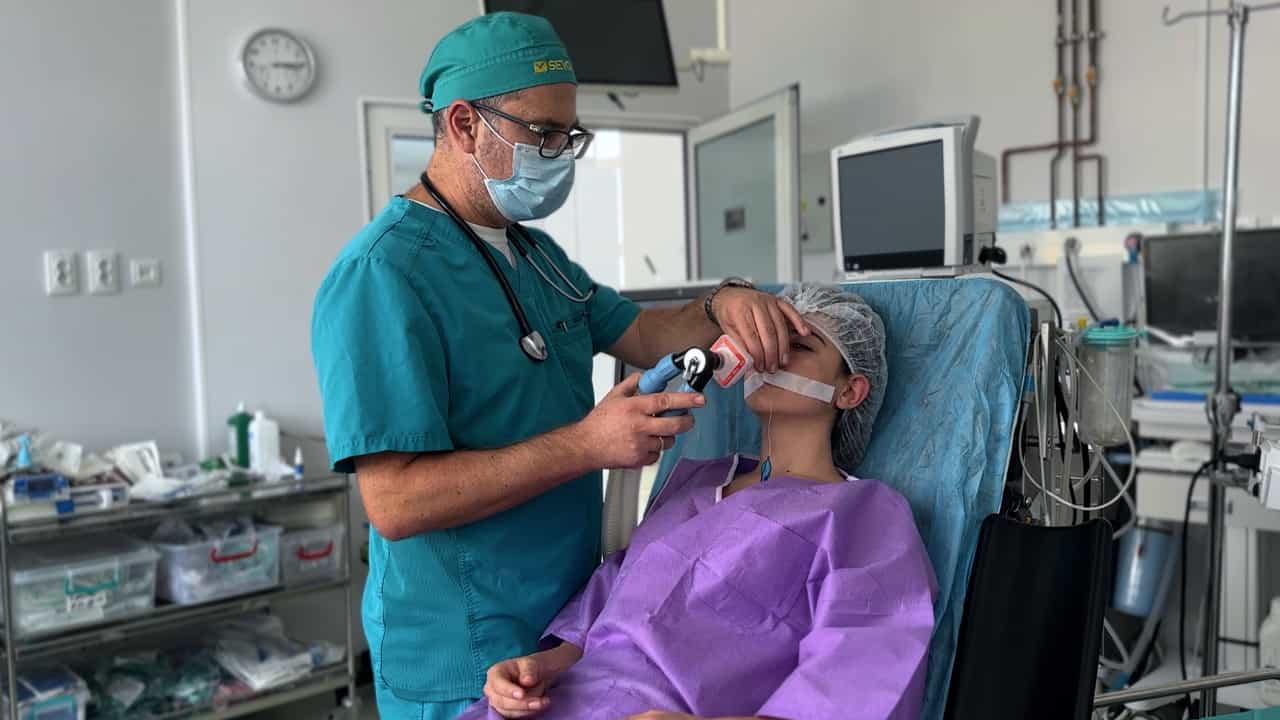

The Flexible Rhino-Laryngoscope for Awake Nasotracheal Intubation
Published on: August 2, 2024
Association between glottic view and tracheal intubation during videolaryngoscopy: a prospective observational study
Miguel Ángel Fernández-Vaquero1,2, Pedro Charco-Mora3, Manuel Ángel Gómez-Ríos4
1Department of Anaesthesiology and Critical Care, Clínica Universidad de Navarra, Madrid, Spain.

Introduction:
A good view of the glottis with videolaryngoscopy does not translate consistently into straightforward tracheal tube delivery, suggesting a dissociation between visualisation and procedural execution. When videolaryngoscopy documentation is based on laryngeal view alone, it does not reliably reflect the performance of tracheal intubation. We evaluated this relationship and the reproducibility of a structured classification framework for videolaryngoscopic tracheal intubation.
Methods:
We conducted a prospective multicentre observational study across 44 hospitals. Videolaryngoscopic tracheal intubations were assessed independently by an airway operator and an observer using a three-domain classification: blade geometry; glottic view using the percentage of glottic opening (POGO) score; and tracheal tube delivery. Inter-rater reliability was assessed. The relationship between glottic view and tracheal tube delivery was analysed across predefined POGO categories.
Results:
A total of 5302 tracheal intubations with paired assessments were analysed. The overall inter-rater agreement for the three-domain classification was high (Krippendorff's α = 0.86, 95%CI 0.85-0.87). Among tracheal intubations with poor view (POGO < 25%), 37/151 (24.5%) were classified as easy. Among tracheal intubations with POGO ≥ 25%, 527/5151 (10.2%) were classified as difficult or failed. Even with excellent glottic view (POGO > 75%), the initial strategy was classified as difficult or failed in 252/4025 (6.3%) of cases.
Discussion:
The ease of tracheal intubation with videolaryngoscopy cannot be inferred from glottic view alone. A structured approach that incorporates what was used, what was seen and what was done may improve communication in clinical practice.

Related Concept Videos
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:28
Tracheostomy: Procedure and Tubes
Tracheostomy tubes can be made of semiflexible plastic (polyurethane or silicone), rigid plastic, or metal, and they come in...
 01:15
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:30
Endoscopic Studies I: Bronchoscopy and Thoracoscopy
Bronchoscopy
Description
Bronchoscopy is a procedure that involves direct visualization of the larynx, trachea, and bronchi for diagnostic and therapeutic purposes. A flexible fiber optic or rigid bronchoscope is used to carry out the procedure. The fiber-optic bronchoscope is more frequently used due to...
 01:25
Tracheostomy Care II: Procedure
Step 1: Perform hand hygiene, and put on personal protective equipment: gown, gloves, mask and...
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals.