Related Experiment Video
Updated: Aug 19, 2026
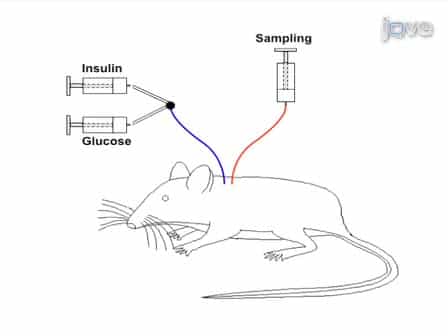
Hyperinsulinemic-Euglycemic Clamp in the Conscious Rat
Published on: February 7, 2011
Biphasic insulin secretion after intravenous but not after intraportal CCK-8 infusion in rats
B Balkan1, A B Steffens, J H Strubbe
1Department of Animal Physiology, University of Groningen, Netherlands.

The effects of physiological doses of sulfated cholecystokinin-8 (CCK-8) on insulin secretion were investigated in unrestrained unanesthetized rats. The routes of administration were intravenous or intraportal infusion. Intravenous infusion (0.33-5.0 micrograms CCK-8.kg-1.20 min-1) resulted in a biphasic response pattern consisting of a fast 1st-min rise in plasma insulin concentration and a slower second phase that lasted throughout the infusion. The first phase showed the same amplitude with all amounts of CCK-8 administered in this study, whereas the second phase exhibited dose dependency. Blood glucose levels were lowered during all infusions of CCK-8, although the second phase of insulin release was absent with the lowest dose. These results suggest a strong stimulatory effect of CCK-8 on the pancreatic beta-cells, probably by changing the set point for glucose. The described effects of intravenous administration of CCK-8 cannot be produced when the infusion is given into the portal vein. Only very high concentrations of CCK-8 (15 micrograms.kg-1.20 min-1) produced a small increase in plasma insulin levels, indicating a strong CCK-8-eliminating mechanism in the liver. These results indicate that 1) CCK-8 evokes biphasic insulin release and a concomitant drop in glucose levels, and 2) CCK-8 acting on the beta-cell in vivo is not of intestinal origin but is probably released by the pancreatic vagal branch.
The effects of physiological doses of sulfated cholecystokinin-8 (CCK-8) on insulin secretion were investigated in unrestrained unanesthetized rats. The routes of administration were intravenous or intraportal infusion. Intravenous infusion (0.33-5.0 micrograms CCK-8.kg-1.20 min-1) resulted in a biphasic response pattern consisting of a fast 1st-min rise in plasma insulin concentration and a slower second phase that lasted throughout the infusion. The first phase showed the same amplitude with all amounts of CCK-8 administered in this study, whereas the second phase exhibited dose dependency. Blood glucose levels were lowered during all infusions of CCK-8, although the second phase of insulin release was absent with the lowest dose. These results suggest a strong stimulatory effect of CCK-8 on the pancreatic beta-cells, probably by changing the set point for glucose. The described effects of intravenous administration of CCK-8 cannot be produced when the infusion is given into the portal vein. Only very high concentrations of CCK-8 (15 micrograms.kg-1.20 min-1) produced a small increase in plasma insulin levels, indicating a strong CCK-8-eliminating mechanism in the liver. These results indicate that 1) CCK-8 evokes biphasic insulin release and a concomitant drop in glucose levels, and 2) CCK-8 acting on the beta-cell in vivo is not of intestinal origin but is probably released by the pancreatic vagal branch.


Related Concept Videos
 01:05
Insulin Secretory Vesicles
 01:27
Glucose Homeostasis: Pancreatic Islets and Insulin Secretion
Insulin and C-peptide are co-secreted in...
 01:27
Insulin Formulations: Types and Delivery
Short-acting insulins are divided into rapid-acting...
 01:24
Glucagon-like Receptor Agonists
GLP-1, when administered in high doses intravenously, triggers insulin secretion, inhibits glucagon release, slows gastric emptying, reduces food intake, and restores normal insulin secretion. However, its rapid inactivation by the...