Related Experiment Video
Updated: May 29, 2026
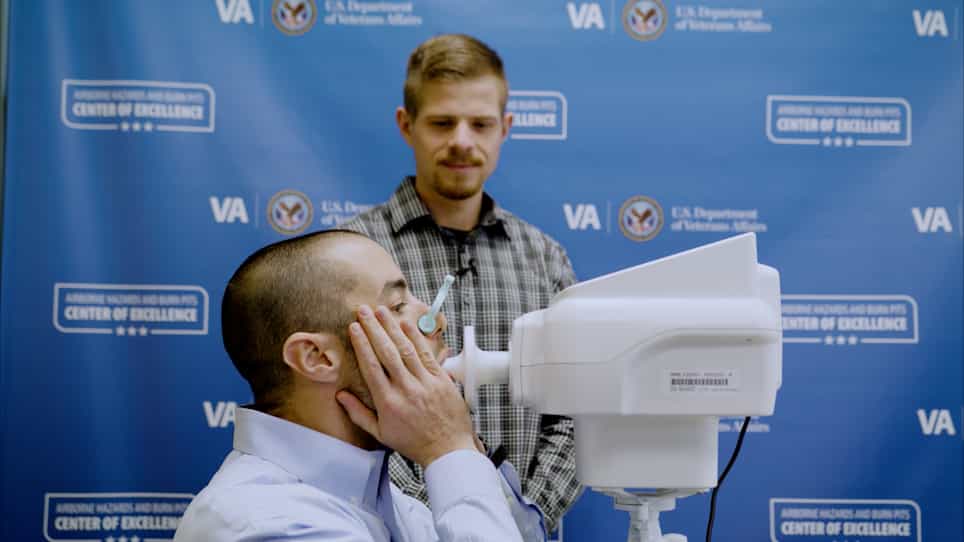

Employing the Forced Oscillation Technique for the Assessment of Respiratory Mechanics in Adults
Published on: February 9, 2022
Airway responsiveness measured by forced oscillation technique in severely obese patients, before and after bariatric
Françoise Zerah-Lancner1, Laurent Boyer, Saida Rezaiguia-Delclaux
1Service de Physiologie-Explorations Fonctionnelles, Hôpital Henri Mondor, AP-HP, Creteil, France. francoise.zerah@hmn.aphp.fr

Background:
The influence of obesity on airway responsiveness remains controversial.
Objective:
This study was designed to investigate airway responsiveness, airway inflammation, and the influence of sleep apnea syndrome (SAS), in severely obese subjects, before and after bariatric surgery.
Methods:
A total of 120 non-asthmatic obese patients were referred consecutively for pre-bariatric surgery evaluation. Lung function, airway responsiveness to methacholine, exhaled nitric oxide measurement, and sleep studies were performed. Airway hyperresponsiveness (AHR) was defined as a 50% or greater increase in respiratory resistance measured using the forced oscillation technique in response to a methacholine dose ≤ 2000 μg. Forced expiratory volume in 1 second (FEV₁) was measured after the last methacholine dose. Airway responsiveness was reevaluated after weight loss in patients with a pre-surgery AHR.
Results:
AHR was found in 16 patients. The percent FEV₁ decrease or percent respiratory resistance increase in response to methacholine was related to baseline expiratory airflow (forced expiratory flow at 50%) (r = 0.26, p < .006 and r = 0.315, p = .0005, respectively) but not to body mass index (BMI) or exhaled nitric oxide. Both airway responsiveness parameters were significantly related to forced expiratory flow at 25-75%/forced vital capacity, a measure of airway size relative to lung size (r = 0.27, p < .005 and r = 0.25, p < .007, respectively). Sleep apnea was not significantly associated with AHR or airway inflammation. About 11 patients with AHR were reevaluated 18 months to 2 years after surgery, with no change in AHR associated with weight loss.
Conclusion:
Airway responsiveness is not related to BMI or to SAS. AHR in severely obese patients might be related to distal airway obstruction or low relative airway size.
Related Concept Videos
 01:15
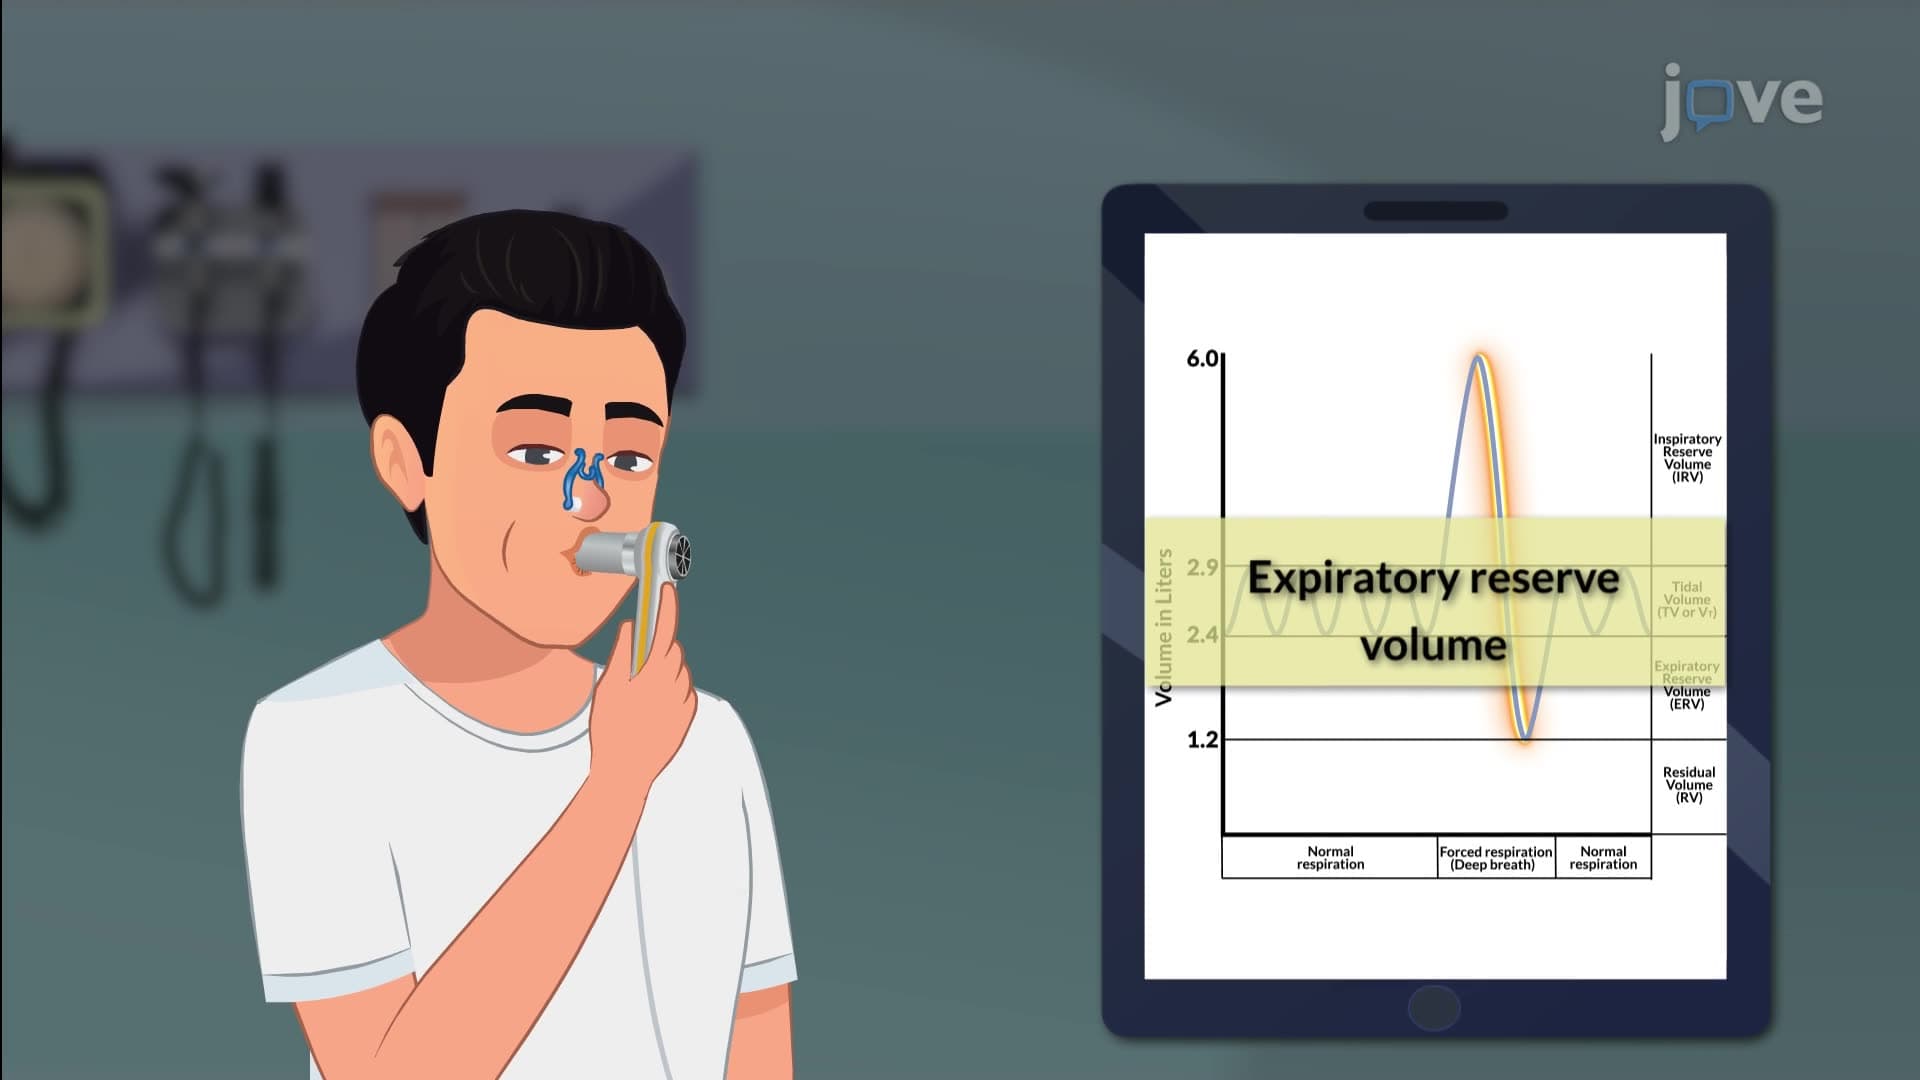
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:30
Assessment of Airway, Skin Color, and Use of Accessory Muscles
Introduction
The initial evaluation of a patient's respiratory system...
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:23
Assessment of Respiration
Subjective Assessment: Nurses interview the patient to gather information directly during the subjective assessment. It includes questions about the individual's medical history, medications, and symptoms, focusing on past respiratory conditions like asthma or COPD,...
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques