Related Experiment Video
Updated: May 29, 2026
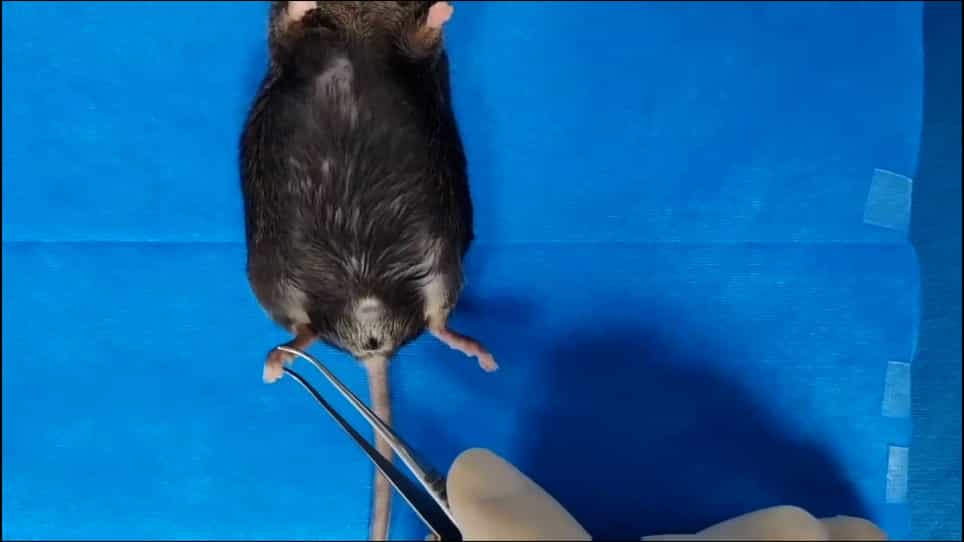

Duodenal-Jejunal Bypass Surgery in Diet-Induced Obese Diabetic Mice
Published on: October 18, 2024
Diabetes remission after bariatric surgery: is it just the incretins?
1New York Obesity Nutrition Research Center, Division of Endocrinology and Diabetes, Department of Medicine, St Luke's Roosevelt Hospital Center, Columbia University College of Physicians and Surgeons, New York, NY 10025, USA. BBL14@columbia.edu

Abstract:
Gastric bypass surgery (GBP) results in important and sustained weight loss and remarkable improvement of Type 2 diabetes. The favorable change in the incretin gut hormones is thought to be responsible, in part, for diabetes remission after GBP, independent of weight loss. However, the relative role of the change in incretins and of weight loss is difficult to differentiate. After GBP, the plasma concentrations of the incretin hormones glucagon-like peptide 1 (GLP-1) and glucose-dependent insulinotropic polypeptide increase postprandially by three- to fivefold. The postprandial incretin effect on insulin secretion, blunted in diabetes, improves rapidly after the surgery. In addition to the change in incretins, the pattern of insulin secretion in response to oral glucose changes after GBP, with recovery of the early phase and significant decrease in postprandial glucose levels. These changes were not seen after an equivalent weight loss by diet. The improved insulin release and glucose tolerance after GBP were shown by others to be blocked by the administration of a GLP-1 antagonist, demonstrating that the favorable metabolic changes after GBP are, in part, GLP-1 dependent. The improved incretin levels and effect persist years after GBP, but their long-term effect on glucose metabolism, and on hypoglycemia post GBP are yet unknown. Understanding the mechanisms by which incretin release is exaggerated postprandially after GBP may help develop new less invasive treatment options for obesity and diabetes. Changes in rate of eating, gastric emptying, intestinal transit time, nutrient absorption and sensing, as well as bile acid metabolism, may all be implicated.

Related Concept Videos
 01:24
Glucagon-like Receptor Agonists
GLP-1, when administered in high doses intravenously, triggers insulin secretion, inhibits glucagon release, slows gastric emptying, reduces food intake, and restores normal insulin secretion. However, its rapid inactivation by the...
 01:23
Dipeptidyl Peptidase 4 Inhibitors
 01:36
Carbohydrate Metabolism
Starch accounts for approximately 60% of the carbohydrates consumed by humans. Since amylase enzymes cannot function in the stomach's acidic environment, starch can only be digested in the mouth and small intestine. Simple sugars are found naturally in milk and fruits in the...
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
 01:26
Oral Hypoglycemic Agents: Biguanides and Glitazones
 01:24
Type II Diabetes II: Pathophysiology