Related Experiment Video
Updated: May 29, 2026
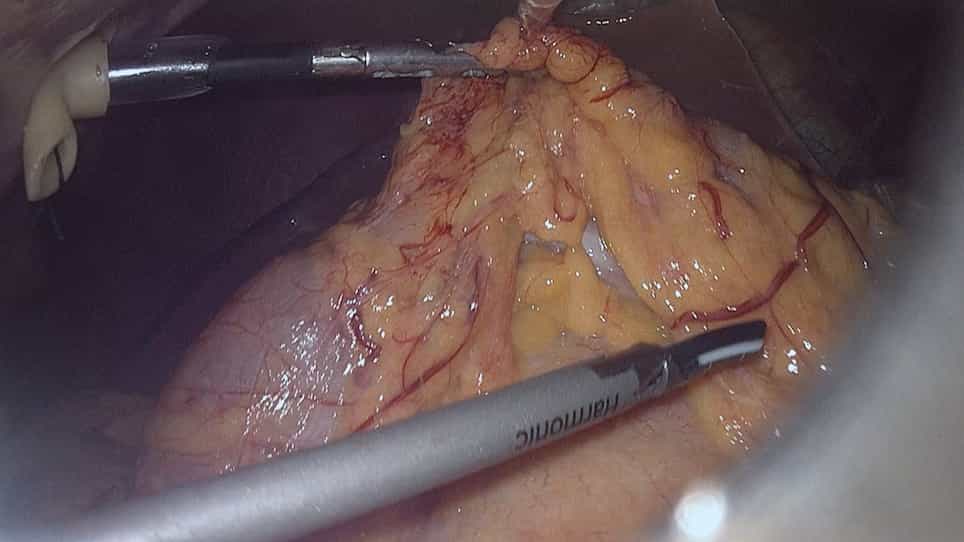

Laparoscopic Pancreatoduodenectomy for Pancreatic Cancer Using In-Situ No-Touch Isolation Technique
Published on: February 2, 2022
Staging laparoscopy for proximal pancreatic cancer in a magnetic resonance imaging-driven practice: what's it worth?
Elliot Tapper1, Bobby Kalb, Diego R Martin
1Department of Medicine, Beth Israel Deaconess Medical Centre, Boston, MA, USA.

Background:
Preoperative imaging is often inadequate in excluding unresectable pancreatic cancer. Accordingly, many groups employ staging laparoscopy (SL), although none have evaluated SL after preoperative magnetic resonance imaging (MRI). We performed a retrospective, indirect cost-effectiveness analysis of SL after MRI for pancreatic head lesions.
Methods:
All MRI scans administered for proximal pancreatic cancer between 2004 and 2008 were reviewed and the clinical course of each patient determined. We queried our billing database to render average total costs for all inpatients with proximal pancreatic cancer who underwent pancreaticoduodenectomy, palliative bypass or an endoscopic stenting procedure. We then performed an indirect evaluation of the cost of routine SL.
Results:
The average costs of hospitalization for patients undergoing pancreaticoduodenectomy, open palliative bypass and endoscopic palliation were: US$26, 122.43, US$21, 957.18 and US$11, 304.00, respectively. The calculated cost of SL without laparotomy was US$2966.25 or US$1538.61 prior to laparotomy. The calculated cost of treating unresectable disease by outpatient laparoscopy followed by endoscopy was US$5943.17. Routine SL would increase our costs by US$76, 967.46 (3.6%).
Conclusions:
Staging laparoscopy becomes cost-effective by diverting unresectable patients from operative to endoscopic palliation. Given the paucity of missed metastases on MRI, the yield of SL is marginal and its cost-effectiveness is poor. Future studies should address the utility of SL by both examining this issue prospectively and investigating the cost-effectiveness of endoscopic vs. surgical palliation in a manner that takes account of survival and quality of life data.