Related Experiment Video
Updated: May 29, 2026
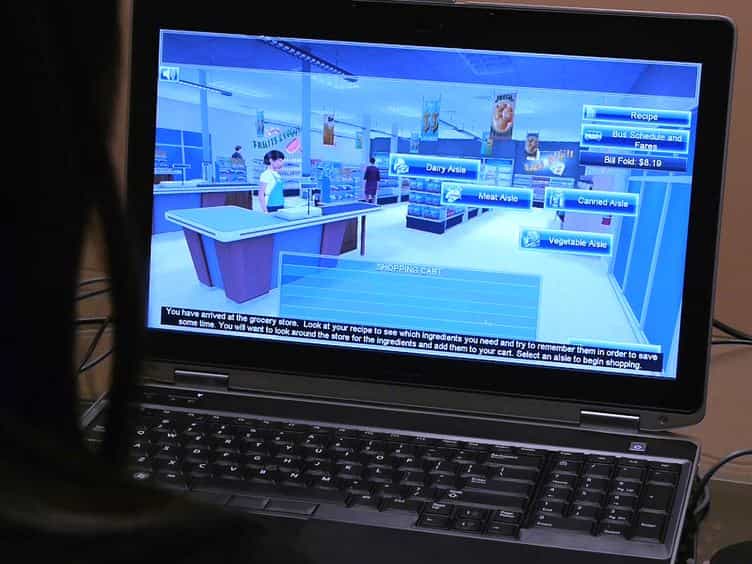

Development of a Virtual Reality Assessment of Everyday Living Skills
Published on: April 23, 2014
Psychometric validation of the cardiac rehabilitation barriers scale
Shamila Shanmugasegaram1, Lucia Gagliese, Paul Oh
1York University, Toronto, Ontario, Canada.

Insights
The Cardiac Rehabilitation Barriers Scale (CRBS) has four factors and good psychometric properties, identifying key barriers to cardiac rehabilitation utilization. Further research should explore addressing these barriers.
Area of Science:
- Cardiology
- Health Psychology
- Rehabilitation Medicine
Background:
- Cardiac rehabilitation is crucial for patient recovery.
- Understanding barriers to participation is essential for improving uptake.
- The Cardiac Rehabilitation Barriers Scale (CRBS) needed validation.
Purpose of the Study:
- To investigate the factor structure of the CRBS.
- To assess the psychometric properties of the CRBS.
- To validate the CRBS for measuring cardiac rehabilitation barriers.
Main Methods:
- 2636 cardiac inpatients completed surveys, including the CRBS.
- Factor analysis with oblique rotation was used.
- Convergent validity and test-retest reliability were assessed.
Main Results:
- A four-factor solution emerged: perceived need/healthcare, logistical, work/time, and comorbidities/functional status.
- The CRBS demonstrated sound psychometric properties (Cronbach's α ranging from .71 to .89).
- Non-enrollees reported significantly higher barriers than enrollees (P < .001).
Conclusions:
- The CRBS is a valid and reliable measure with four subscales.
- Identified barriers may hinder cardiac rehabilitation utilization.
- Future studies should focus on interventions to overcome these barriers.
Objective:
The purpose of this study was to investigate the factor structure and psychometric properties of the Cardiac Rehabilitation Barriers Scale (CRBS).
Design, Setting, And Participants:
In total, 2636 cardiac inpatients from 11 hospitals completed a survey. One year later, participants completed a follow-up survey, which included the CRBS. A subsample of patients also completed a third survey which included the CRBS, the Cardiac Rehabilitation Enrolment Obstacles scale, and the Beliefs About Cardiac Rehabilitation scale three weeks later. The CRBS asked participants to rate 21 cardiac rehabilitation barriers on a five-point Likert scale regardless of cardiac rehabilitation referral or enrolment.
Results:
Maximum likelihood factor analysis with oblique rotation resulted in a four-factor solution: perceived need/healthcare factors (eigenvalue = 6.13, Cronbach's α = .89), logistical factors (eigenvalue = 5.83, Cronbach's α = .88), work/time conflicts (eigenvalue = 3.78, Cronbach's α = .71), and comorbidities/functional status (eigenvalue = 4.85, Cronbach's α = .83). Mean total perceived barriers were significantly greater among non-enrollees than cardiac rehabilitation enrollees (P < .001). Convergent validity with the Beliefs About Cardiac Rehabilitation and Cardiac Rehabilitation Enrolment Obstacles scales was also demonstrated. Test-retest reliability of the CRBS was acceptable (intraclass correlation coefficient = .64).
Conclusion:
The CRBS consists of four subscales and has sound psychometric properties. The extent to which identified barriers can be addressed to facilitate greater cardiac rehabilitation utilization warrants future study.
