Related Experiment Video
Updated: May 29, 2026
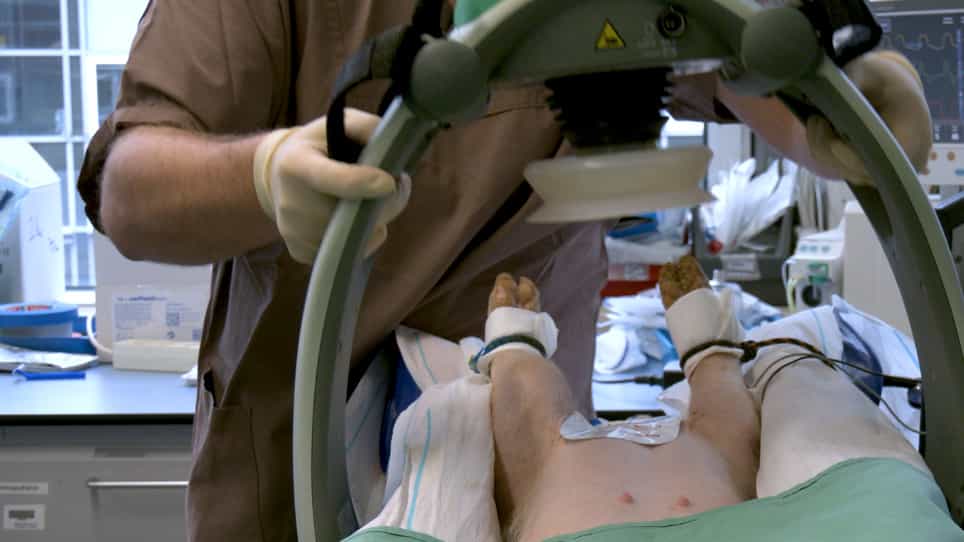
Standardized Model of Ventricular Fibrillation and Advanced Cardiac Life Support in Swine
Published on: January 30, 2020
Factors associated with emergency medical services scope of practice for acute cardiovascular events
Ishmael Williams1, Amy L Valderrama, Patricia Bolton
1From the Division for Heart Disease and Stroke Prevention, Centers for Disease Control and Prevention, Atlanta, GA 30341, USA. iwilliams2@cdc.gov

Objectives:
To examine prehospital emergency medical services (EMS) scope of practice for acute cardiovascular events and characteristics that may affect scope of practice; and to describe variations in EMS scope of practice for these events and the characteristics associated with that variability.
Methods:
In 2008, we conducted a telephone survey of 1,939 eligible EMS providers in nine states to measure EMS agency characteristics, medical director involvement, and 18 interventions authorized for prehospital care of acute cardiovascular events by three levels of emergency medical technician (EMT) personnel.
Results:
A total of 1,292 providers responded to the survey, for a response rate of 67%. EMS scope of practice interventions varied by EMT personnel level, with the proportion of authorized interventions increasing as expected from EMT-Basic to EMT-Paramedic. Seven of eight statistically significant associations indicated that EMS agencies in urban settings were less likely to authorize interventions (odds ratios <0.7) for any level of EMS personnel. Based on the subset of six statistically significant associations, fire department-based EMS agencies were two to three times more likely to authorize interventions for EMT-Intermediate personnel. Volunteer EMS agencies were more than twice as likely as nonvolunteer agencies to authorize interventions for EMT-Basic and EMT-Intermediate personnel but were less likely to authorize any one of the 11 interventions for EMT-Paramedics. Greater medical director involvement was associated with greater likelihood of authorization of seven of the 18 interventions for EMT-Basic and EMT-Paramedic personnel but had no association with EMT-Intermediate personnel.
Conclusions:
We noted statistically significant variations in scope of practice by rural vs. urban setting, medical director involvement, and type of EMS service (fire department-based/non-fire department-based; volunteer/paid). These variations highlight local differences in the composition and capacity of EMS providers and offer important information for the transition towards the implementation of a national scope of practice model.

Related Concept Videos
 01:30
Introduction Cardiac Emergencies
 01:28
Acute Coronary Syndrome IV: Interprofessional Care
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management
 01:26
Acute Coronary Syndrome V: Nursing Management
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:23
Cardiopulmonary Resuscitation III: AED Use