Related Experiment Video
Updated: May 29, 2026
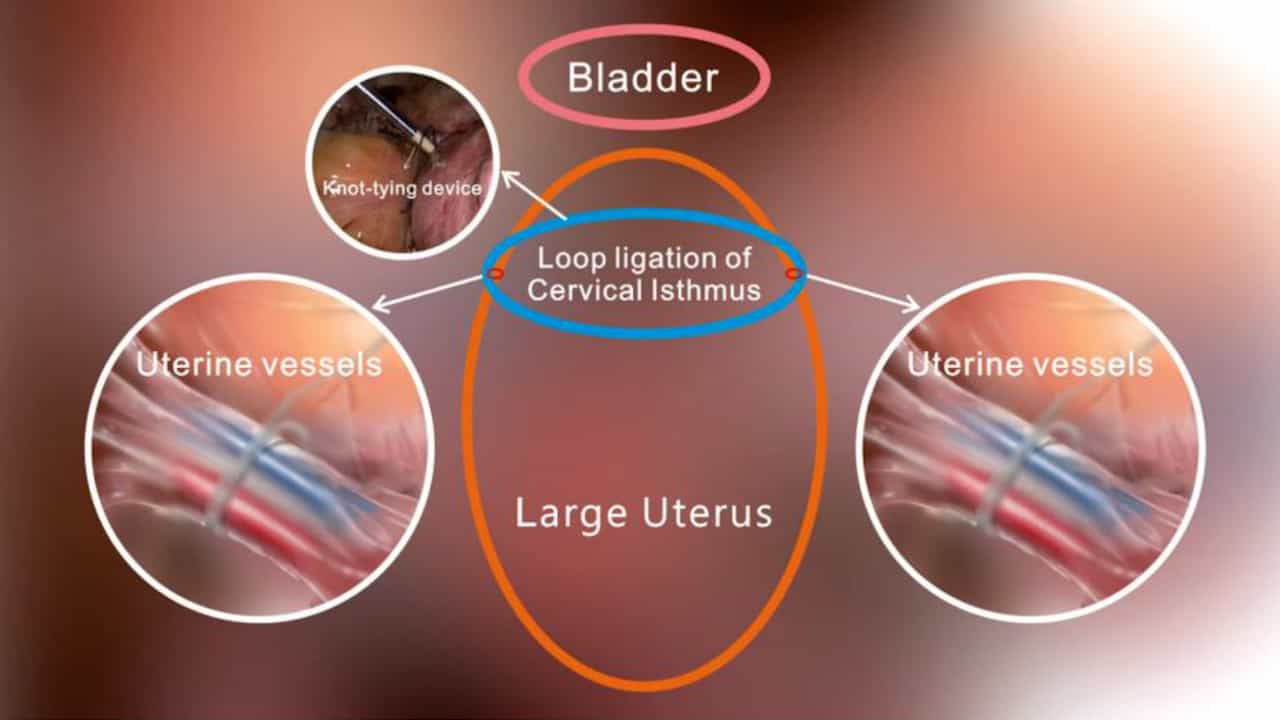

Laparoscopic Extracorporeal Knot-Tying for Uterine Vessel Occlusion during Hysterectomy with Cervical Cerclage in Large Uteri
Published on: September 12, 2025
When do we need to perform laparotomy for benign uterine disease? Factors involved with conversion in vaginal
Hye-Yon Cho1, Hong-Bae Kim, Sung-Won Kang
1Department of Obstetrics and Gynecology, Hallym University Hospital, Seoul, Korea.

Aim:
To identify the preoperative risk factors affecting the conversion to laparotomy during vaginal hysterectomy (VH) for benign uterine conditions.
Material And Methods:
The charts were reviewed for all patients who underwent VH between 1 January 2003 and 31 December 2008 at Hallym University Hospital, Seoul.
Results:
The rate of conversion to laparotomy was 3.7% (32 cases). Factors that were independently associated with the risk of conversion to laparotomy were found to be low parity (conversion 1.43 vs VH 1.92, P=0.021), previous abdominal surgery (conversion 0.71 vs, VH 0.26, P=0.012), pelvic adhesion (conversion 1.25 vs VH 0.04, P=0.000), and large uterine weight (conversion 345.15g vs VH 222.38g, P=0.005). In the conversion group, the operative time was longer (conversion 144.84min vs VH 77.67min, P=0.000), and estimated blood loss was also greater (conversion 656.25mL vs VH 358.47mL, P=0.00). Postoperative hemoglobin change (conversion 1.65g/dL vs VH 1.23g/dL, P=0.046) and transfusion rate were also greater in the conversion group (conversion 0.75 vs VH 0.01, P=0.001).
Conclusion:
VH is the main procedure for benign uterine disease and is successfully performed in most cases. But several factors, including low parity, previous abdominal surgery, pelvic adhesion and large uterine weight can affect the risk of conversion to laparotomy.

