Related Experiment Video
Updated: May 28, 2026

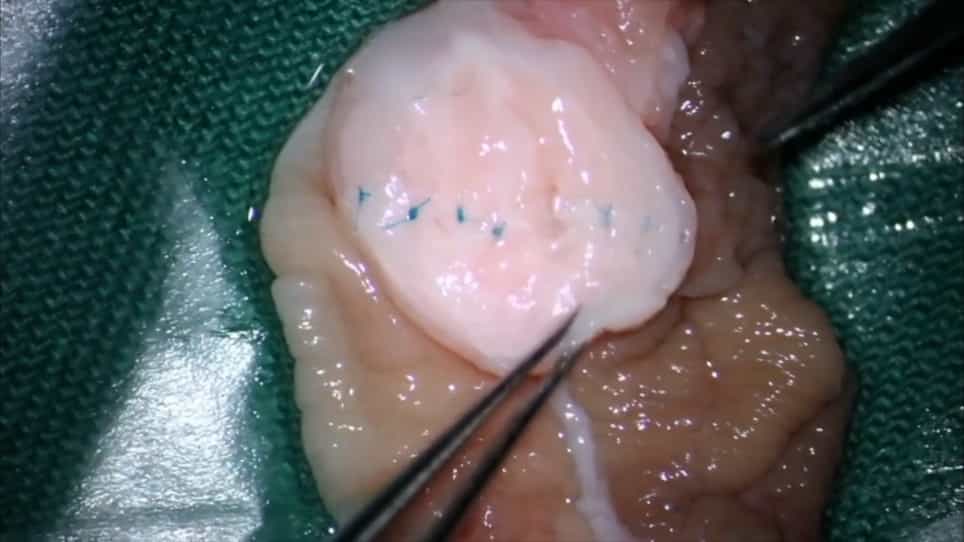
Urethral Stricture Induction Followed by Buccal Mucosa Graft Urethroplasty in a Rat Model
Published on: April 28, 2023
Single-stage dorsal inlay for reconstruction of recurrent peno-glandular stenosis
Patrick J Bastian1, Margit Mayer, Stefan Tritschler
1Urologische Klinik und Poliklinik, Klinikun der Universität München-Campus Großhadern, Ludwig-Maximilians-Universität, Marchioninistr. 15, 81377 Munich, Germany. patrick.bastian@med.uni-muenchen.de

Objective:
To evaluate the validity of a single-stage dorsal inlay for recurrent peno-glandular stenosis following previous endourological or open urethroplastic surgery. Urethral glanular reconstruction included a deep dorsal incision followed by complete scar excision to create a deep groove presenting well-vascularized recipient bed ensuring appropriate graft healing.
Materials And Methods:
Between April 2002 and January 2008, a total of 34 patients (mean age 51.5 years, 14-85 years) were enrolled in the study. Congenital anomalies included hypospadia (n = 19, 53%) and epispadia (n = 2, 6%). Condition of strictures was either iatrogenic (n = 7), due to infection (n = 5), or traumatic (n = 1). Foreskin grafts were used in 13 cases, foreskin and buccal mucosa in one case, penile skin in 6 cases, and inguinal skin/thigh (harvested by electrodermatom) in 14 cases. The combination of meticulous scar excision with a deep incision of the glans was used to provide a well-vascularized grafting bed, thus ensuring excellent graft healing. The outcome analysis included urinary flow, urethral calibration >18 ch, voiding cystometry, and patient's satisfaction in a follow-up regime every 3 months.
Results:
The average graft length was 4.7 cm (median 8, range 1.5-14). Mean follow-up was 70 months. In 31 patients (91%), no recurrent glanular stenosis was observed resulting in a post-operative flow of average 26.2 ml/s (11-53). Three post-operative wound infections occurred resulting in stricture recurrence, which was treated with internal urethrotomy, buccal mucosa, or penile skin inlay, respectively. Cosmetic results were satisfactory in all patients. Post-operative voiding parameters were significantly improved (P < 0.001).
Conclusion:
The single-stage dorsal inlay for reconstruction of peno-glandular stenosis represents a reliable method even if the urethral plate is severely scarred or has been excised during previous surgery. The good results imply that a well-vascularized graft and the technical approach seem to be more important than the substitute material.