Related Experiment Video
Updated: May 28, 2026

Quantification of the Immunosuppressant Tacrolimus on Dried Blood Spots Using LC-MS/MS
Published on: November 8, 2015
Tacrolimus dose and blood concentration variability in kidney transplant recipients undergoing conversion from twice
I Kurnatowska1, J Krawczyk, T Oleksik
1Department of Nephrology, Hypertension and Kidney Transplantation, Medical University of Łódź, Łódź, Poland.

Introduction:
Maintenance of the target blood levels of immunosuppressive drugs is one of the main factors determining transplant function. The aim of this study was to assess the effect of the conversion of tacrolimus from twice daily (Tc) to the prolonged release form administered once daily (Tc-pr) including the variability of blood concentrations and glomerular filtration rates in kidney transplantation patients.
Materials And Methods:
This retrospective analysis evaluated 52 patients including 23 females, and 29 males with established grafts who underwent a scheduled change of treatment from Tc to Tc-pr. We examined data from six consecutive visits before and six visits after conversion.
Results:
The average daily dose of Tc was 3.8±2.6 mg/24 h, whereas mean coefficient of variation (CoV) calculated from the visits before conversion was 68%. After the conversion, the mean total daily dose of Tc-pr was not significantly lower (3.2±1.8 mg), as was the mean CoV at six subsequent visits 57% (P=ns). Blood concentrations in both analyzed periods remained in the target range (Tc-pr 6.7±2.9 ng/mL versus Tc-pr 5.0±1.11) with a lower CoV in the case of Tc-pr compared to Tc (22% versus 44%; P<.001). There was no difference in graft function in the analyzed periods. After conversion, lower blood glucose levels were observed: 103.4±28.3 mg/dL versus 95±25.9 mg/dL (P<.03).
Conclusions:
The slow-release form of tacrolimus provided greater stability of drug blood concentrations compared with the standard form administered twice daily. The change of the tacrolimus treatment from Tc to Tc-pr dosing did not effect organ function but seemed to improve glycemic control.
Related Concept Videos
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:15
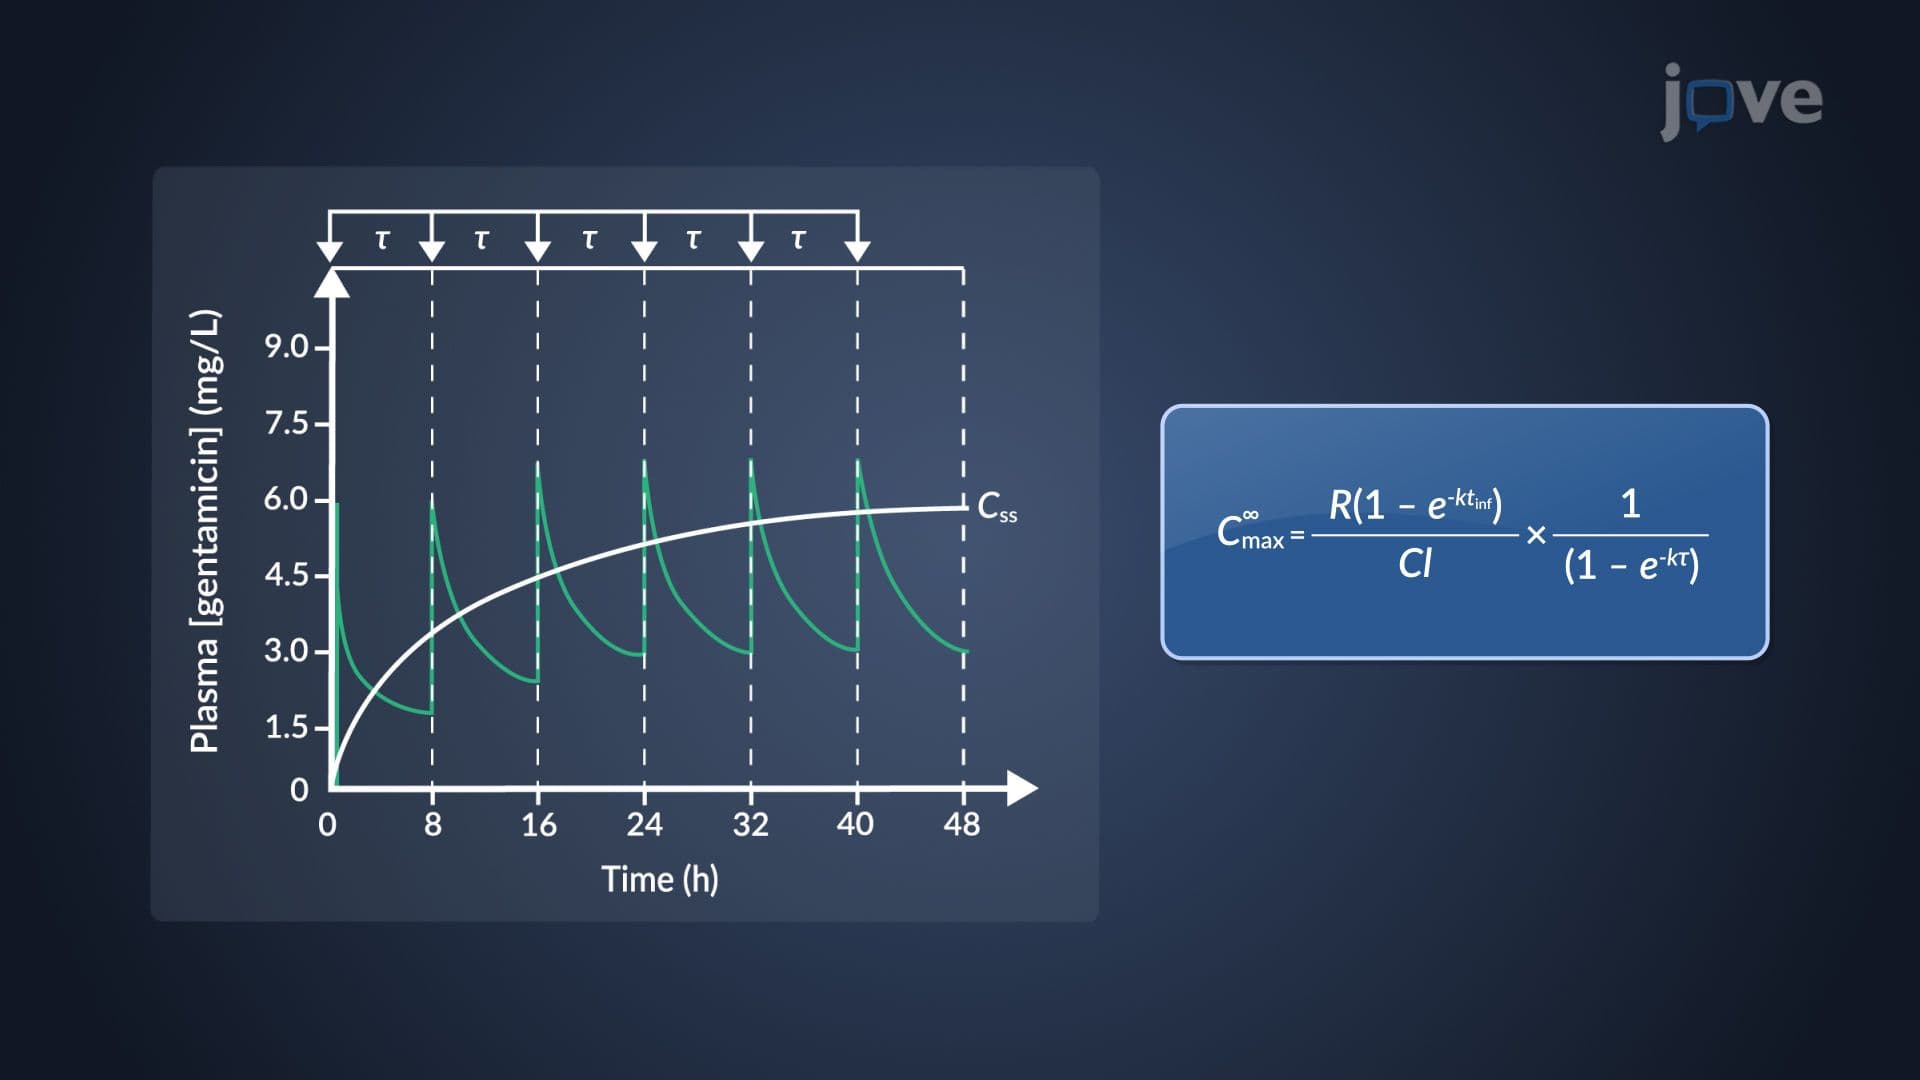
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:25
Drug Dosing in Renal Diseases: Measurement of Serum Creatinine Concentration and Clearance
 01:24
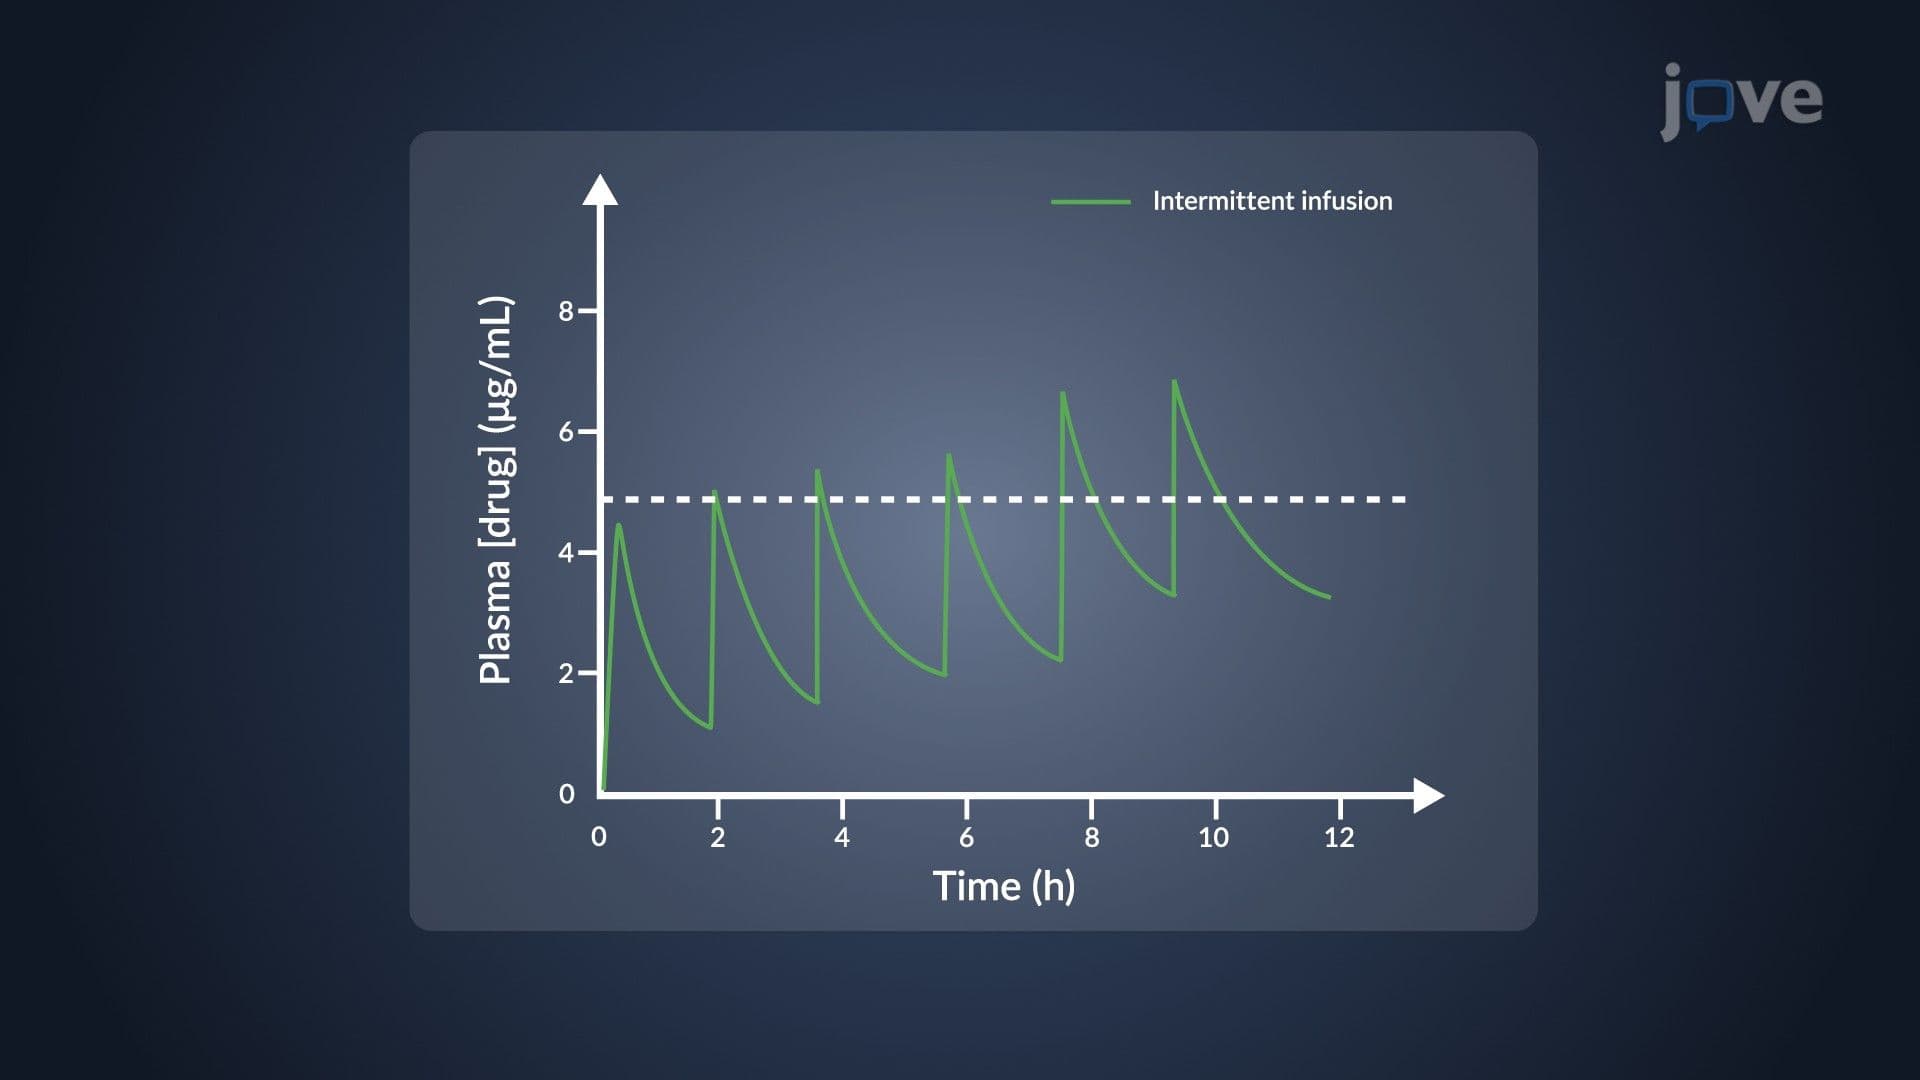
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:28
Drug Dosing in Renal Diseases: Estimation of Glomerular Filtration Rate Based on Serum Creatinine Concentration
 01:01
Dosage Regimens: Partial Pharmacokinetic Parameters