Related Experiment Video
Updated: May 28, 2026

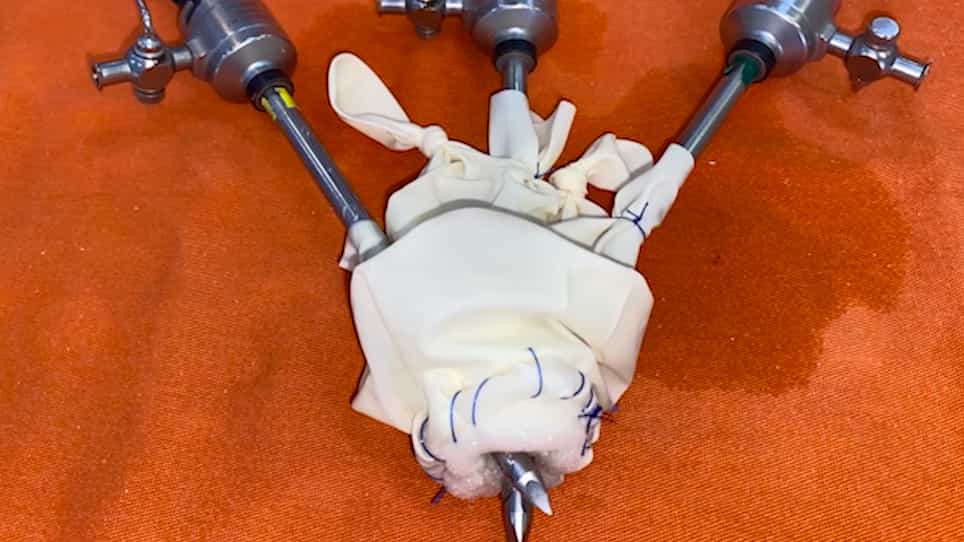
Manufacture of a Multi-Purpose Low-Cost Animal Bench-Model for Teaching Tracheostomy
Published on: May 18, 2019
Management of acquired tracheoesophageal fistula with various clinical presentations
Şule Yalçin1, Arbay O Ciftci, Ibrahim Karnak
1Department of Pediatric Surgery, Hacettepe University Faculty of Medicine, 06100 Ankara, Turkey. suleyal@hacettepe.edu.tr

Purpose:
To determine the best therapeutic approach for acquired tracheoesophageal fistulae in childhood by evaluation of distinct clinical presentations requiring different surgical management based on our clinical experience.
Patients And Methods:
Seven patients with acquired tracheoesophageal fistula seen between 1999 and 2010 were retrospectively studied with regard to the presenting findings, diagnostic evaluation, therapeutic approach, and outcomes.
Results:
Five girls and two boys with a median age of 36 months (range, 2-156 months) were treated for acquired tracheoesophageal fistula. The presenting symptoms were respiratory difficulty (n = 3), coughing (n = 2), and dysphagia with coughing (n = 2), with a median duration of 30 days (range, 1-730 days). The etiologies were disc battery ingestion (n = 3), placement of endoesophageal prosthesis for caustic esophageal stricture (n = 2), corrosive ingestion with extensive burn (n = 1), and blunt chest trauma with subsequent emergency tracheotomy (n = 1). The site of the fistulae were proximal (n = 3) and middle (n = 1) trachea, left main bronchus (n = 1), and nearly the entire posterior wall of the trachea (n = 2). The patients were variously managed: conservatively with eventual spontaneous closure (n = 1), primary repair (n = 2), and colon interposition after cervical esophagostomy (n = 4) based on the clinical evaluation on admission and the follow-up status. Stenosis of the proximal esophagus (n = 2) and esophagocolonic anastomosis (n = 2) were the only complications encountered after treatment and were successfully managed with dilatation.
Conclusions:
The best therapeutic approach for acquired tracheoesophageal fistula can be determined with careful consideration of relevant parameters on admission, including medical history, presenting findings, etiology, and characteristics of the fistula, in addition to the clinical evaluation in the follow-up period. In general, conservative management should precede definitive surgical intervention both to allow for possible spontaneous closure and also to achieve optimal preoperative status. Primary repair or a staged surgical approach can be best selected by giving priority to the patient's airway security.
Related Concept Videos
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:22
Trachea
Anatomical Features:
Location: About half of the trachea is situated in the neck, anterior to the esophagus, and extends from the larynx (at the level of the...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:28
Tracheostomy: Procedure and Tubes
Tracheostomy tubes can be made of semiflexible plastic (polyurethane or silicone), rigid plastic, or metal, and they come in...
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:23
Oxygen Delivering System III: Tracheostomy and T-piece
Tracheostomy
A tracheostomy is a surgically created opening (stoma) in the anterior part of the trachea. It is used to establish a patient airway, bypass an upper airway obstruction, simplify the removal of secretions, permit long-term...