Related Experiment Video
Updated: May 28, 2026

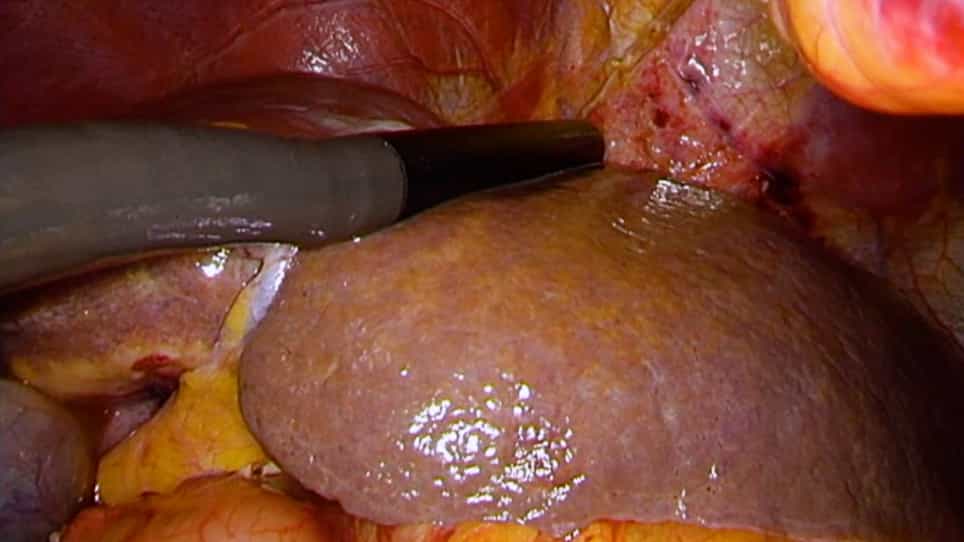
Laparoscopic Left Hemihepatectomy Combined with Caudate Lobe Resection
Published on: April 11, 2025
Caudate lobe resection for hepatocellular carcinoma
Mohamed Abdel Wahab1, Omar Fathy, Ehab Elhanafy
1Mansoura University, Mansoura, Rgypt. wahab_m_eg@yahoo.com

Insights
Isolated caudate lobe resection for hepatocellular carcinoma (HCC) is a feasible surgical option. This procedure offers low morbidity and no mortality, with careful technique being essential for successful outcomes in rare HCC cases.
Area of Science:
- Hepatobiliary Surgery
- Surgical Oncology
- Gastroenterology
Background:
- Hepatocellular carcinoma (HCC) originating in the caudate lobe is a rare clinical presentation.
- Surgical treatment for caudate lobe HCC is complex due to anatomical challenges.
Purpose of the Study:
- To evaluate the surgical outcomes of isolated caudate lobe resection for HCC.
- To assess the feasibility and safety of this specific surgical approach.
Main Methods:
- Retrospective analysis of 30 consecutive patients with HCC originating in the caudate lobe.
- Patients underwent isolated caudate lobe resection.
Main Results:
- All patients achieved tumor-negative surgical margins.
- The hospital morbidity rate was 33% with no postoperative mortality.
- Overall survival rates at 1, 3, and 5 years were 62%, 34%, and 11%, respectively.
Conclusions:
- Isolated caudate lobe resection is a feasible and safe procedure for HCC.
- Low morbidity and nil mortality can be achieved with careful technique and detailed anatomical knowledge.
- This approach is viable for managing rare caudate lobe hepatocellular carcinoma.
Background/Aims:
Hepatocellular carcinoma (HCC) originating in the caudate lobe is rare, and the treatment for this type of carcinoma is a complex surgical procedure. We aimed to evaluate the surgical outcomes after isolated caudate lobe resection for HCC.
Methodology:
We retrospectively analyzed 30 consecutive patients with HCC originating in the caudate lobe who underwent isolated caudate lobe resection.
Results:
Thirty patients underwent caudate lobe resection for HCC. The main sites of the tumors were located in the Spiegel lobe, the paracaval portion and caudate process. The surgical margin was tumor negative in all of the patients. The median tumor size was 4.3cm. The mean operative time was 230 ± 50min and the intraoperative blood loss was 1200 ± 200mL. The hospital morbidity rate was 33%. There was no postoperative mortality. The mean survival rate was 25.3+11.7 months. The overall survival rates were 62%, 34% and 11% at 1, 3 and 5 years, respectively. The disease free survival rate after isolated caudate lobectomy was 31% at 3 years. Recurrence was noted in 12 patients (40%). Eleven patients were identified as having intrahepatic recurrences and 1 patient as having peritoneal dissemination.
Conclusions:
Isolated caudate lobe resection is a feasible procedure and can be undertaken with low morbidity and nil mortality. Careful technique and detailed anatomic knowledge of the caudate lobe are essential for this procedure.