Related Experiment Video
Updated: May 28, 2026
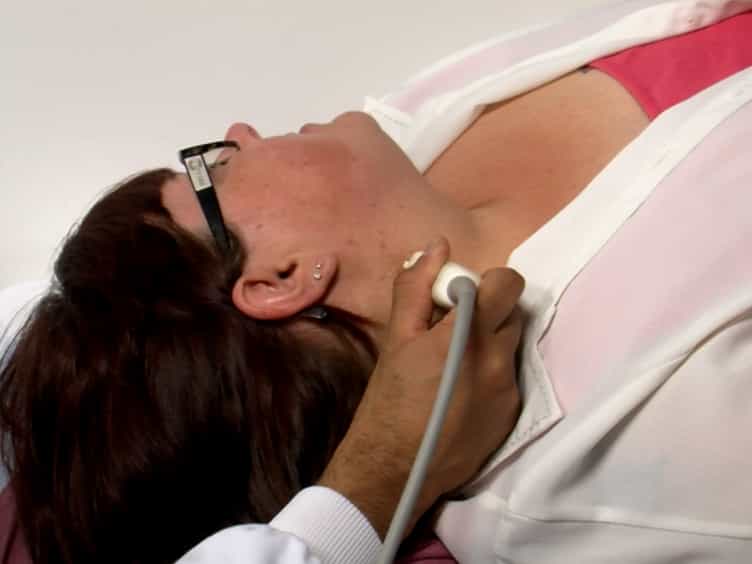

A Methodological Approach to Non-invasive Assessments of Vascular Function and Morphology
Published on: February 7, 2015
Carotid artery intima-media thickness in patients with autoimmune connective tissue diseases: a case-control study
Vincenzo Bruzzese1, Cinzia Marrese, Angelo Zullo
1Internal Medicine and Reumatology, Ospedale Nuovo Regina Margherita, Vie E. Morosini, 30, 00153, Rome, Italy, vinbruzzese@tin.it.

Insights
Cardiovascular risk in autoimmune rheumatic disorders is linked to traditional factors like age, not systemic inflammation. Preclinical atherosclerosis was similar in patients and controls, highlighting the importance of managing common risk factors.
Area of Science:
- Rheumatology
- Cardiovascular Medicine
- Immunology
Background:
- Patients with autoimmune rheumatic disorders exhibit higher cardiovascular (CV) event rates and mortality.
- While traditional CV risk factors are prevalent, systemic inflammation is debated as an independent CV risk factor, especially in rheumatoid arthritis (RA).
Purpose of the Study:
- To investigate the prevalence of preclinical atherosclerosis in patients with autoimmune rheumatic disorders compared to matched controls.
- To identify independent predictors of early atherosclerosis in this patient population.
Main Methods:
- A case-control study involving 152 patients with autoimmune rheumatic disorders and 140 matched controls.
- Assessment of early atherosclerosis using carotid artery intima-media thickness (IMT) measurement (normal ≤ 0.9 mm, abnormal > 0.9 mm).
- Multivariate analysis to determine predictors of pathological IMT.
Main Results:
- No significant difference in the prevalence of abnormal IMT (>0.9 mm) between patients (61%) and controls (69%).
- Similar IMT distribution observed between rheumatoid arthritis patients and controls.
- Presence of CV risk factors significantly increased the prevalence of pathological IMT in both patients (77.1%) and controls (84.6%).
- Age and traditional CV risk factors, not rheumatic disease, were identified as independent predictors of pathological IMT.
Conclusions:
- Autoimmune rheumatic diseases, including RA, do not show a higher prevalence of preclinical arterial wall atherosclerotic damage compared to matched controls.
- Traditional CV risk factors and patient age are the primary determinants of preclinical atherosclerosis in patients with autoimmune rheumatic disorders.
Abstract:
Patients with autoimmune rheumatic disorders have an increased incidence of cardiovascular (CV) events and mortality. Despite this being related to a high prevalence of the traditional CV risk factors, systemic inflammation has been postulated to be an independent CV risk factor, particularly in patients with rheumatoid arthritis (RA). However, data are still controversial. We designed a case-control study, in which patients with autoimmune rheumatic disorders were matched with age-, sex-matched controls. Prevalence of early atherosclerosis was assessed by carotid artery intima-media thickness (IMT) measurement. IMT values were considered normal (IMT ≤ 0.9 mm) or abnormal (IMT > 0.9). Multivariate analysis was performed to identify predictors of pathological IMT. Overall, 152 patients and 140 matched controls were enrolled. Prevalence of >0.9 mm IMT values did not significantly differ between patients with autoimmune rheumatic disorders and controls (61 vs. 69%, p = 0.1). In detail, a similar IMT distribution between the 69 RA patients and controls was observed. Cases with a CV risk factor showed a higher prevalence of pathological IMT as compared to those without any risk factor, both in patients (77.1 vs. 38.6%; p < 0.0001) and controls (84.6 vs. 25%; p < 0.0001). At multivariate analysis, age and presence of CV risk factors were found to be independent predictors of >0.9 mm IMT, while RA as well as any other considered rheumatic disease were not. Our data found a similar prevalence of preclinical arterial wall atherosclerotic damage in patients with autoimmune rheumatic diseases and matched controls. Presence of traditional CV risk factors and patient age remain the main factors involved in preclinical atherosclerosis in patients with autoimmune rheumatic disorders, including RA.

Related Concept Videos
 01:27
Atherosclerosis II: Clinical Manifestations and Diagnostic Tests
 01:29
Autoimmune Disorders
Concept and Mechanism of Autoimmune Diseases
The immune system...
 01:22
Connective Tissue Cell Types
Fat cells (adipocytes), smooth muscle cells (myoblasts), and bone cells (osteoblasts) are some connective tissue cell types. Some immune system cells...
 01:22
Rheumatic Heart Disease II: Clinical Manifestations and Diagnostic Studies
 01:30
Atherosclerosis I: Introduction
 01:26
Atherosclerosis III: Management