Related Experiment Video
Updated: May 28, 2026
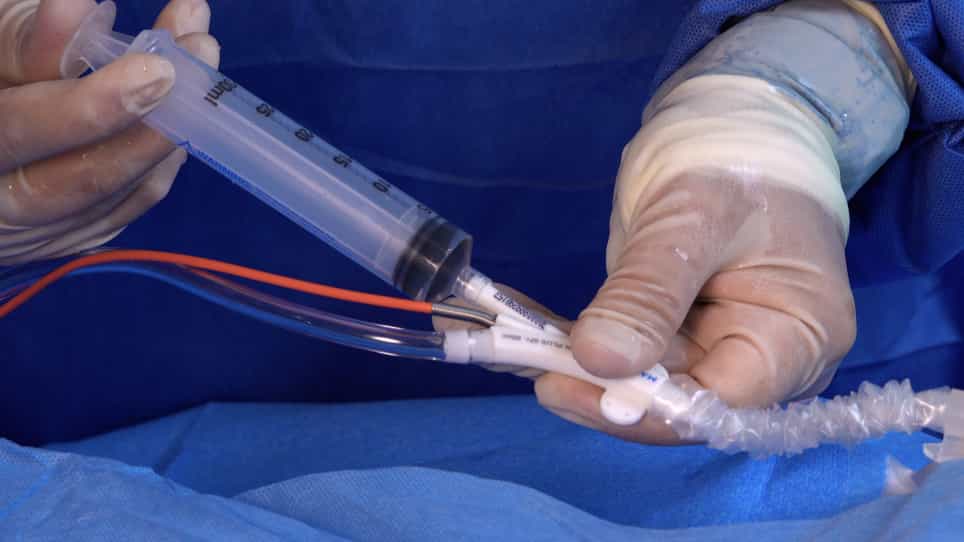

The Intra-Aortic Balloon Pump
Published on: February 5, 2021
Gastric perforation and subarachnoid hemorrhage secondary to intragastric balloon device
M A Sánchez-Pérez1, M Muñoz-Juárez, F Cordera-González de Cosío
1Department of General Surgery, American British Cowdray Medical Center, México City, Mexico.

Abstract:
Obesity is a major health problem worldwide that leads to high morbidity and mortality rates. Medical options for obesity treatment are multiple and invasive therapy may be classified as surgical and non-surgical. Intragastric balloon device placement is an invasive non-surgical option that may benefit some obese patients. Potential complications related to intragastric balloon placement are multiple and perforations at the esophagus or stomach are the most hazardous. Prompt surgical management is mandatory upon the diagnosis of gastric perforation secondary to intragastric balloon to avoid further complications and mortality. Here we report an unusual case of patient that suffered both a subarachnoid hemorrhage as well as a gastric perforation related to intragastric balloon in which early diagnosis and prompt surgical treatment lead to a successful outcome.

Related Concept Videos
 01:22
Esophageal Perforation-I: Introduction
The location of esophageal perforation can vary, occurring anywhere along the esophagus.
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:23
Gastritis III: Clinical Manifestations and Management
Clinical manifestations of acute gastritis
The patient with acute gastritis may have a rapid onset of symptoms, such as epigastric pain or discomfort, dyspepsia, anorexia, hiccups, or nausea and vomiting, which can last from a few hours to a few days. Erosive or hemorrhagic gastritis may cause bleeding, which may manifest as blood in vomit or as...
 01:07
Intestinal Obstruction II: Pathophysiology
 01:26
Aneurysm III: Interprofessional Care
 01:25
Peptic Ulcer Disease III: Clinical Manifestations and Complications