Related Experiment Video
Updated: May 28, 2026
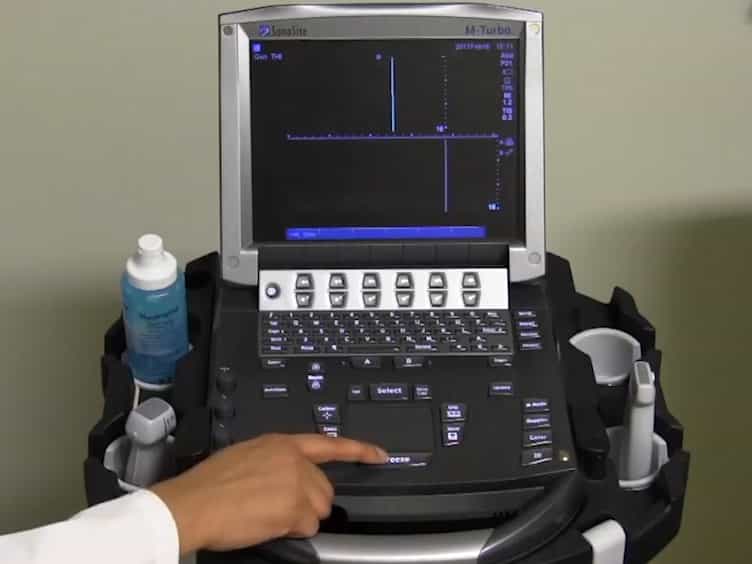

Bedside Ultrasound for Guiding Fluid Removal in Patients with Pulmonary Edema: The Reverse-FALLS Protocol
Published on: July 28, 2018
Flexible diuretic titration in chronic heart failure: where is the evidence?
Mariann R Piano1, Marilyn A Prasun, Thomas Stamos
1Department of Biobehavioral Health Science, College of Nursing, University of Illinois, Chicago, Illinois, USA. piano@uic.edu

Insights
Flexible diuretic dosing in heart failure (HF) may reduce hospitalizations and improve quality of life. More research is needed, especially for HF with preserved ejection fraction, to confirm these benefits.
Area of Science:
- Cardiology
- Pharmacology
- Clinical Medicine
Background:
- Heart failure (HF) guidelines recommend flexible diuretic dosing for fluid overload management.
- Evidence supporting improved clinical outcomes with flexible diuretic regimens is limited.
- This review examines the evidence for flexible diuretic dosing in outpatient HF management.
Purpose of the Study:
- To summarize and review the evidence supporting flexible diuretic regimens in outpatient heart failure patients.
- To assess the effectiveness of flexible diuretic dosing on clinical outcomes.
- To identify gaps in the current research.
Main Methods:
- A systematic review of relevant studies was conducted.
- Nine studies were identified, including five randomized trials.
- Two randomized trials specifically evaluated flexible diuretic titration's sole contribution.
Main Results:
- Flexible diuretic dosing may be associated with reduced emergency room visits.
- Individualized diuretic dosing showed potential for reduced rehospitalization rates.
- Improved quality of life was observed in heart failure patients with reduced ejection fraction.
Conclusions:
- Limited randomized trials specifically assessed flexible diuretic dosing in outpatient HF.
- Data are insufficient for heart failure patients with preserved ejection fraction.
- Well-designed prospective randomized trials are critically needed to validate this strategy.
Background:
Several sets of heart failure (HF) consensus/guideline statements support the use of a flexible diuretic dosing regimen for HF outpatient management of fluid overload-related signs and symptoms. However, despite the widespread acceptance of such an approach, the evidence supporting the effectiveness of this approach in improving clinical outcomes is unknown. The primary objective of this manuscript was to summarize and review the evidence supporting the use of a flexible diuretic regimen in the management of outpatient heart failure patients.
Methods And Results:
A systematic review was performed, and 9 studies were identified relevant to the question of flexible diuretic titration in the setting of chronic heart failure. Among the 9 studies, 5 were randomized. Three of the randomized trials included flexible diuretic titration as part of a broader multifaceted disease management program, and only 2 were designed to specifically evaluate the sole contribution of flexible diuretic titration. Collectively, data from all of the studies reviewed supported the idea that flexible and individualized diuretic dosing is potentially associated with reduced emergency room visits, reduced rehospitalization, and improved quality of life in HF patients with reduced ejection fraction.
Conclusions:
To date, only 2 randomized clinical studies were identified that were designed to determine the effects of a flexible diuretic dosing regimen in outpatient HF patients with reduced ejection fraction. Data are lacking in HF patients with preserved ejection fraction. There is a critical need to test this strategy in well designed prospective randomized clinical trials.

Related Concept Videos
 01:22
Heart Failure Drugs: Diuretics
 01:30
Heart Failure V: Medical Management
 01:22
Heart Failure VI: Adjunct Therapies
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System
 01:29
Heart Failure II: Pathophysiology