Natural history of prenatal ventricular septal defects and their association with foetal echocardiographic features
Related Experiment Video
Updated: May 27, 2026
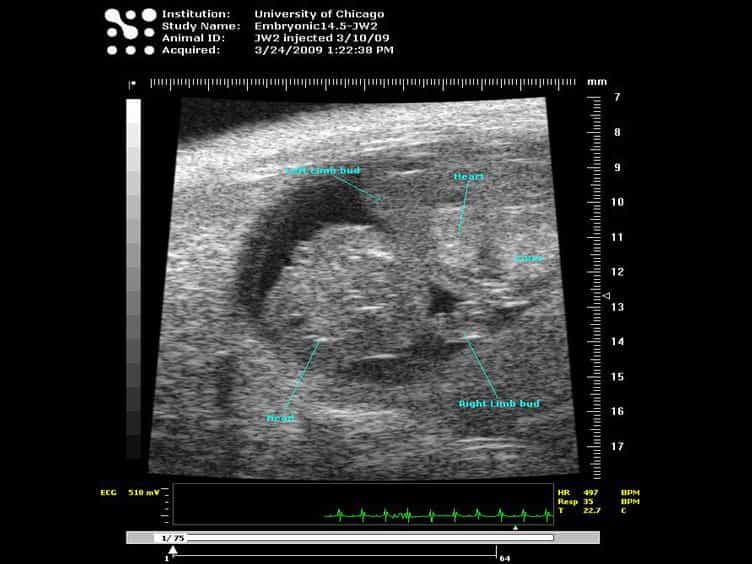
Murine Fetal Echocardiography
Published on: February 15, 2013
Youpeng Jin1, Aiyun Wang, Yulin Wang
1Pediatric Department, Shandong Provincial Hospital affiliated to Shandong University, Jinan, Shandong, China.

Insights
Small and muscular ventricular septal defects (VSDs) show high closure rates and early spontaneous closure, either in utero or postnatally. Defect size and location significantly influence the natural history of VSDs.
Area of Science:
- Pediatric Cardiology
- Fetal Echocardiography
- Congenital Heart Defects
Background:
- Ventricular septal defects (VSDs) are common congenital heart anomalies.
- Understanding the natural history of VSDs is crucial for management.
- Prenatal diagnosis allows for early monitoring and intervention planning.
Purpose of the Study:
- To track the progression of VSDs from prenatal diagnosis to age 3 years.
- To analyze factors influencing VSD closure, including size and location.
- To correlate fetal echocardiographic features with VSD closure rates and timing.
Main Methods:
- Prospective study of 125 infants with isolated VSD diagnosed via fetal echocardiography.
- Regular ultrasonography every 2 weeks until VSD closure or 3 years postnatally.
- Analysis of VSD closure rates based on size, location (muscular vs. perimembranous), and Doppler flow patterns.
Main Results:
- VSDs can close spontaneously in utero or postnatally; 55 closed postnatally at a mean age of 13.7 months.
- Muscular VSDs had significantly higher closure rates (92.3%) compared to perimembranous VSDs (64.3%).
- All VSDs ≤3 mm closed, while 79.5% of larger defects closed by age 3. Small VSDs closed earlier, with 60.9% closing by 1 year.
Conclusions:
- Ventricular septal defects exhibit significant natural variation in closure.
- VSD size and location are critical determinants of spontaneous closure.
- Small, muscular VSDs have a favorable prognosis with high rates of early spontaneous closure.
Objective:
To describe the evolution of ventricular septal defects in infants from intra-uterine diagnosis to the age of 3 years or until documented echocardiographic closure of the defect, as well as any relationship between closure rate, time and foetal echocardiographic features.
Methods:
Between January, 2004 and December, 2006, 268 cases of congenital cardiac defect were detected in 14,993 pregnancies referred to our hospital for routine foetal echocardiography; of these cases, 125 had isolated ventricular septal defect. The mothers were scheduled for regular ultrasonography every 2 weeks from diagnosis until the ventricular septal defect closed or 3 years postnatally.
Results:
Of the 125 cases of ventricular septal defects, the pregnancy was terminated in 25, four resulted in death, two defects closed spontaneously in utero, 55 closed at a mean age of 13.7 months postnatally, 17 were treated with surgery, nine remained unclosed, and 13 cases were lost to follow-up. Only 7.7% of muscular ventricular septal defects remained patent as compared with 35.7% of perimembranous ventricular septal defects (p is less than 0.01). Muscular ventricular septal defects closed earlier than perimembranous ventricular septal defects. All the ventricular septal defects less than or equal to 3 millimetres closed, whereas only 79.5% of the defects greater than 3 millimetres closed before the age of 3 years; 60.9% of the defects less than or equal to 3 millimetres closed before the age of 1 year as compared with 41.7% of the defects greater than 3 millimetres. The velocity of right-to-left flow was negatively correlated with closure rate but not related to closure period.
Conclusion:
Ventricular septal defects can close in utero or during the postnatal period, and both the size and site play a role in the natural history, with small and muscular ventricular septal defects having a high closure rate and early closure.

Related Concept Videos
 01:27
Development of the Heart
As the embryo undergoes lateral folding, these paired tubes approach each other, merging into a single primitive heart tube by...
 01:23
Mitral Stenosis II: Clinical features and Diagnostic Tests
 01:14
Fetal Circulation
Two umbilical arteries transport blood from the fetus to the placenta. At the placenta, the blood absorbs oxygen and nutrients while simultaneously eliminating waste products. This oxygen-enriched and nutrient-rich blood then returns to the fetus through one...
 01:20
Imaging Studies for Cardiovascular System II:Types of Echocardiography
Types of Echocardiography
Transthoracic Echocardiography (TTE)
TTE is the most common type of echocardiogram which involves placing a transducer on the patient's chest, emitting sound waves to create heart images. TTE is invaluable for evaluating the heart's size, structure, and motion, making it particularly useful for diagnosing...