Related Experiment Video
Updated: May 26, 2026
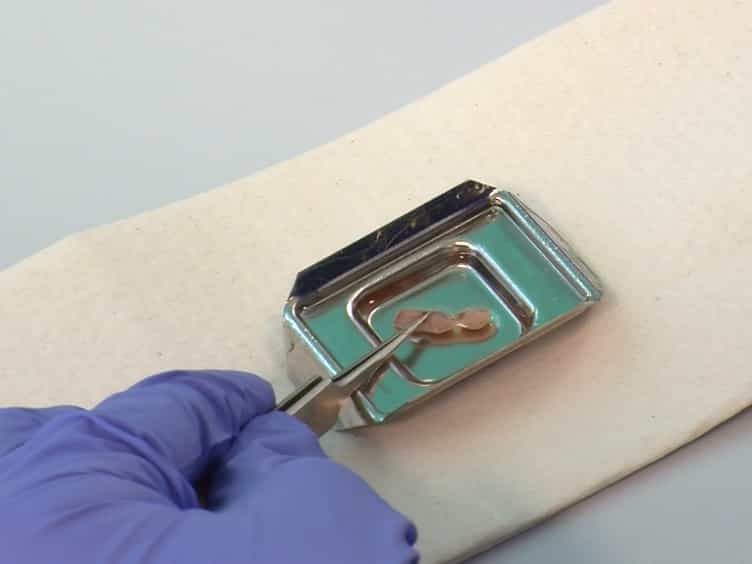

Assessment of Maternal Vascular Remodeling During Pregnancy in the Mouse Uterus
Published on: December 5, 2015
Challenges posed to the maternal circulation by pregnancy
Gloria Valdés1, Jenny Corthorn
1Centro de Investigaciones Médicas y Departamento Nefrología, Escuela Medicina, Pontificia Universidad Católica, Santiago, Chile.

In primates, adequate growth of the fetus depends on the development of the uteroplacental unit. On the fetal side, this is achieved by the creation of the vascular network of the placenta. On the maternal side, the transformation of the spiral arteries into saccular nonreactive vessels by the trophoblast provides high blood flow to the intervillous space. Apart from the changes in the uterine arteries, the mother expands her plasma volume - at the expense of stimulating the renin-angiotensin-aldosterone system - and her cardiac output. In the maintaining of normotension in the face of an increased cardiac output and plasma volume, the renin-angiotensin-aldosterone system requires an enhanced vasodilator synthesis. Finally, in the late stages of pregnancy, a normal endothelial function is required to provide an ample margin to the activation provoked by deportation of syncytiotrophoblast fragments/factors to the maternal circulation. These four adaptative processes require various interrelated vasodilator systems. Deficient adaptations cause isolated or proteinuric arterial hypertension, intrauterine growth restriction, preterm delivery, and stillbirths, among others. Moreover, a normal or a defective adaptation to pregnancy influences maternal cardiovascular health in later life, as evidenced by various studies, most of them epidemiological; thus, pregnancy is now considered a stress test to the maternal cardiovascular system. Because of this, women planning to become pregnant should be screened for clinical and biochemical cardiovascular risks. Inversely, women presenting with hypertension in pregnancy should be thoroughly studied to detect and correct cardiovascular risks. The incorporation of the predictive value of a hypertensive pregnancy should help reduce cardiovascular disease in women.
In primates, adequate growth of the fetus depends on the development of the uteroplacental unit. On the fetal side, this is achieved by the creation of the vascular network of the placenta. On the maternal side, the transformation of the spiral arteries into saccular nonreactive vessels by the trophoblast provides high blood flow to the intervillous space. Apart from the changes in the uterine arteries, the mother expands her plasma volume - at the expense of stimulating the renin-angiotensin-aldosterone system - and her cardiac output. In the maintaining of normotension in the face of an increased cardiac output and plasma volume, the renin-angiotensin-aldosterone system requires an enhanced vasodilator synthesis. Finally, in the late stages of pregnancy, a normal endothelial function is required to provide an ample margin to the activation provoked by deportation of syncytiotrophoblast fragments/factors to the maternal circulation. These four adaptative processes require various interrelated vasodilator systems. Deficient adaptations cause isolated or proteinuric arterial hypertension, intrauterine growth restriction, preterm delivery, and stillbirths, among others. Moreover, a normal or a defective adaptation to pregnancy influences maternal cardiovascular health in later life, as evidenced by various studies, most of them epidemiological; thus, pregnancy is now considered a stress test to the maternal cardiovascular system. Because of this, women planning to become pregnant should be screened for clinical and biochemical cardiovascular risks. Inversely, women presenting with hypertension in pregnancy should be thoroughly studied to detect and correct cardiovascular risks. The incorporation of the predictive value of a hypertensive pregnancy should help reduce cardiovascular disease in women.


Related Concept Videos
 01:14
Fetal Circulation
Two umbilical arteries transport blood from the fetus to the placenta. At the placenta, the blood absorbs oxygen and nutrients while simultaneously eliminating waste products. This oxygen-enriched and nutrient-rich blood then returns to the fetus through one...
 01:11
Overview of Systemic Veins
The coronary sinus, the heart's principal vein, resides in the coronary sulcus on the heart's posterior aspect. This broad venous channel receives nearly all venous blood from the myocardium, the heart muscle. It is fed by three primary veins: the great cardiac vein, the middle...
 01:19
Mitral Valve Prolapse III: Nursing Management
 01:07
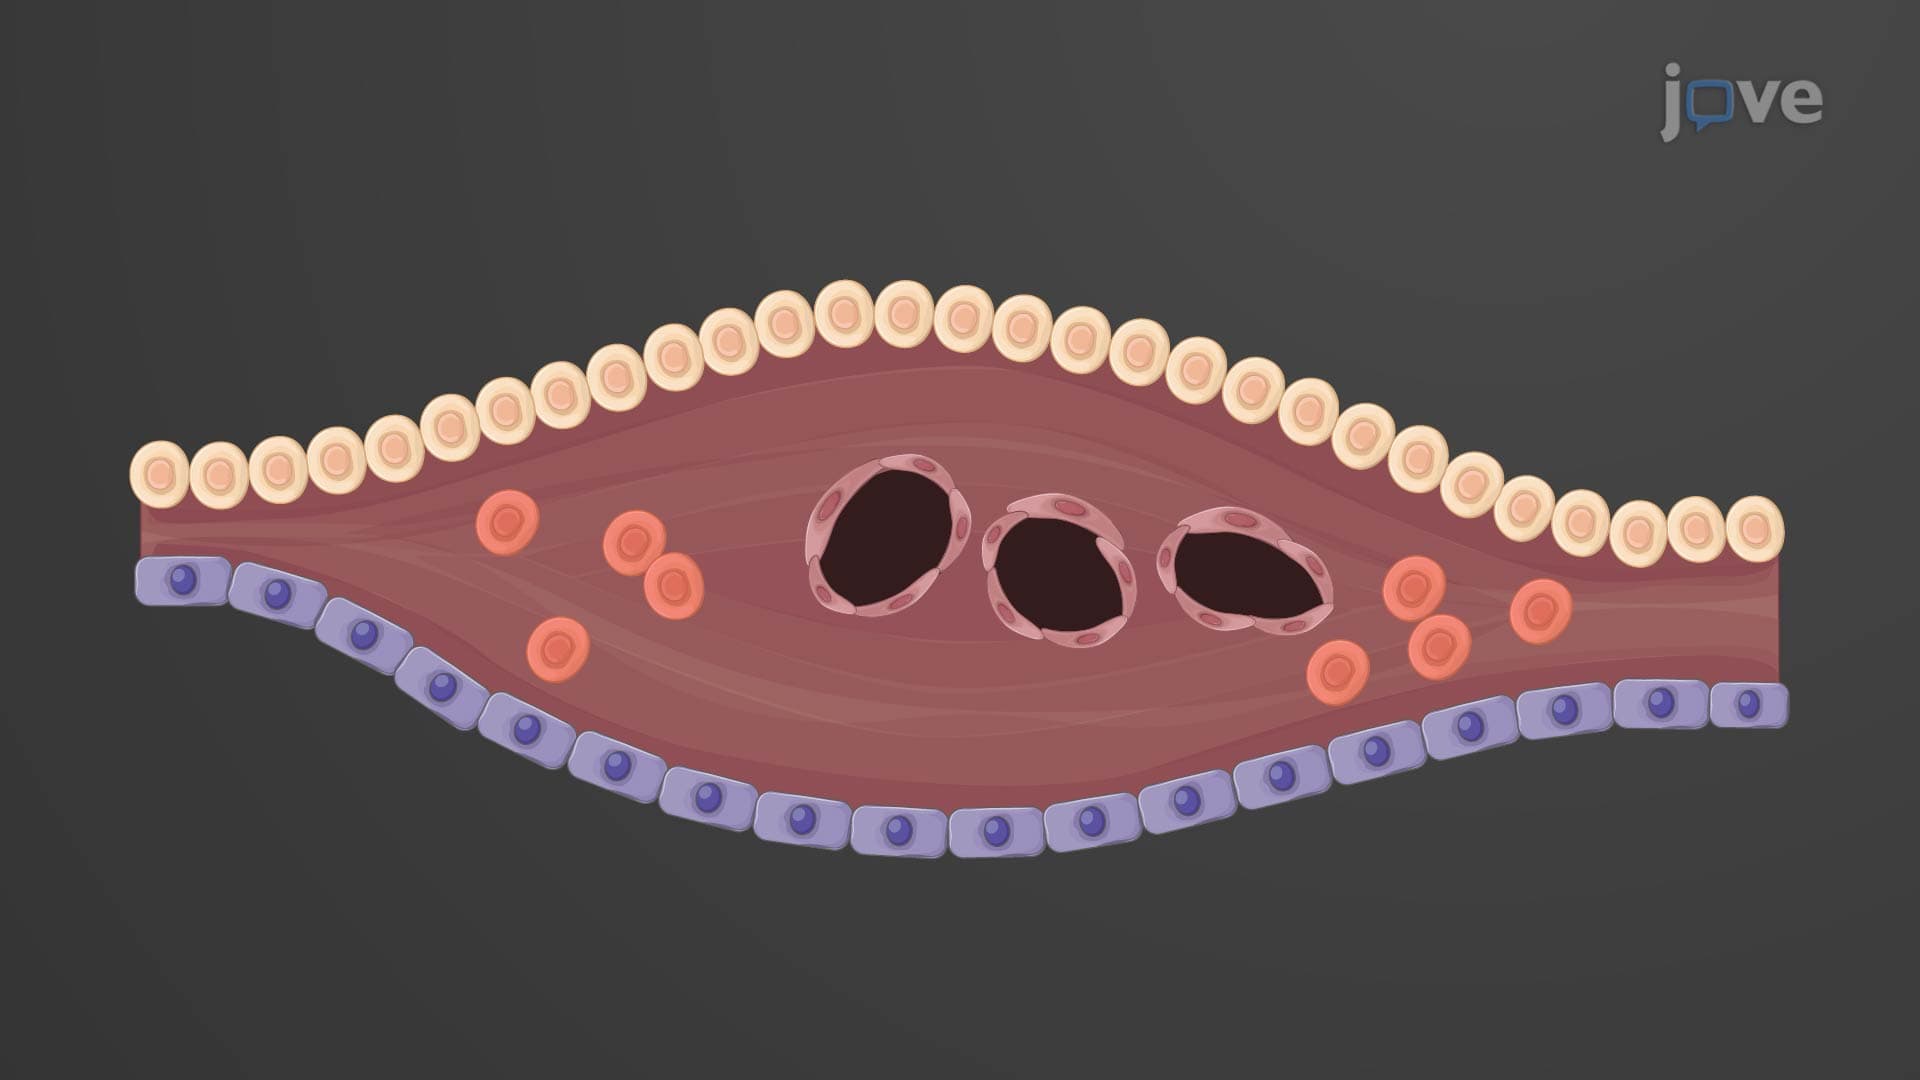
Development of Blood Vessels
The initial formation of this system is facilitated by the small amount of yolk present in the ovum and yolk sac. Blood vessels originate from...
 01:24
Blood Pressure Imbalances and Circulatory Shock
Blood Pressure: Hypertension and Hypotension
Normal blood pressure is 120/80 mm Hg. Elevated blood pressure is 120-129/under 80 mm Hg. Hypertension, warranting treatment at 130/80 mm Hg, is often asymptomatic and can lead to severe cardiovascular events, aneurysms, peripheral arterial disease, chronic renal disease, or cardiac...
 01:20
Vascular Resistance
The primary determinants of vascular resistance are vessel diameter, blood viscosity, and vessel length. Among these, vessel diameter plays the most significant role due to the fourth power relationship described by...