Related Experiment Video
Updated: May 26, 2026
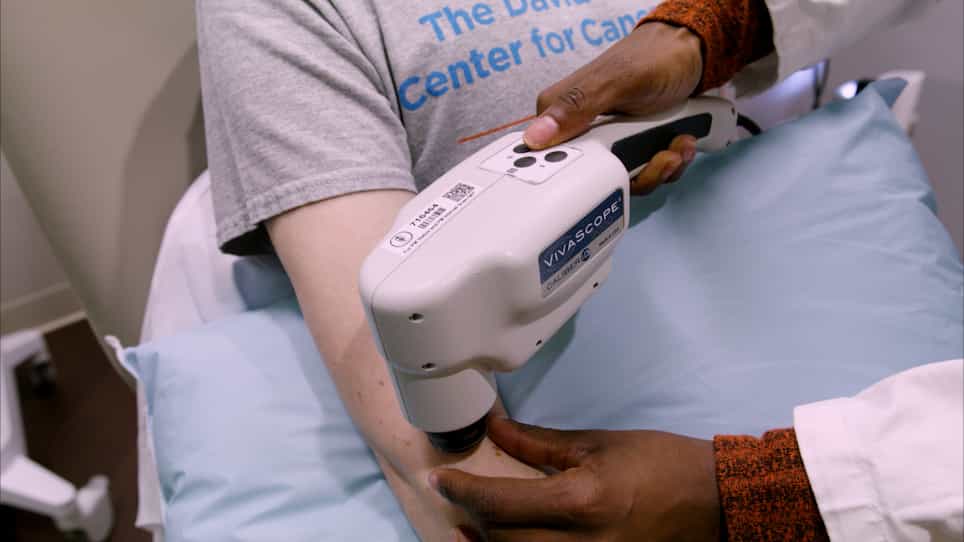

Combining Reflectance Confocal Microscopy with Optical Coherence Tomography for Noninvasive Diagnosis of Skin Cancers via Image Acquisition
Published on: August 18, 2022
Nodular cutaneous amyloidosis
Jessica Borowicz1, Leah Shama, Richard Miller
1Largo Medical Center, Largo, FL, USA. drjflowers@hotmail.com

Abstract:
A 56-year-old white man presented with a lesion on the right shoulder. The lesion developed during a short period and recently became irritated with occasional bleeding and mild pruritus. The patient denied pain. Medical history included melanoma, nonmelanoma skin cancer, diabetes mellitus type II, hyperlipidemia, multinodular thyroid goiter, and obesity. Medications and family and social history were noncontributory. Review of systems was negative. Examination revealed a slightly raised, friable yellow-pink waxy plaque located on the right shoulder (Figure 1). There was no evidence of excoriation, secondary infection, drainage, scale, crust, atrophy, lichenification, or telangiectasia. The patient had no mucosal or nail changes and the remainder of his skin examination was normal. A shave biopsy on the right shoulder revealed a nodular deposit of homogenous eosinophilic material associated with extravasated erythrocytes within the dermis. An infiltrate of lymphocytes and plasma cells was associated with the deposits. Immunohistochemical stains revealed positive plasma cells with kappa light chain and negative with lambda light chain. Congo red stain was positive and supported the diagnosis. The findings were consistent with nodular cutaneous amyloidosis (NCA) of the amyloid light-type. Initial work-up included referrals to hematology/oncology and to general surgery. The patient had a complete blood cell count (CBC), complete metabolic profile (CMP), serum protein electrophoresis (S-PEP), urine protein electrophoresis (U-PEP), 24-hour urine creatinine clearance, and protein, serum immunoglobulins and 132 microglobulin. These were all within normal limits. Abdominal/pelvic computed tomography and positron emission tomography scan also were within normal limits. Bone marrow biopsy showed no abnormalities. The patient underwent both an abdominal fat pad biopsy as well as a colonoscopy with rectal biopsy. Both were negative for amyloidosis. Initially, the patient's cutaneous amyloidosis remained localized and mild pruritus was controlled with low potency topical steroids. The patient was closely monitored by hematology/oncology and general surgery on a biannual basis to assess the possibility of progression to systemic amyloidosis. Over the course of the subsequent two years, the patient developed multiple similar lesions across the back, shoulders, and chest, which were biopsied and found to be consistent with NCA. Progression of the cutaneous nodules led to disfiguring, painful, and friable pink to yellow waxy papules coalescing into plaques with obvious hemorrhage diffusely over the trunk (Figure 2). In lieu of the painful and disfiguring progression of disease, the patient desired a more aggressive treatment plan. At present, the treatment option recommended to the patient is carbon dioxide laser ablation. Hematology/oncology recommendation consists of a general systemic amyloid reevaluation annually, including CBC, CMP, S-PEP, U-PEP, 24-hour urine collection with creatinine clearance, and history and physical examination.

Related Concept Videos
 01:30
Skin Cancer
Basal Cell Carcinoma (BCC): BCC is the most common type of skin cancer, accounting for about 80% of cases. It typically develops in...
 03:03
Amyloid Fibrils
Amyloid deposits were observed as early as 1639 in the liver and the spleen. In 1854, Rudolph Virchow performed iodine staining, normally used to...
03:03Amyloid Fibrils
Amyloid deposits were observed as early as 1639 in the liver and the spleen. In 1854, Rudolph Virchow performed iodine staining, normally used to...
 01:23
Skin Diseases and Disorders
Gram-positive Staphylococcus spp. and Streptococcus spp. are responsible for many of the most common skin infections. However, many...
 01:11
Papillary Dermis
The dermis might be considered the "core" of the integumentary system, as distinct from the epidermis and hypodermis. It contains blood and lymph vessels, nerves, and other structures, such as hair follicles and sweat glands. The dermis is made of two layers of connective tissue that comprise an interconnected mesh of elastin and collagenous fibers, produced by fibroblasts.
Papillary Layer
The papillary layer is made of loose, areolar connective tissue, which means the collagen and...
 01:15
Reticular Dermis
Reticular Layer
Underlying the papillary layer is the much thicker reticular layer, composed of dense, irregular connective...