Related Experiment Video
Updated: May 26, 2026
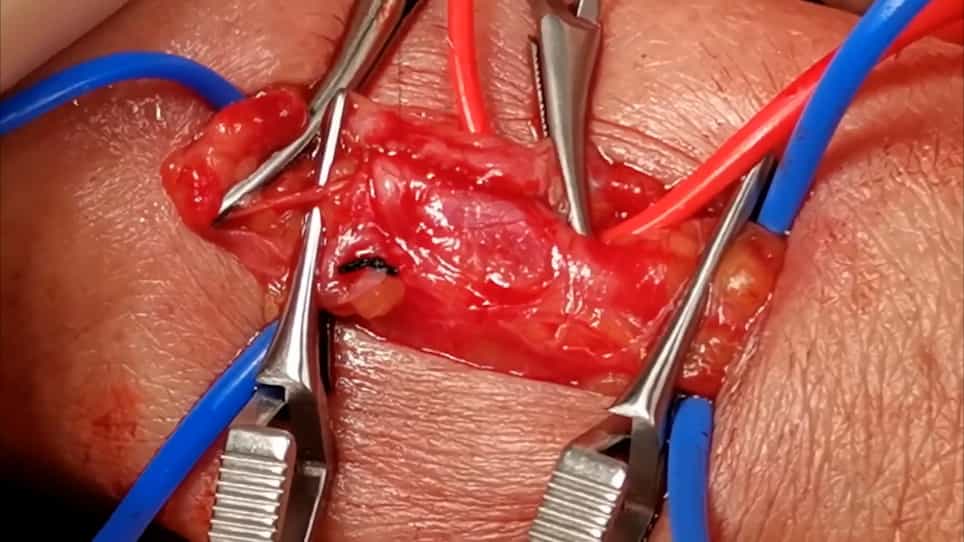

Creating Radio-cephalic Arteriovenous Fistula in the Forearm with a Modified No-Touch Technique
Published on: April 1, 2022
Vascular access considerations for therapeutic apheresis procedures
Chidi Okafor1, Kambiz Kalantarinia
1Department of Medicine, Division of Nephrology, University of Virginia Health System, Charlottesville, Virginia 22908, USA.

The success of therapeutic apheresis (TA), similar to hemodialysis, depends on the integrity of the extracorporeal circuit as well as a reliable vascular access. However, unlike hemodialysis, which requires high flow of blood around 400 mL/minute through the extracorporeal circuit for effective clearance, TA is usually carried out with much lower blood flow rates (<100 ml/minute). Therefore, even peripheral venous access can be considered for TA. The main determinants of the choice of vascular access for TA is the duration of the planned treatment and, to a certain degree, the indication for its use. While peripheral venous access and temporary central venous catheters are sufficient for short-term TA, tunnelled catheters and arteriovenous fistulae (AVF) are usually used for long-term treatments. Because of the large body of evidence in the hemodialysis literature on the advantages of AVF over tunnelled catheters and AV grafts, they should be considered as the preferred access for chronic TA as well. However, advance planning for the care of AVF after creation is of critical importance especially since many of the healthcare providers dealing with TA are less familiar with caring for AVF than nephrologists and dialysis nurses. In this article we first review the similarities and differences between HD and TA procedures. The pros and cons of different vascular access options are discussed next. Finally, we have included a list of recommendations on maintenance of AVF created for TA based on our own experience.
The success of therapeutic apheresis (TA), similar to hemodialysis, depends on the integrity of the extracorporeal circuit as well as a reliable vascular access. However, unlike hemodialysis, which requires high flow of blood around 400 mL/minute through the extracorporeal circuit for effective clearance, TA is usually carried out with much lower blood flow rates (<100 ml/minute). Therefore, even peripheral venous access can be considered for TA. The main determinants of the choice of vascular access for TA is the duration of the planned treatment and, to a certain degree, the indication for its use. While peripheral venous access and temporary central venous catheters are sufficient for short-term TA, tunnelled catheters and arteriovenous fistulae (AVF) are usually used for long-term treatments. Because of the large body of evidence in the hemodialysis literature on the advantages of AVF over tunnelled catheters and AV grafts, they should be considered as the preferred access for chronic TA as well. However, advance planning for the care of AVF after creation is of critical importance especially since many of the healthcare providers dealing with TA are less familiar with caring for AVF than nephrologists and dialysis nurses. In this article we first review the similarities and differences between HD and TA procedures. The pros and cons of different vascular access options are discussed next. Finally, we have included a list of recommendations on maintenance of AVF created for TA based on our own experience.


Related Concept Videos
 01:25
Hemodialysis I: Introduction
 01:24
Hemodialysis II: Procedure and Complications
 01:25
Extracorporeal Removal of Drugs: Hemoperfusion and Hemofiltration
 01:25
Hemodialysis III: Nursing Management
 01:26
Extracorporeal Removal of Drugs: Continuous Renal Replacement Therapy
 01:29
Venous Thrombosis III: Interprofessional Care