Related Experiment Video
Updated: May 26, 2026
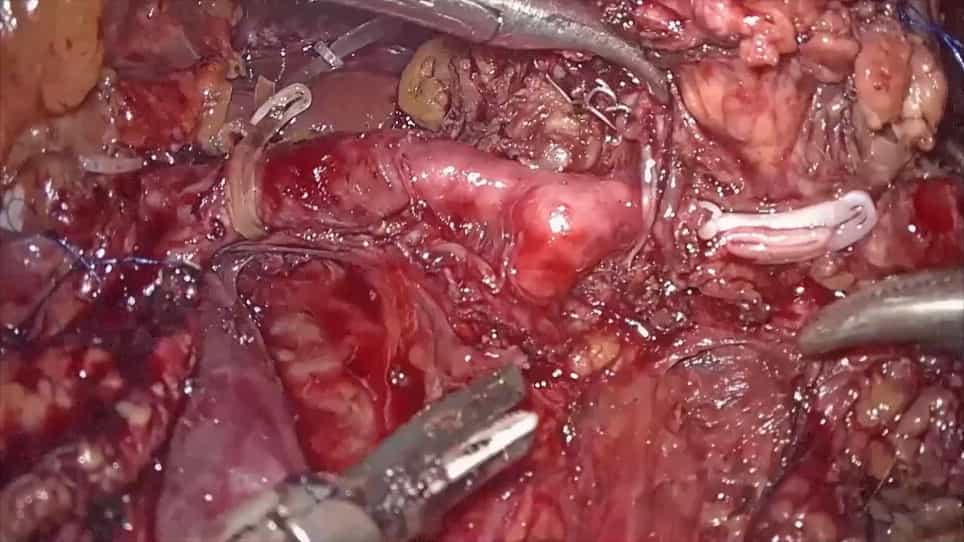

Laparoscopic Radical Antegrade Modular Pancreatosplenectomy via Dorsal-Caudal Artery Approach for Pancreatic Neck-Body Cancer
Published on: November 18, 2022
[A long-term survivor who received S-1-based multidisciplinary therapy for unresectable advanced pancreatic cancer]
Hironobu Makino1, Hisashi Kametaka, Takashi Koyama
1Dept. of Surgery, Odawara City Hospital.

Abstract:
A 62-year-old woman with a diagnosis of pancreatic cancer with splenic invasion, liver metastasis, and peritoneal dissemination was scheduled to receive chemotherapy. However, emergency surgery was performed because of an exacerbation of ileus. Laparotomy revealed moderate ascites and innumerable nodular lesions on the mesenteric side of the small intestine and colon. Peritoneal dissemination was associated with many sites of stenosis in the small intestine and colon. Surgery was performed to resect cancer of the tail of the pancreas (the primary tumor) and to permit the oral intake of food. The postoperative course was good, with no complications. On the 19th hospital day, gemcitabine was started as first-line chemotherapy. Tumor marker levels promptly decreased and remained within the normal range for 6 months. The patient received 17 courses of chemotherapy. Tumor marker levels increased subsequently, and chemotherapy was switched to S-1 as second-line treatment. Twelve courses were delivered, and tumor marker levels decreased again. Erlotinib was then added to S-1, and treatment was continued. Tumor marker levels decreased after adding erlotinib, even when there was no further response to S-1 alone. At present, the patient is receiving combined therapy with S-1 and irinotecan and has survived for 3 years and 1 month after surgery. Our findings suggest that S-1-based chemotherapy for second-line and subsequent treatment contributed to long-term survival.
Related Concept Videos
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 02:56
Treatment Resistant Cancers