Related Experiment Video
Updated: Jan 19, 2026
Cardiac Response to β-Adrenergic Stimulation Determined by Pressure-Volume Loop Analysis
Published on: May 19, 2021
A common β1-adrenergic receptor polymorphism predicts favorable response to rate-control therapy in atrial
Babar Parvez1, Nagesh Chopra, Shane Rowan
1Department of Medicine, Vanderbilt University Medical Center, Nashville, TN 37323, USA.

Objectives:
In this study, we evaluated the impact of 2 common β1-adrenergic receptor (β1-AR) polymorphisms (G389R and S49G) in response to ventricular rate control therapy in patients with atrial fibrillation (AF).
Background:
Randomized studies have shown that ventricular rate control is an acceptable treatment strategy in patients with AF. However, identification of patients who will adequately respond to rate-control therapy remains a challenge.
Methods:
We studied 543 subjects (63% men; age 61.8 ± 14 years) prospectively enrolled in the Vanderbilt AF registry and managed with rate-control strategy. A "responder" displayed adequate ventricular rate control based on the AFFIRM (Atrial Fibrillation Follow-Up Investigation of Rhythm Management) criteria: average heart rate (HR) at rest ≤80 beats/min; and maximum HR during a 6-min walk test ≤110 beats/min or average HR during 24-h Holter ≤100 beats/min.
Results:
A total of 295 (54.3%) patients met the AFFIRM criteria. Baseline clinical characteristics were similar in responders and nonresponders except for mean resting HR (76 ± 20 beats/min vs. 70 ± 15 beats/min; p < 0.01) and smoking (6% vs. 1%; p < 0.01). Multiple clinical variables (age, gender, hypertension) failed to predict response to rate-control therapy. By contrast, carriers of Gly variant at 389 were more likely to respond favorably to rate-control therapy; 60% versus 51% in the Arg389Arg genotype, p = 0.04. This association persisted after correction for multiple clinical factors (odds ratio: 1.42, 95% confidence interval: 1.00 to 2.03, p < 0.05). Among responders, subjects carrying the Gly389 variant required the lowest doses of rate-control medications; atenolol: 92 mg versus 68 mg; carvedilol: 44 mg versus 20 mg; metoprolol: 80 mg versus 72 mg; diltiazem: 212 mg versus 180 mg, and verapamil: 276 mg versus 200 mg, respectively (p < 0.01 for all comparisons).
Conclusions:
We have identified a common β1-AR polymorphism, G389R, that is associated with adequate response to rate-control therapy in AF patients. Gly389 is a loss-of-function variant; consequently, for the same adrenergic stimulation, it produces reduced levels of adenyl cyclase, and hence, attenuates the β-adrenergic cascade. Mechanistically, the effect of rate-control drugs will be synergistic with that of the Gly389 variant, which could possibly explain our findings. These findings represent a step forward in the development of a long-term strategy of selecting treatment options in AF based on genotype.

Related Concept Videos
 01:26
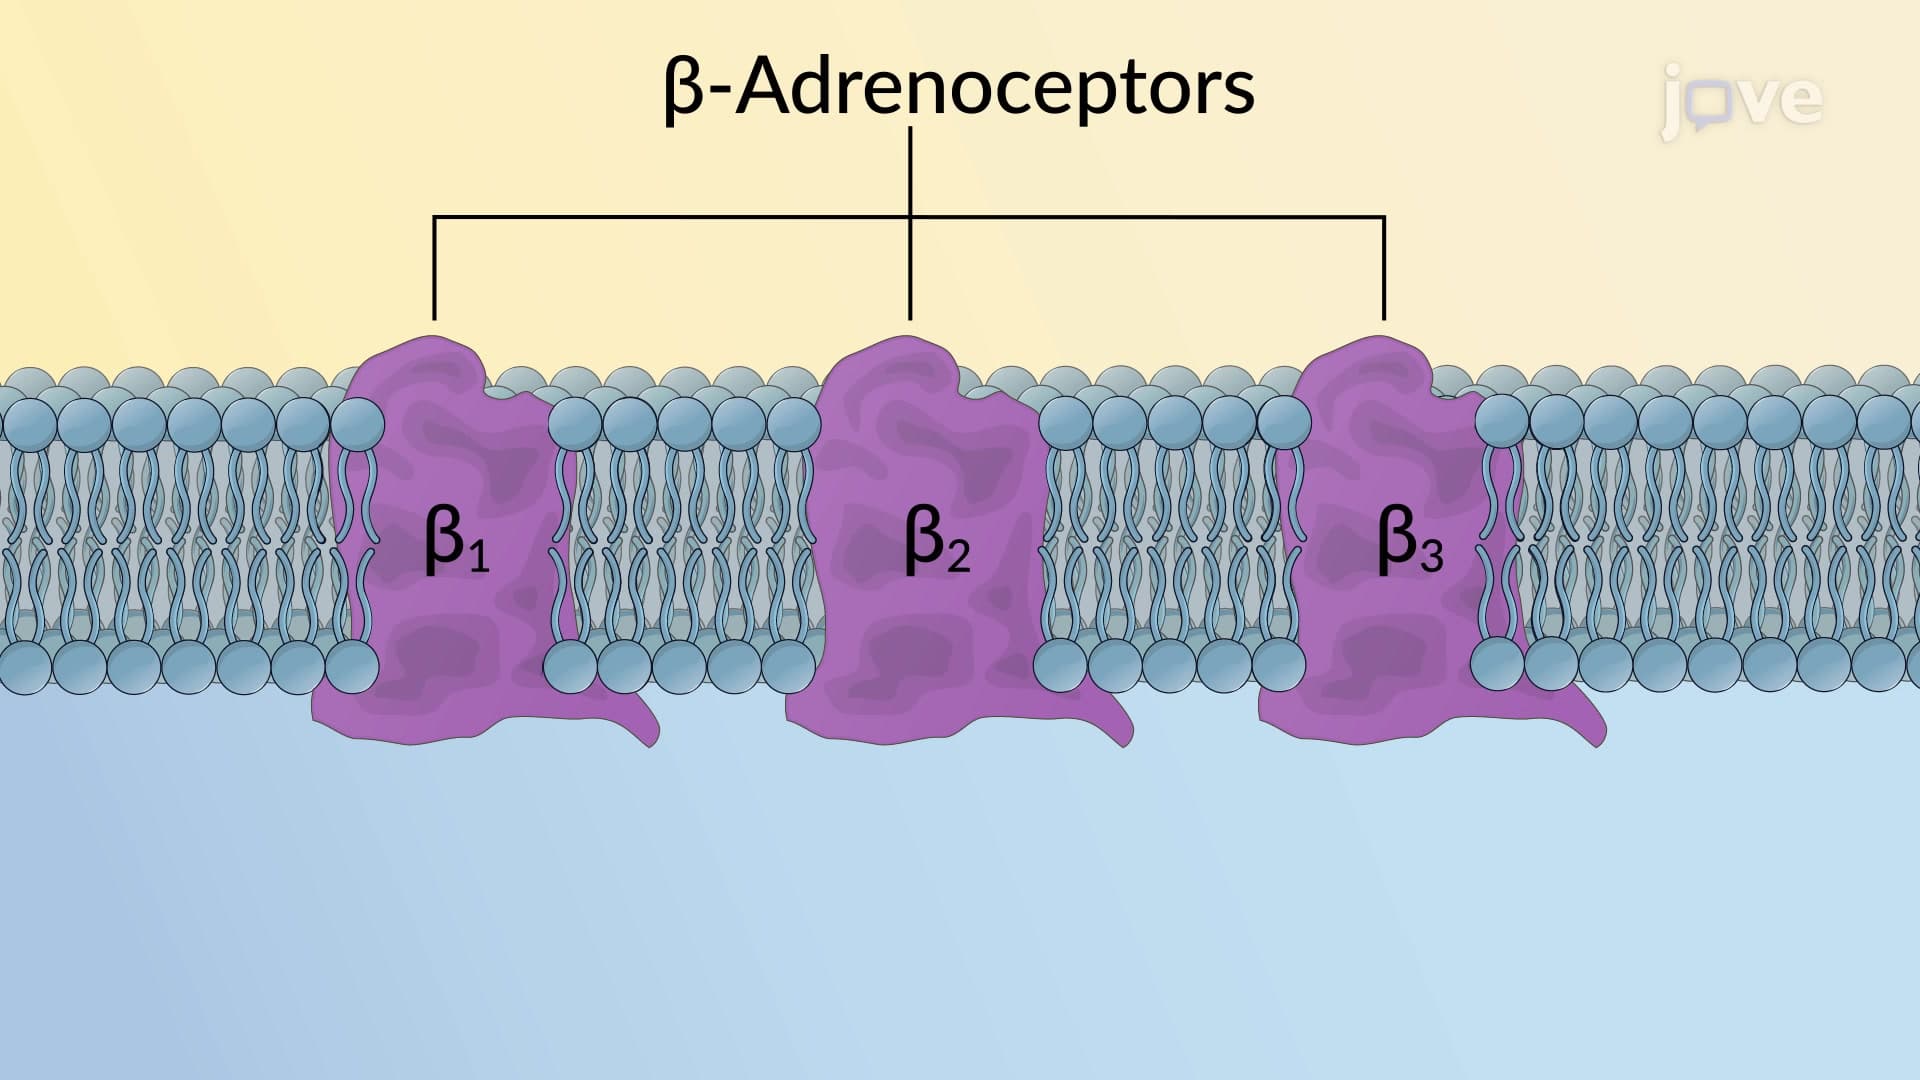
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors...
 01:25
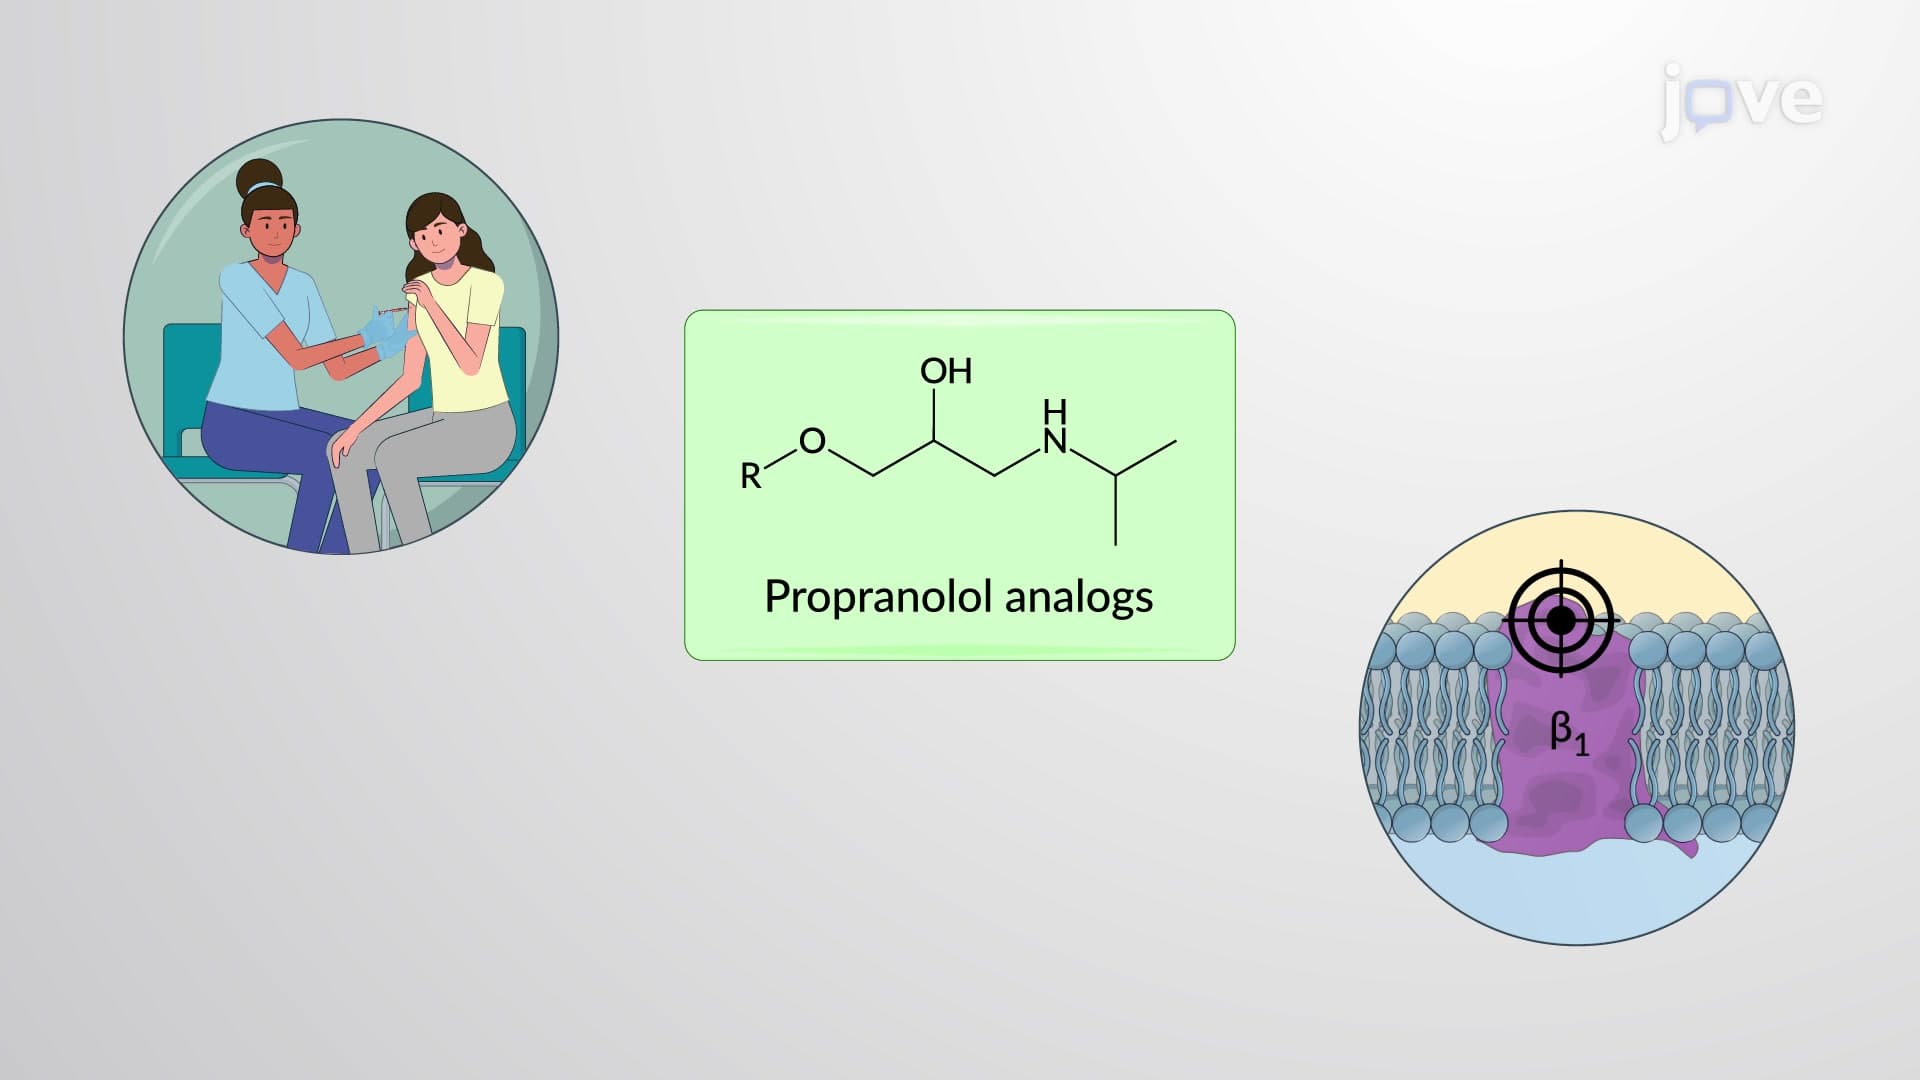
Adrenergic Antagonists: Chemistry and Classification of β-Receptor Blockers
 01:31
Adrenergic Antagonists: ɑ and β-Receptor Blockers
 01:22
Heart Failure Drugs: β-Blockers
 01:24
Antiarrhythmic Drugs: Class II Agents as β-Adrenergic Blockers
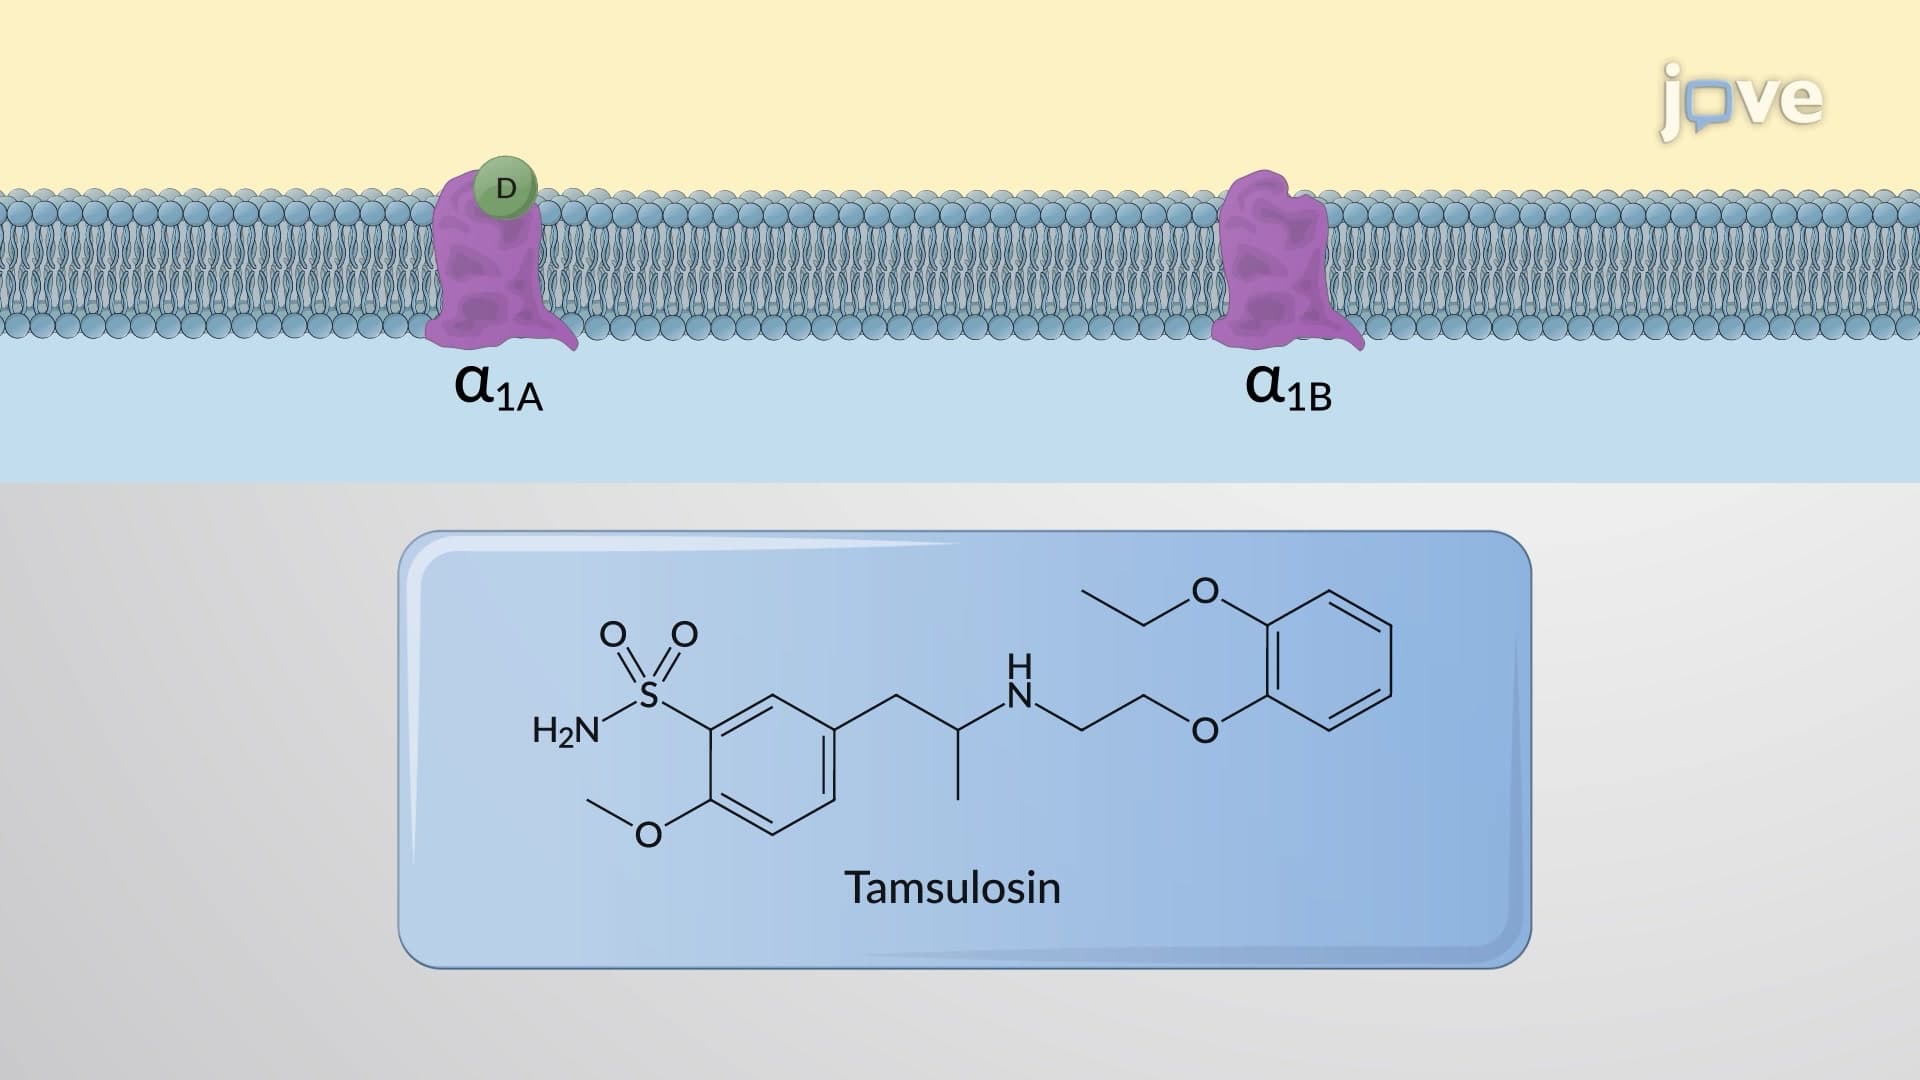 01:31
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase...