Related Experiment Video
Updated: May 26, 2026

Digital Home-Monitoring of Patients after Kidney Transplantation: The MACCS Platform
Published on: April 12, 2021
Utilization and costs of cardiovascular disease medications in dialysis patients in Medicare Part D
Diane L Frankenfield1, Eric D Weinhandl, Christopher A Powers
1Centers for Medicare & Medicaid Services, Center for Medicare and Medicaid Innovation, Baltimore, MD 21244, USA. diane.frankenfield@cms.hhs.gov

Insights
Cardiovascular disease (CVD) medication use in dialysis patients shows beta-blockers as most common. Out-of-pocket costs were higher for those without the low-income subsidy, despite similar total drug costs.
Area of Science:
- Nephrology
- Cardiology
- Health Services Research
Background:
- Cardiovascular disease (CVD) is a leading cause of death and disability among dialysis patients.
- Limited data exists on the population-level use of CVD medications in this high-risk group.
Purpose of the Study:
- To describe the utilization patterns and costs of cardiovascular disease (CVD) medications among adult dialysis patients in the United States.
- To examine variations in medication use and costs based on demographic characteristics and low-income subsidy status.
Main Methods:
- Retrospective cohort study of adult dialysis patients enrolled in Medicare Parts A, B, and D in 2007.
- Analysis of prescription fills for CVD medications and associated out-of-pocket and total costs.
- Stratification by low-income subsidy status and demographic factors.
Main Results:
- Beta-blockers were the most frequently used CVD medication (64%), followed by renin-angiotensin system inhibitors (52%) and calcium channel blockers (51%).
- Patients receiving the low-income subsidy had higher total medication costs ($124.02/month) compared to those without ($110.32/month).
- Out-of-pocket costs were substantially higher for patients without the low-income subsidy ($49.59/month) versus those with it ($3.44/month).
Conclusions:
- Most Medicare dialysis patients were enrolled in Part D, with a majority receiving the low-income subsidy.
- Significant disparities in out-of-pocket medication costs exist based on subsidy status.
- Further research is needed to understand variations in CVD medication use and costs across patient subgroups.
Background:
Cardiovascular disease (CVD) is a major source of mortality and morbidity in dialysis patients. Population-level descriptions of CVD medication use are lacking in this population.
Study Design:
Retrospective cohort study.
Setting & Participants:
Adult dialysis patients in the United States, alive on December 31, 2006, with Medicare Parts A and B and enrollment in Medicare Part D continuously in 2007.
Predictor:
CVDs and demographic characteristics.
Outcome:
≥1 prescription fill during follow-up (2007).
Measurements:
Average out-of-pocket costs per user per month and average total drug costs per member per month were calculated.
Results:
Of 225,635 dialysis patients who met inclusion criteria during the entry period, 70% (n = 158,702) had continuous Part D coverage during follow-up. Of these, 76% received the low-income subsidy. β-Blockers were the most commonly used CVD medication (64%), followed by renin-angiotensin system inhibitors (52%), calcium channel blockers (51%), lipid-lowering agents (44%), and α-agonists (23%). Use varied by demographics, geographic region, and low-income subsidy status. For CVD medications, mean out-of-pocket costs per user per month were $3.44 and $49.59 and mean total costs per member per month were $124.02 and $110.32 for patients with and without the low-income subsidy, respectively.
Limitations:
Information was available for only filled prescriptions under the Part D benefit; information for clinical contraindications was lacking, information for over-the-counter medications was unavailable, and medication adherence and persistence were not examined.
Conclusions:
Most Medicare dialysis patients in 2007 were enrolled in Part D, and most enrollees received the low-income subsidy. β-Blockers were the most used CVD medication. Total costs of CVD medications were modestly higher for low-income subsidy patients, but out-of-pocket costs were much higher for patients not receiving the subsidy. Further study is warranted to delineate sources of variation in the use and costs of CVD medications across subgroups.
Related Concept Videos
 01:28
Drug Dosing in Renal Diseases: Estimation of Glomerular Filtration Rate Based on Serum Creatinine Concentration
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:22
Heart Failure Drugs: Diuretics
 01:25
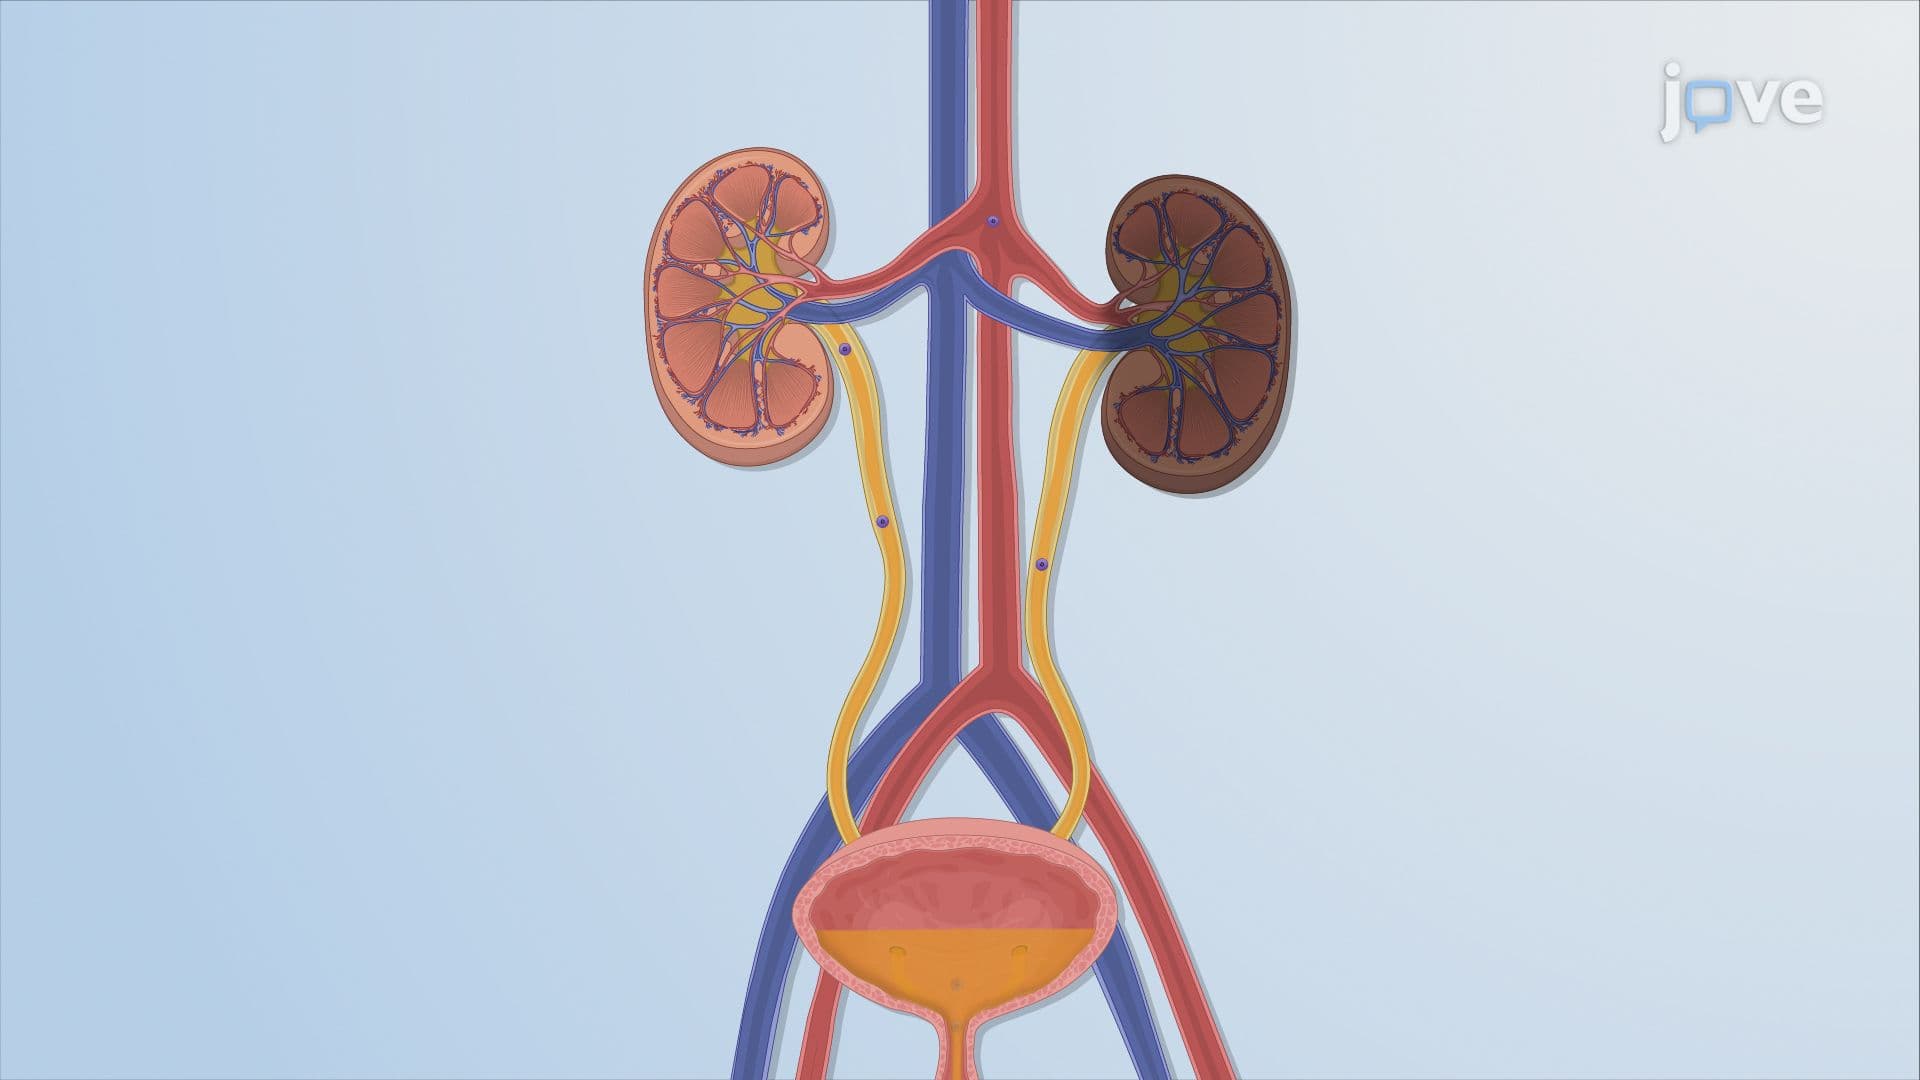
Drug Dosing in Renal Diseases: Measurement of Glomerular Filtration Rate
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:27
Dialysis
Acute kidney injury develops suddenly and can be caused by pre-renal causes (e.g., hypovolemia, shock), intrinsic renal causes (e.g., acute tubular necrosis), or post-renal causes (e.g., urinary obstruction). In contrast, chronic renal failure progresses gradually over time and is often...