Related Experiment Video
Updated: May 26, 2026
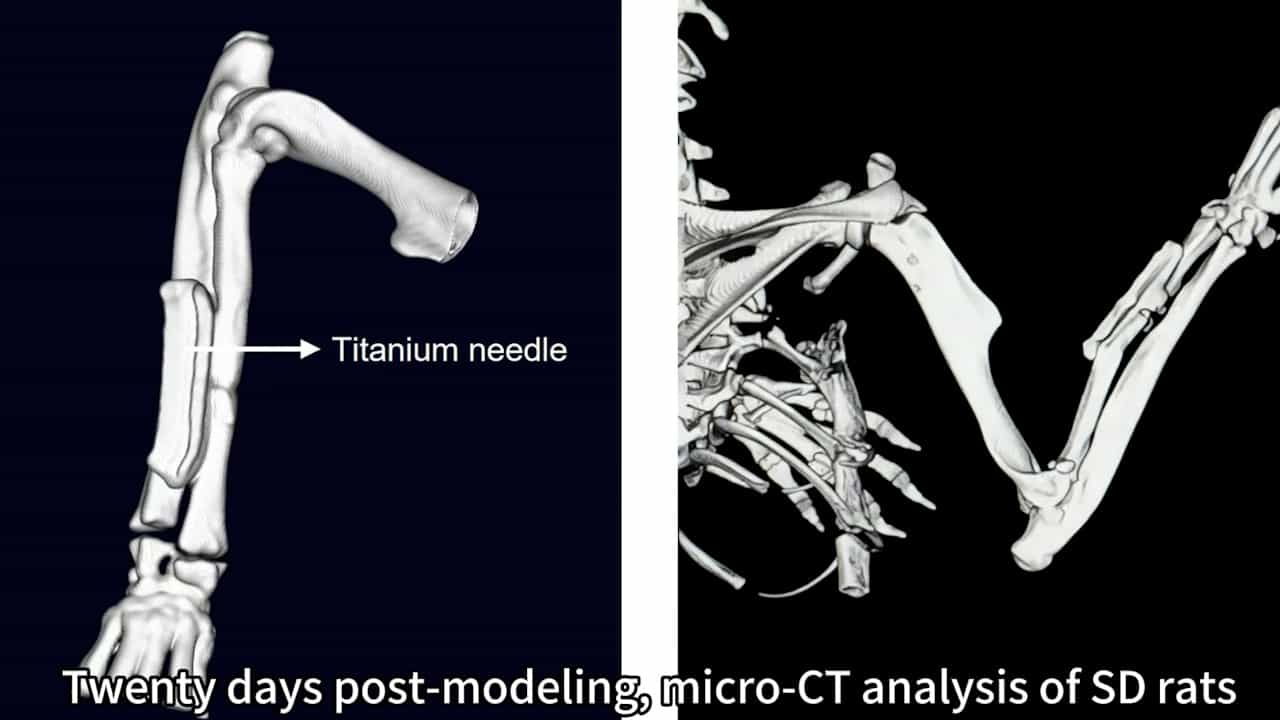

Development of a Novel Internal Fixation Model for Rat Radial Fractures: Fracture Healing Assessment and Dorsal Root Ganglion Isolation
Published on: March 13, 2026
Reconstruction of a Bryan and Morrey type I capitellar fracture in a sawbone model with four different fixation
Thomas C Koslowsky1, Christian Zilleken, Jens Dargel
1Department of Surgery, St. Elisabeth Hospital, Werthmannstrasse 1, D-50935 Cologne, Germany. tkoslowsky@web.de

Background:
We evaluated 4 different fixation devices for the reconstruction of a standardised Bryan and Morrey capitellar shear fracture in a sawbone model. Outcome measurements were the quality of reduction, time for reconstruction and stability.
Methods:
80 standardised Bryan and Morrey type I fractures were created for 5 different orthopaedic surgeons in 80 sawbones. Each surgeon reconstructed 16 fractures with 2mm K-wires, 3mm Herbert screws, 2.7 mm AO screws and 2.2mm fine-threaded wires (Fragment Fixation System: FFS). 4 fractures were allocated to each method with a standardised reconstruction procedure. Quality of reduction and time for reconstruction were measured after definitive fixation. Biomechanical testing was performed using a shear loading model with the application of monocyclic or polycyclic stress to the reconstructed capitulum.
Results:
There was no difference in the quality of reduction with the different fixation devices. Herbert and AO screw fixation was slower than the other implants (p<0.05). No difference in the time for reconstruction was observed with K-wires and FFS. Failure load was less for K-wires compared to FFS, Herbert screws and AO screws (p<0.05). With polycyclic loading, residual deformation was higher with K-wire reconstruction compared to FFS, Herbert screws and AO screws (p<0.05).
Conclusion:
When using four different fixation devices, the fixation of standardised Bryan and Morrey type I fractures in the sawbone model differs when it comes to the time needed for reduction, but not in the quality of reduction. Stability was the same for the implants used, except for the K-wires. There is no argument in favour one of the screw implants over another in clinical use.
More Related Videos
 07:35
Creating Rigidly Stabilized Fractures for Assessing Intramembranous Ossification, Distraction Osteogenesis, or Healing of Critical Sized Defects
Published on: April 11, 2012
 06:41
A Minimally Invasive Model to Analyze Endochondral Fracture Healing in Mice Under Standardized Biomechanical Conditions
Published on: March 22, 2018
