Related Experiment Video
Updated: May 25, 2026
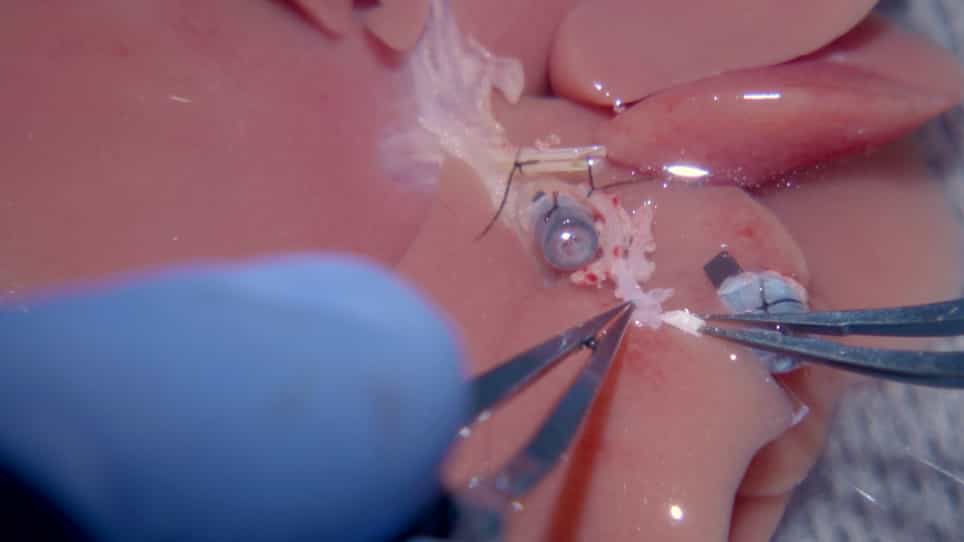

Reduced Complications after Arterial Reconnection in a Rat Model of Orthotopic Liver Transplantation
Published on: November 7, 2020
Gout and organ transplantation
Lisa K Stamp1, Peter T Chapman
1Department of Medicine, University of Otago, Christchurch, P.O. Box 4345, Christchurch, 8140, New Zealand. lisa.stamp@cdhb.govt.nz

Acute and chronic gout are common complications following organ transplantation. Risk factors include those shared with the general population (eg, diuretic use) and transplant-specific risk factors (eg, cyclosporine). Clinical features of gout are similar to those seen in the general population, although tophi may be more common. A definitive diagnosis requires demonstration of monosodium urate crystals within synovial fluid or tophi. Treatment is often empiric, although a poor response should prompt joint aspiration to exclude septic arthritis. Corticosteroids are commonly used to treat acute gout due to the adverse profile and drug interactions with NSAIDs and colchicine. Sustained reduction of serum urate (≤6 mg/dL) is critical in long-term management. Allopurinol is the most commonly used agent, although vigilant monitoring is required if combined with azathioprine. Other options include febuxostat and benzbromarone. The role of newer agents such as interleukin-1 inhibitors and uricases remains to be determined. General measures should include minimizing diuretic use.
Acute and chronic gout are common complications following organ transplantation. Risk factors include those shared with the general population (eg, diuretic use) and transplant-specific risk factors (eg, cyclosporine). Clinical features of gout are similar to those seen in the general population, although tophi may be more common. A definitive diagnosis requires demonstration of monosodium urate crystals within synovial fluid or tophi. Treatment is often empiric, although a poor response should prompt joint aspiration to exclude septic arthritis. Corticosteroids are commonly used to treat acute gout due to the adverse profile and drug interactions with NSAIDs and colchicine. Sustained reduction of serum urate (≤6 mg/dL) is critical in long-term management. Allopurinol is the most commonly used agent, although vigilant monitoring is required if combined with azathioprine. Other options include febuxostat and benzbromarone. The role of newer agents such as interleukin-1 inhibitors and uricases remains to be determined. General measures should include minimizing diuretic use.

Related Concept Videos
 01:28
Kidney Transplant I: Introduction
 01:24
Tissue Transplantation
The Biology of Tissue Transplantation
The biology of tissue transplantation hinges on the Major Histocompatibility Complex (MHC) molecules. These molecules...
 01:26
Kidney Transplant II: Surgical Procedure
 01:16
Kidney Transplant III: Nursing Management
 01:22
Bone Marrow Sampling and Transplants
The transplant begins with high doses of chemotherapy and radiation treatment, which aim to destroy the...