Related Experiment Video
Updated: May 25, 2026
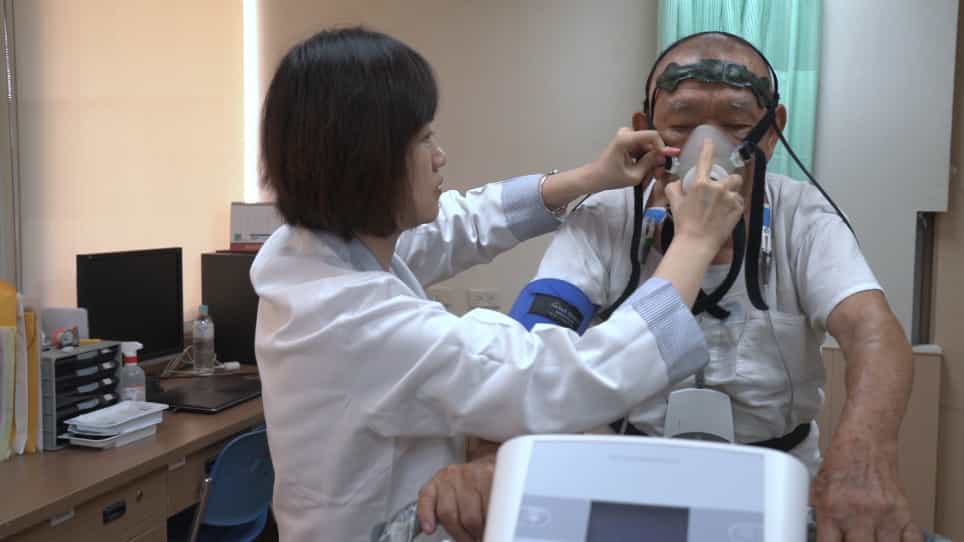
Integration of Brain Tissue Saturation Monitoring in Cardiopulmonary Exercise Testing in Patients with Heart Failure
Published on: October 1, 2019
Elevated Levels of N-Terminal Pro-Brain Natriuretic Peptide in Patients with Chronic Dyspnea and Moderate Renal

Background/Aims:
Serum levels of N-terminal pro-brain natriuretic peptide (NT-proBNP) are often increased in patients with impaired renal function. The objective of this study was to investigate whether the increase in NT-proBNP is predominantly due to a reduced renal clearance or an increased cardiac secretion.
Methods:
A series of 697 outpatients (age: 57.5 ± 16.4 years) referred for evaluation of dyspnea were assigned to 4 groups according to their estimated glomerular filtration rate [eGFR (ml/min per 1.73 m2)]: group 1, eGFR <60 (n = 77); group 2, eGFR ≧60 to <75 (n = 139); group 3, eGFR ≧75 to <90 (n = 191), and group 4, eGFR ≧90 (n = 289). The patients were also grouped into 2 categories based on the presence (n = 176) or absence (n = 521) of heart disease.
Results:
In patients with heart disease, the adjusted values for NT-proBNP were higher in eGFR group 1 than in eGFR groups 2-4 (p ≤ 0.01). In patients without heart disease, eGFR group 1 membership had no effect on NT-proBNP.
Conclusion:
A reduced renal clearance does not explain increased NT-proBNP levels in patients with moderate renal impairment and dyspnea. Our data suggest that a moderate reduction in renal function places additional stress on the heart in patients with established cardiac disease.
Related Concept Videos
 01:29
Heart Failure II: Pathophysiology
 01:19
Blood Studies for Cardiovascular System II: CRP, Hcy, and Cardiac Natriuretic Peptide Markers
These markers indicate stress or strain on the heart muscle:
Natriuretic Peptides (BNP)
Cardiac myocytes produce these hormones in response to ventricular stretching...
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System
 01:22
Heart Failure Drugs: Diuretics
 01:18
Chronic Kidney Disease IV: Nursing Management
 01:29
Hypertension II: Pathophysiology