Related Experiment Video
Updated: May 24, 2026


Signal Acquisition, Score Interpretation, and Economics of a Non-Invasive Point-of-Care Test for Coronary Artery Disease
Published on: August 9, 2024
Physician discretion is safe and may lower stress test utilization in emergency department chest pain unit patients
Anthony M Napoli1, James A Arrighi, Matthew S Siket
1Department of Emergency Medicine, Warren Alpert Medical School of Brown University, Rhode Island Hospital, Providence, RI 02903, USA. anapoli@lifespan.org

Introduction:
Chest pain unit (CPU) observation with defined stress utilization protocols is a common management option for low-risk emergency department patients. We sought to evaluate the safety of a joint emergency medicine and cardiology staffed CPU.
Methods:
Prospective observational trial of consecutive patients admitted to an emergency department CPU was conducted. A standard 6-hour observation protocol was followed by cardiology consultation and stress utilization largely at their discretion. Included patients were at low/intermediate risk by the American Heart Association, had nondiagnostic electrocardiograms, and a normal initial troponin. Excluded patients were those with an acute comorbidity, age >75, and a history of coronary artery disease, or had a coexistent problem restricting 24-hour observation. Primary outcome was 30-day major adverse cardiovascular events-defined as death, nonfatal acute myocardial infarction, revascularization, or out-of-hospital cardiac arrest.
Results:
A total of 1063 patients were enrolled over 8 months. The mean age of the patients was 52.8 ± 11.8 years, and 51% (95% confidence interval [CI], 48-54) were female. The mean thrombolysis in myocardial infarction and Diamond & Forrester scores were 0.6% (95% CI, 0.51-0.62) and 33% (95% CI, 31-35), respectively. In all, 51% (95% CI, 48-54) received stress testing (52% nuclear stress, 39% stress echocardiogram, 5% exercise, 4% other). In all, 0.9% patients (n = 10, 95% CI, 0.4-1.5) were diagnosed with a non-ST elevation myocardial infarction and 2.2% (n = 23, 95% CI, 1.3-3) with acute coronary syndrome. There was 1 (95% CI, 0%-0.3%) case of a 30-day major adverse cardiovascular events. The 51% stress test utilization rate was less than the range reported in previous CPU studies (P < 0.05).
Conclusions:
Joint emergency medicine and cardiology management of patients within a CPU protocol is safe, efficacious, and may safely reduce stress testing rates.


Related Concept Videos
 01:26
Exercise Stress Test
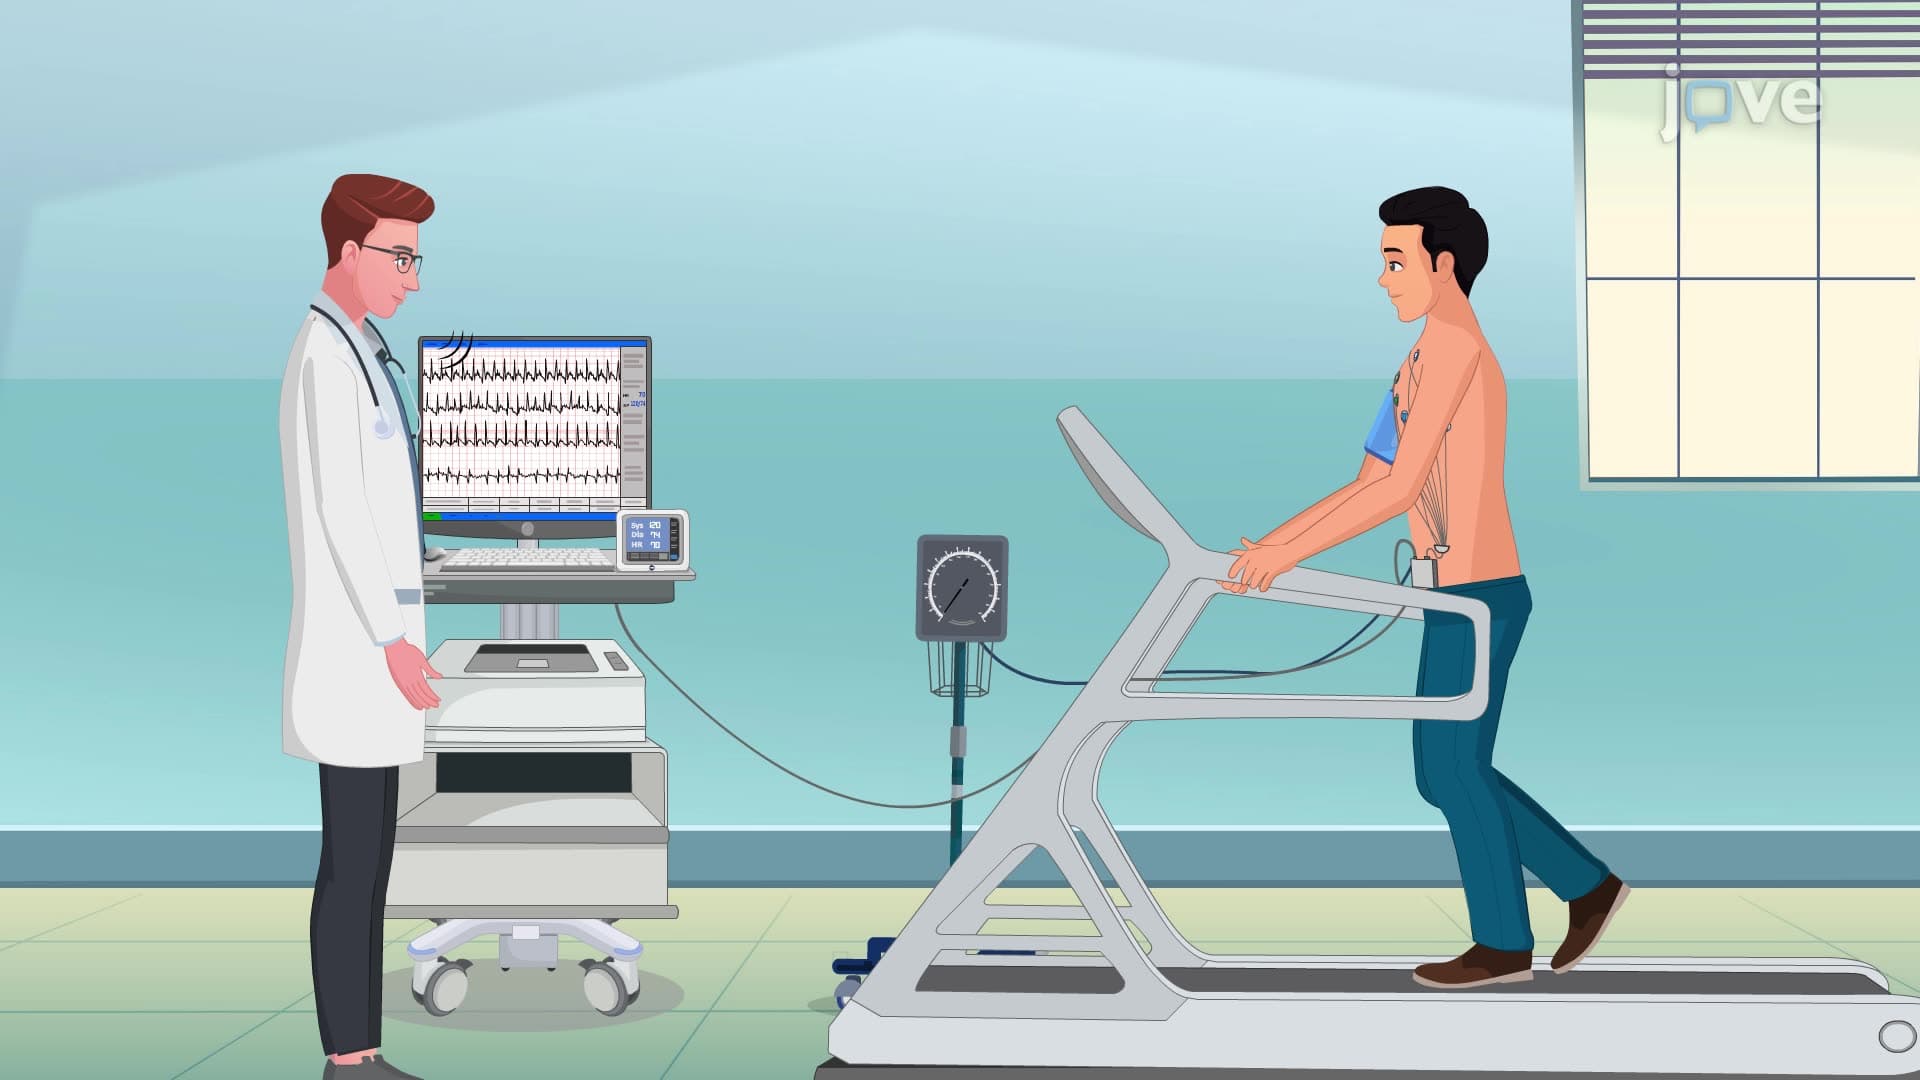
Exercise stress testing, commonly known as a treadmill test, is a noninvasive procedure used to evaluate cardiovascular function and diagnose heart conditions.
Definition
An exercise stress test measures the heart's response to exertion using a treadmill or stationary bicycle. Chest electrodes record the heart's electrical activity through an ECG, and blood pressure is monitored regularly.
Purposes
 01:29
Angina III: Clinical Manifestations and Assessment
 01:20
Angina V: Nursing Management
 01:10
Pre-Procedural Guidelines for Assessing Blood Pressure
 01:28
Imaging Studies for Cardiovascular System V: CT
 01:26
Cardiac Catheterization IV: Nursing Management