Related Experiment Video
Updated: May 24, 2026
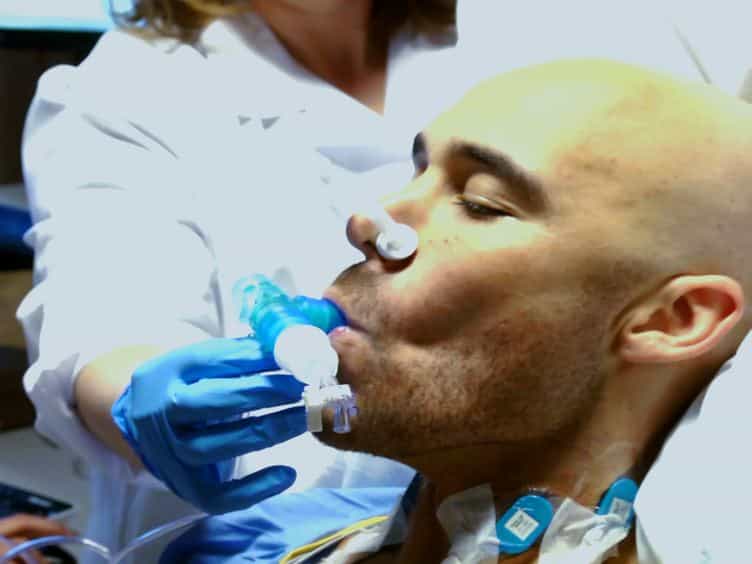

Evaluation of Respiratory Muscle Activation Using Respiratory Motor Control Assessment (RMCA) in Individuals with Chronic Spinal Cord Injury
Published on: July 19, 2013
Assessment of pulmonary restriction in cervical spinal cord injury: a preliminary report
Christopher R West1, Ian G Campbell, Lee M Romer
1Centre for Sports Medicine and Human Performance, Brunel University, Uxbridge, UK.

Objective:
To compare the prevalence of pulmonary restriction on the basis of a vital capacity (VC) below the lower limit of normal (LLN) and a normal or high forced expiratory volume in 1 second (FEV(1))/VC ratio with the criterion standard of total lung capacity (TLC) less than LLN in individuals with spinal cord injury (SCI) and able-bodied (AB) controls.
Design:
Method comparison with criterion standard.
Setting:
University research center.
Participants:
Individuals with cervical SCI (n=12; injury level, C5-7) and AB controls (n=12) matched for age, stature, and body mass.
Interventions:
None.
Main Outcome Measures:
TLC via plethysmography; FEV(1) and VC via spirometry; and maximum inspiratory and expiratory pressures (P(Imax) and P(Emax)).
Results:
All participants with SCI exhibited a VC less than LLN and a normal-to-high FEV(1)/VC ratio, whereas significantly fewer (8 of 12) participants with SCI exhibited a TLC less than LLN (P=.046). For the AB group, no participant exhibited a VC or TLC less than LLN. Percent-predicted VC was lower than the percent-predicted TLC in SCI (P=.013), whereas percent-predicted VC was higher than percent-predicted TLC in AB controls (P=.001). Percent-predicted P(Imax) was higher than P(Emax) in SCI (P=.001) but not AB controls (P=.146).
Conclusions:
A VC less than LLN with a normal-to-high FEV(1)/VC ratio does not accurately predict pulmonary restriction in cervical SCI. When using spirometry to infer pulmonary restriction in cervical SCI, we recommend using a VC below 60% of the AB predicted value.