Middle lobe syndrome: a review of clinicopathological features, diagnosis and treatment
Related Experiment Video
Updated: May 24, 2026
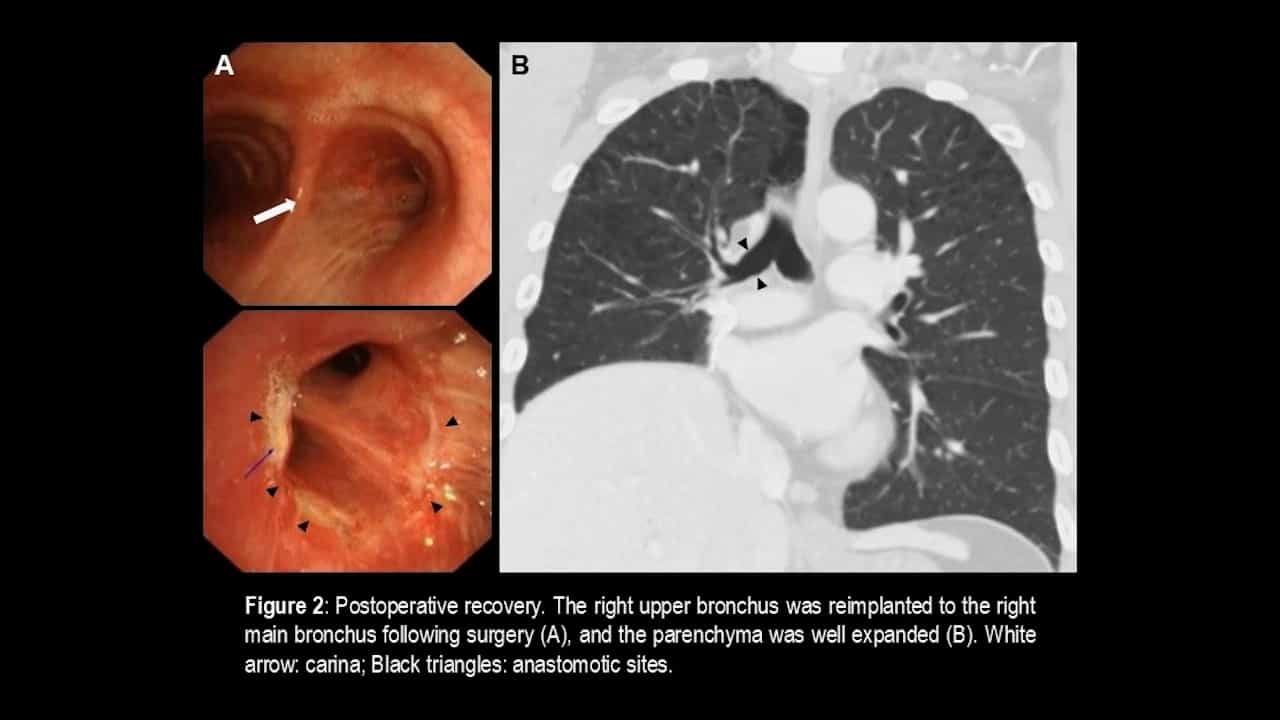
Thoracoscopic Extended Right Middle Plus Lower Sleeve Lobectomy for Non-Small-Cell Lung Cancer
Published on: February 27, 2026
Tomas Gudbjartsson1, Gunnar Gudmundsson
1Department of Cardiothoracic Surgery, Landspitali - The National University Hospital of Iceland, Reykjavik, Iceland. tomasgud@landspitali.is

Abstract:
Middle lobe syndrome (MLS) is a rare but important clinical entity that has been poorly defined in the literature. It is characterized by recurrent or chronic collapse of the middle lobe of the right lung but can also involve the lingula of the left lung. Pathophysiologically, there are two forms of MLS, namely obstructive and nonobstructive. Obstructive MLS is usually caused by endobronchial lesions or extrinsic compression of the middle lobe bronchus such as from hilar lymphadenopathy or tumors of neoplastic origin, resulting in postobstructive atelectasis and pneumonitis. In the nonobstructive type, no obstruction of the middle lobe bronchus is evident during bronchoscopy or with computerized tomography of the chest. The etiology of the nonobstructive form is not completely understood. Inefficient collateral ventilation, infection and inflammation in the middle lobe or lingula are thought to play a role, and bronchiectasis is the most common histological finding. Patients with proven endobronchial lesions or malignancy are usually offered surgical resection directly. This contrasts with nonobstructive MLS, where most patients respond to medical treatment consisting of bronchodilators, mucolytics and broad-spectrum antibiotics. However, some patients do not respond to conservative treatment and may suffer irreversible damage of the middle lobe or lingula, in addition to having recurrent symptoms of infection or inflammation. These selected patients can be offered surgical resection of the middle lobe or lingula, which is associated with a low mortality rate and favorable outcome.
Related Concept Videos
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...
 01:23
Mitral Stenosis II: Clinical features and Diagnostic Tests
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features
 01:19
Chronic Obstructive Pulmonary Disease IV: Clinical Manifestations
 01:28
Pleural Effusion II: Symptoms and Management
A pleural effusion is the abnormal collection of fluid between the parietal and visceral pleura layers of tissue that form the lining of the lungs and chest cavity. It can occur independently or due to surrounding parenchymal diseases, such as infection, malignancy, or inflammatory conditions.
Clinical Manifestations:
 01:25
Chronic Obstructive Pulmonary Disease-III: Symptoms and Complications.
Symptoms of COPD can be classified as primary or systemic. Primary symptoms relate to reduced airflow, while systemic or extrapulmonary symptoms relate to COPD's broader impact on the body.
Primary Symptoms of COPD: