Related Experiment Video
Updated: May 23, 2026
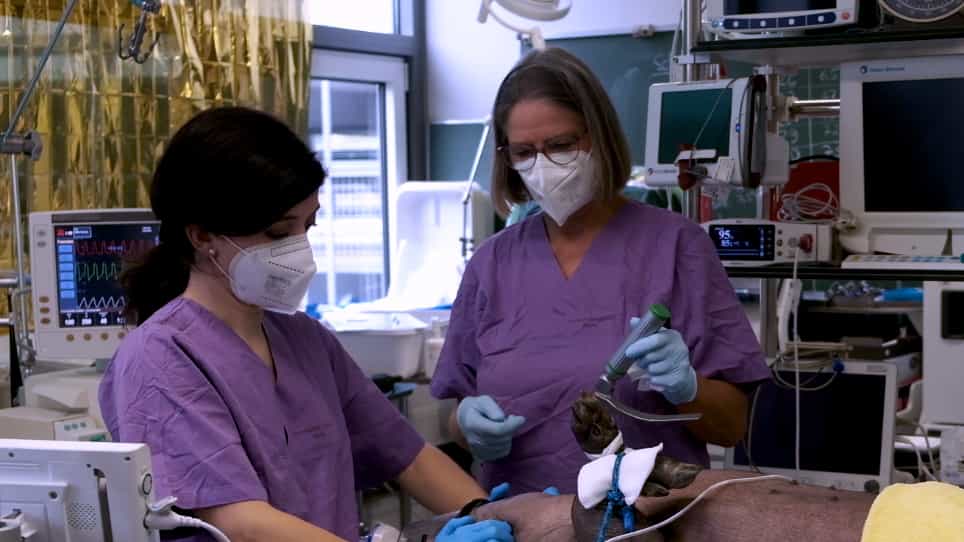

Endotracheal Intubation Using a Flexible Intubation Endoscope as a Standardized Model for Safe Airway Management in Swine
Published on: August 25, 2022
Outcomes of intubation in difficult airways due to head and neck pathology
Tim A Iseli1, Claire E Iseli, J Blake Golden
1Department of Surgery, Melbourne University, Parkville, Victoria, Australia.

Abstract:
The purpose of this study was to examine the impact of surgical pathology, anesthesiologist experience, and airway technique on surgically relevant outcomes in patients identified by preoperative laryngoscopy to have a difficult airway due to head and neck pathology. We prospectively recorded a series of 152 difficult airway cases due to head and neck pathology out of 2,145 direct laryngoscopies undertaken between November 2005 and June 2008. One of two senior anesthesiologists specializing in head and neck procedures intubated 101 (66.4%) of the 152 patients and did so 3.3 minutes faster (p = 0.51), with better oxygenation (87.3 vs. 81.8%; p = 0.02) and fewer airway plan changes (p = 0.001) than did other, nonspecialist anesthesiologists. Predictors of failure of the first intubation plan included: cancer diagnosis (p = 0.02), previous radiotherapy (p = 0.03), and supraglottic lesions (p = 0.03). Glottic/subglottic lesions required the most intubation attempts (p = 0.02). Awake fiberoptic intubation was the most common method used (44.7%) but resulted in a change in the airway plan in 6 cases (8.8%). Gas induction maintained the best oxygenation (p = 0.01). Awake tracheostomy was infrequent (1.3%) and took the longest (p = 0.006). We concluded that difficult airways due to head and neck pathology require teamwork and a backup plan. An anesthesiologist specializing in head and neck procedures may help to avoid adverse outcomes associated with cancer, especially previously irradiated supraglottic/glottic lesions, leading to a less frequent need for awake tracheostomy.


Related Concept Videos
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:15
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:17
Endotracheal Intubation II: Nursing Management
1. Nursing Care of Patients Before Intubation
Before the endotracheal intubation procedure, nurses play an essential role in ensuring the process goes smoothly. The nurses must be familiar with intubation...
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals.
 01:22
Trachea
Anatomical Features:
Location: About half of the trachea is situated in the neck, anterior to the esophagus, and extends from the larynx (at the level of the...
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management