Related Experiment Video
Updated: May 23, 2026


Modeling and Evaluation of Murine Diabetic Cardiomyopathy Model
Published on: November 29, 2024
Left ventricular hypertrophy and geometry in type 2 diabetes patients with chronic kidney disease. An
M P Bayauli1, F B Lepira, P K Kayembe
1Department of Internal Medicine, Division of Endocrinology, University of Kinshasa Hospital, Democratic Republic of the Congo (DRC).

Objective:
We assessed left ventricular structural alterations associated with chronic kidney disease (CKD) in Congolese patients with type 2 diabetes.
Methods:
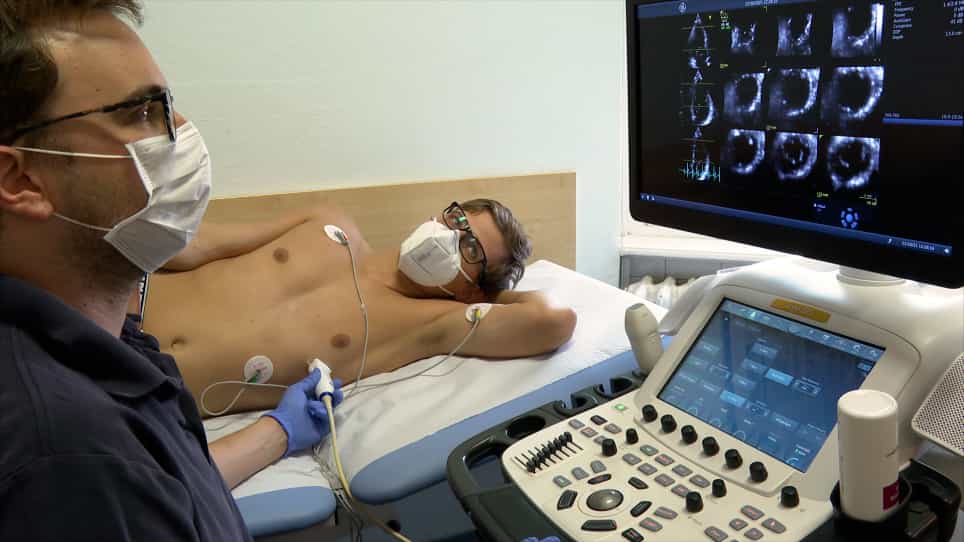
This was a cross-sectional study of a case series. We obtained anthropometric, clinical, biological and echocardiographic measurements in 60 consecutive type 2 diabetes patients (37 females, 62% ) aged 20 years or older from the diabetes outpatient clinic, University of Kinshasa Hospital, DRC. We computed creatinine clearance rate according to the MDRD equation and categorised patients into mild (CrCl > 60 ml/min per 1.73 m(2)), moderate (CrCl 30-60 ml/min per 1.73 m(2)) and severe CKD (< 30 ml/min per 1.73 m(2)). Left ventricular hypertrophy (LVH) was indicated by a LV mass index (LVMI) > 51 g/m(2.7) and LV geometry was defined as normal, or with concentric remodelling, eccentric or concentric hypertrophy, using relative wall thickness (RWT) and LVMI.
Results:
Compared to patients with normal kidney function, CKD patients had higher uric acid levels (450 ± 166 vs 306 ± 107 µmol/l; p ≤ 0.001), a greater proportion of LVH (37 vs 14%; p ≤ 0.05) and longstanding diabetes (13 ± 8 vs 8 ± 6 years; p ≤ 0.001). Their left ventricular internal diameter, diastolic (LVIDD) was (47.00 ± 6.00 vs 43.00 ± 7.00 mm; p ≤ 0.001), LVMI was (47 ± 19 vs 36.00 ± 15 g/m2.7; p ≤ 0.05) and proportions of concentric (22 vs 11%; p ≤ 0.05) or eccentric (15 vs 3%; p ≤ 0.05) LVH were also greater. Severe CKD was associated with increased interventricular septum, diastolic (IVSD) (12.30 ± 3.08 vs 9.45 ± 1.94 mm; p ≤ 0.05), posterior wall thickness, diastolic (PWTD) (11.61 ± 2.78 vs 9.52 ± 1.77 mm; p ≤ 0.01), relative wall thickness (RWT) (0.52 ± 0.17 vs 0.40 ± 0.07; p ≤ 0.01) rate of LVH (50 vs 30%; p ≤ 0.05), and elevated proportions of concentric remodelling (25 vs 15%; p ≤ 0.05) and concentric LVH (42 vs 10%; p ≤ 0.05) in comparison with patients with moderate CKD. In multivariable adjusted analysis, hyperuricaemia emerged as the only predictor of the presence of LVH in patients with CKD (adjusted OR 9.10; 95% CI: 2.40-33.73).
Conclusion:
In keeping with a higher rate of cardiovascular events usually reported in patients with impaired renal function, CKD patients exhibited LVH and abnormal LV geometry.

Related Concept Videos
 01:29
Heart Failure II: Pathophysiology
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy
 01:20
Imaging Studies for Cardiovascular System II:Types of Echocardiography
Types of Echocardiography
Transthoracic Echocardiography (TTE)
TTE is the most common type of echocardiogram which involves placing a transducer on the patient's chest, emitting sound waves to create heart images. TTE is invaluable for evaluating the heart's size, structure, and motion, making it particularly useful for diagnosing...
 01:20
Mitral Regurgitation I: Introduction
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests