Related Experiment Video
Updated: May 23, 2026


Mouse Model of Acute to Chronic Kidney Disease Transition Induced by Renal Ischemia/Reperfusion Injury
Published on: February 10, 2026
Toward the optimal dose metric in continuous renal replacement therapy
Rolando Claure-Del Granado1, Etienne Macedo, Glenn M Chertow
1University of California San Diego, San Diego, California - USA.

Purpose:
There is no consensus on the optimal method to measure delivered dialysis dose in patients with acute kidney injury (AKI). The use of direct dialysate-side quantification of dose in preference to the use of formal blood-based urea kinetic modeling and simplified blood urea nitrogen (BUN) methods has been recommended for dose assessment in critically-ill patients with AKI. We evaluate six different blood-side and dialysate-side methods for dose quantification.
Methods:
We examined data from 52 critically-ill patients with AKI requiring dialysis. All patients were treated with pre-dilution CVVHDF and regional citrate anticoagulation. Delivered dose was calculated using blood-side and dialysis-side kinetics. Filter function was assessed during the entire course of therapy by calculating BUN to dialysis fluid urea nitrogen (FUN) ratios q/12 hours.
Results:
Median daily treatment time was 1,413 min (1,260-1,440). The median observed effluent volume per treatment was 2,355 mL/h (2,060-2,863) (p<0.001). Urea mass removal rate was 13.0 ± 7.6 mg/min. Both EKR (r²=0.250; p<0.001) and KD (r²=0.409; p<0.001) showed a good correlation with actual solute removal. EKR and KD presented a decline in their values that was related to the decrease in filter function assessed by the FUN/BUN ratio.
Conclusions:
Effluent rate (mL/kg/h) can only empirically provide an estimated of dose in CRRT. For clinical practice, we recommend that the delivered dose should be measured and expressed as KD. EKR also constitutes a good method for dose comparisons over time and across modalities.

Related Concept Videos
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:30
Continuous Renal Replacement Therapy
 01:24
Rational Dosage Regimen: Maintenance Dose and Loading Dose
In most cases, drugs are administered repetitively or infused continuously to maintain a steady-state concentration in the body. At a steady state,...
 01:15
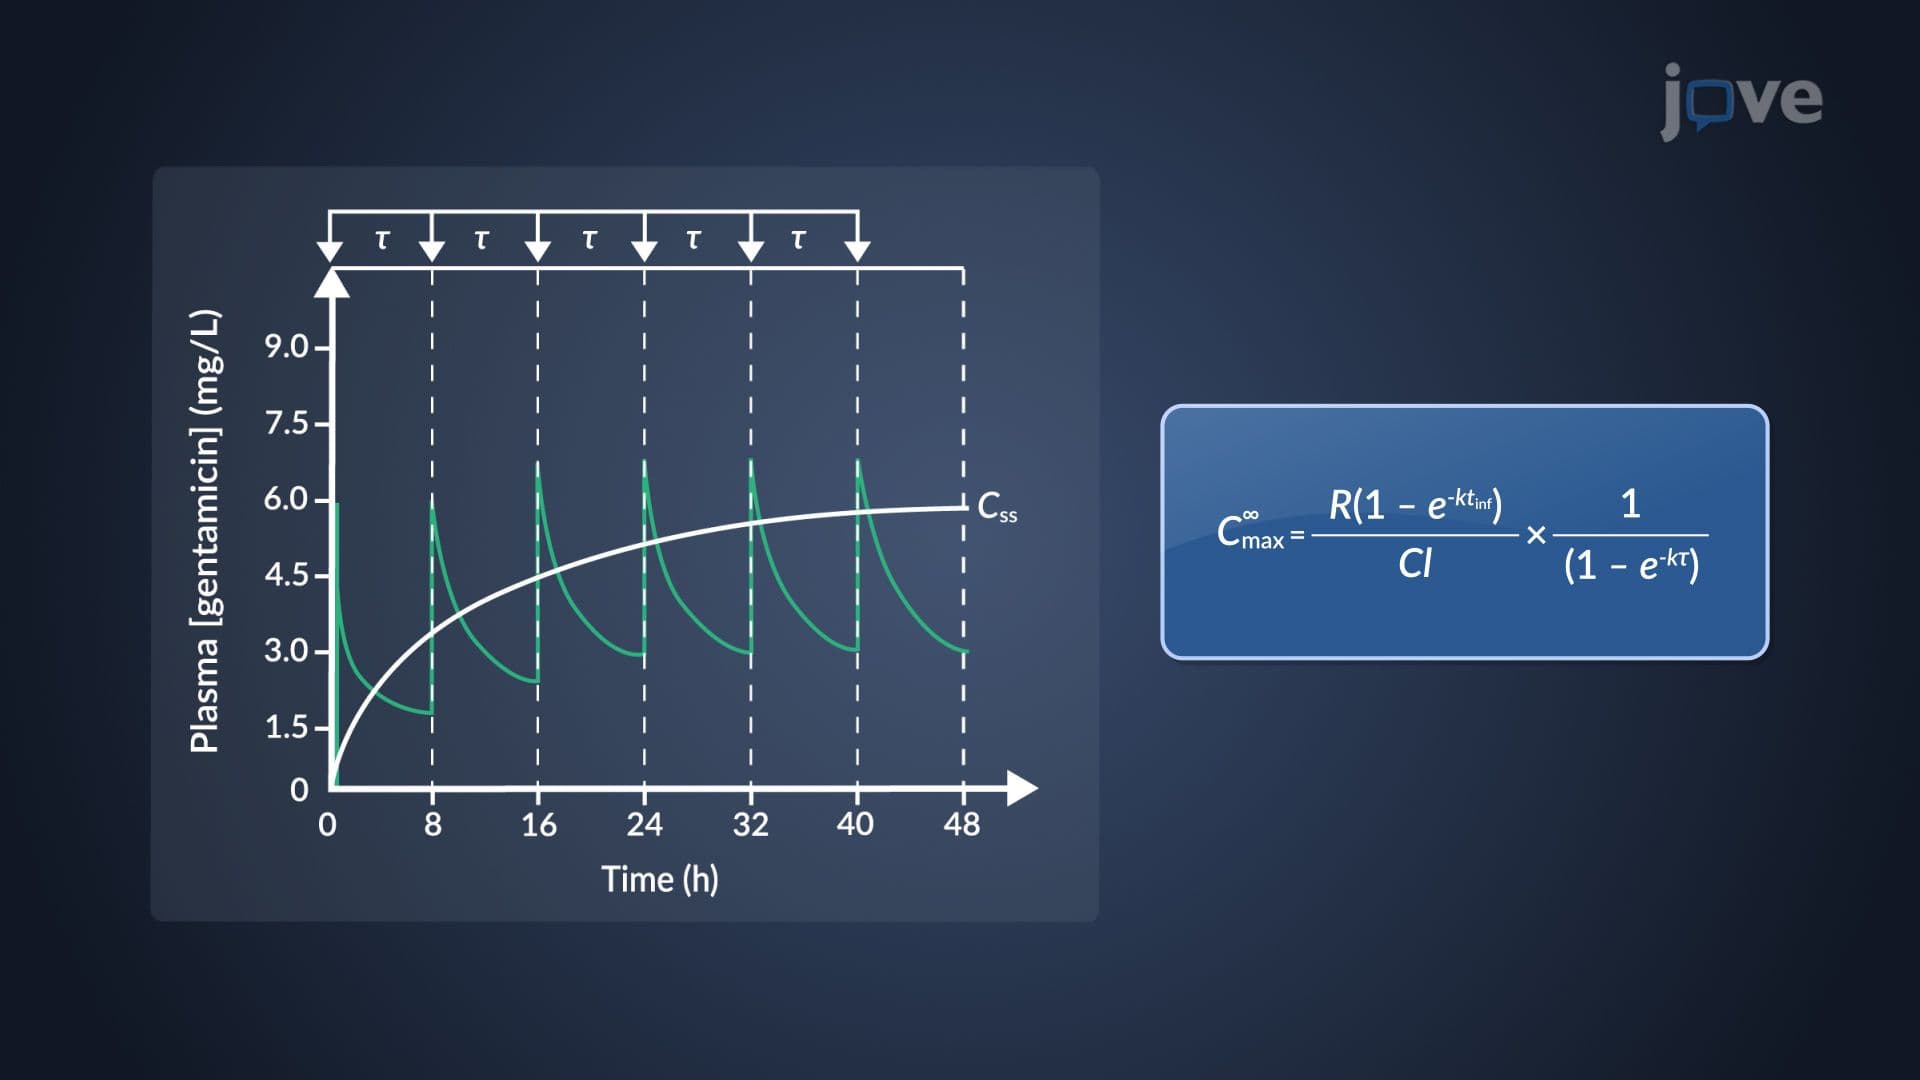
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:26
Extracorporeal Removal of Drugs: Continuous Renal Replacement Therapy