Related Experiment Video
Updated: May 23, 2026
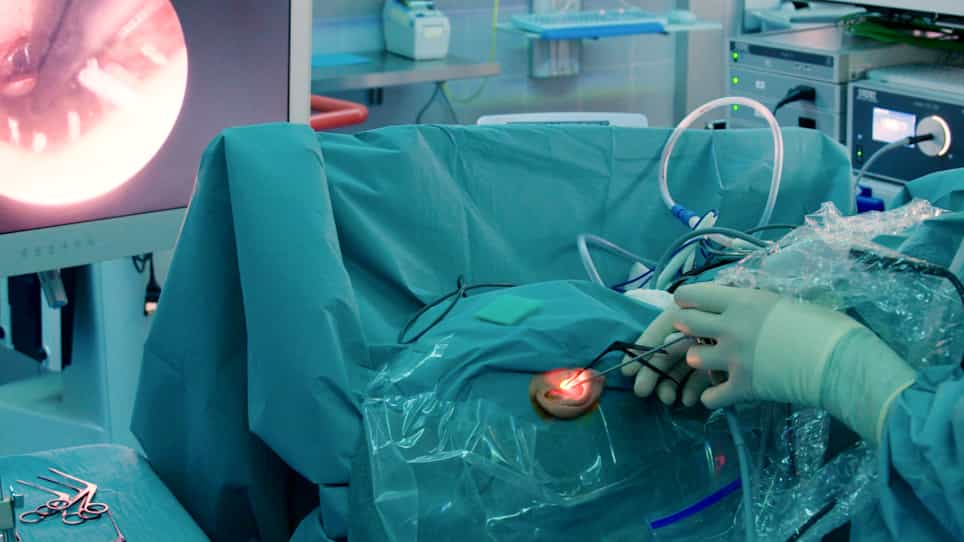

Endoscopic Cholesteatoma Surgery
Published on: January 19, 2022
Acquired cholesteatoma in children: strategies and medium-term results
A Drahy1, A De Barros, Y Lerosey
1Service d'ORL-CCF, CHU Charles-Nicolle, Rouen cedex, France.

Insights
Surgical management of paediatric cholesteatoma, particularly canal wall up tympanoplasty, shows stable hearing outcomes. Recurrence rates for acquired middle ear cholesteatoma in children are low, with minimal long-term auditory impact.
Area of Science:
- Otolaryngology
- Pediatric Surgery
- Audiology
Background:
- Acquired middle ear cholesteatoma is a significant concern in pediatric patients.
- Surgical strategies aim to eradicate disease while preserving or improving hearing.
Purpose of the Study:
- To evaluate surgical management strategies for pediatric cholesteatoma.
- To assess residual disease, recurrence rates, and medium-term auditory outcomes.
Main Methods:
- Retrospective analysis of 22 pediatric patients (<16 years) with acquired middle ear cholesteatoma.
- Follow-up exceeding four years, analyzing surgical techniques, audiograms, and recurrence rates.
Main Results:
- Canal wall up tympanoplasty was the primary approach (82%).
- Residual disease occurred in 9%, and recurrence in 18%, with an overall rate of 27%.
- Hearing loss remained stable, with air-bone gaps close to preoperative levels.
Conclusions:
- Two-stage canal wall up tympanoplasty is a common strategy in children.
- Surgical intervention for pediatric cholesteatoma yields stable long-term hearing results.
- Low recurrence rates support the efficacy of current surgical management.
Objectives:
To assess paediatric cholesteatoma surgical management strategies, residual disease and recurrence rates and especially the medium-term auditory impact.
Material And Methods:
Retrospective study of 22 cases of acquired middle ear cholesteatoma selected from a series of 77 children under the age of 16 operated for cholesteatoma between 1st January 2000 and 31st December 2003 on the basis of the following criteria: first-line surgical management with postoperative follow-up greater than four years. Surgical strategies, preoperative and postoperative (at 1 year and at the final visit) audiograms and residual disease and recurrence rates were analysed.
Results:
A canal wall up tympanoplasty was performed in 82% of cases as first-line procedure and a canal wall down tympanoplasty was performed in 32% of cases. Residual cholesteatoma was observed in 9% of cases and recurrent disease was observed in 18% of cases. The mean preoperative hearing loss was 26dB with an air-bone gap of 23dB with values of 26dB and 20dB respectively at the end of follow-up.
Conclusion:
The majority of children were operated by two-stage canal wall up tympanoplasty. Long-term hearing results remained stable and close to preoperative values. The recurrence rate (residual disease and relapse) was low (27%), as reported in the literature.