Related Experiment Video
Updated: May 23, 2026
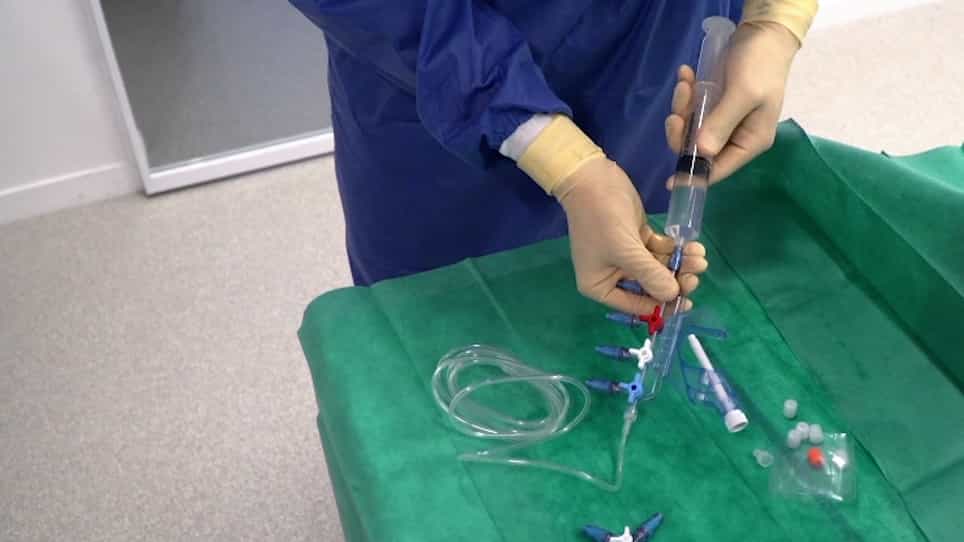

A Protocol to Set Up Needle-Free Connector with Positive Displacement on Central Venous Catheter in Intensive Care Unit
Published on: July 13, 2019
Statewide validation of hospital-reported central line-associated bloodstream infections: Oregon, 2009
John Y Oh1, Margaret C Cunningham, Zintars G Beldavs
1Public Health Division, Oregon Health Authority, Portland, Oregon, USA.

Background:
Mandatory reporting of healthcare-associated infections is common, but underreporting by hospitals limits meaningful interpretation.
Objective:
To validate mandatory intensive care unit (ICU) central line-associated bloodstream infection (CLABSI) reporting by Oregon hospitals.
Design:
Blinded comparison of ICU CLABSI determination by hospitals and health department-based external reviewers with group adjudication.
Setting:
Forty-four Oregon hospitals required by state law to report ICU CLABSIs.
Participants:
Seventy-six patients with ICU CLABSIs and a systematic sample of 741 other patients with ICU-related bacteremia episodes.
Methods:
External reviewers examined medical records and determined CLABSI status. All cases with CLABSI determinations discordant from hospital reporting were adjudicated through formal discussion with hospital staff, a process novel to validation of CLABSI reporting.
Results:
Hospital representatives and external reviewers agreed on CLABSI status in 782 (96%) of 817 bacteremia episodes (k = 0.77 [95% confidence interval (CI), 0.70-0.84]). Among the 27 episodes identified as CLABSIs by external reviewers but not reported by hospitals, the final status was CLABSI in 16 (59%). The measured sensitivities of hospital ICU CLABSI reporting were 72% (95% CI, 62%-81%) with adjudicated CLABSI determination as the reference standard and 60% (95% CI, 51%-69%) with external review alone as the reference standard (P = .07). Validation increased the statewide ICU CLABSI rate from 1.21 (95% CI, 0.95-1.51) to 1.54 (95% CI, 1.25-1.88) CLABSIs/1,000 central line-days; ICU CLABSI rates increased by more than 1.00 CLABSI/1,000 central line-days in 6 (14%) hospitals.
Conclusions:
Validating hospital CLABSI reporting improves accuracy of hospital-based CLABSI surveillance. Discussing discordant findings improves the quality of validation.
Insights
Validating hospital central line-associated bloodstream infection (CLABSI) reporting enhances accuracy. Discussing discrepancies with hospitals improves surveillance quality and data interpretation for healthcare-associated infections.
Area of Science:
- Healthcare epidemiology
- Infection control and prevention
- Public health surveillance
Background:
- Mandatory reporting of healthcare-associated infections is standard practice.
- Underreporting by hospitals can hinder accurate interpretation of infection data.
- Accurate surveillance is crucial for effective infection control.
Purpose of the Study:
- To validate the accuracy of mandatory intensive care unit (ICU) central line-associated bloodstream infection (CLABSI) reporting by Oregon hospitals.
- To assess the impact of external review and adjudication on CLABSI reporting.
- To improve the reliability of CLABSI surveillance data.
Main Methods:
- A blinded comparison was conducted between hospital CLABSI determinations and external reviewer assessments.
- External reviewers evaluated medical records for 817 bacteremia episodes in ICUs across 44 Oregon hospitals.
- Discordant cases underwent group adjudication through discussion with hospital staff.
Main Results:
- Hospital and external reviewer agreement on CLABSI status was high (96%).
- External review identified 27 unreported CLABSI cases, with 16 confirmed upon adjudication (59%).
- Validation increased the statewide ICU CLABSI rate by 27%, highlighting underreporting.
Conclusions:
- Validating hospital CLABSI reporting significantly improves the accuracy of surveillance data.
- Collaborative adjudication of discordant findings enhances the quality and reliability of CLABSI validation.
- Improved CLABSI surveillance supports better infection prevention strategies.
Related Concept Videos
 01:22
Healthcare Associated Infections II: Preventive Measures
The best practices for preventing healthcare-associated infections include hand hygiene, patient risk...
 01:26
Healthcare Associated Infections I: Iatrogenic, Exogenic and Endogenic
HAIs significantly increase the cost of health care. Extended stays in healthcare institutions, increased disability, increased costs of medications, including specialized antibiotics, and prolonged recovery times add to the patient's expenses and the healthcare institution and funding bodies. Common...
 01:29
Endocarditis IV: Nursing Management
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:11
Assessing Blood pressure in the Leg
Preparation:
 01:23
Investigation of Disease Outbreaks